BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR























TL;DR
The strangler fig pattern, wrapping your legacy system with a FHIR API layer and incrementally replacing components, is the lowest-risk modernization strategy. Here are 4 strategies ranked by risk, one cloud-migration example, and the regulatory dates that matter for non-FHIR systems.
The VA’s EHR modernization program is the cautionary tale nobody in healthcare IT can ignore. Billions spent. Years of delays. A September 2026 GAO testimony, “Actions Needed to Sustain Accelerated System Deployments” (GAO-26-109393). Sites going live after 3-year resets.
That’s what big-bang EHR modernization looks like at enterprise scale.
If you’re a CIO or VP of IT at a mid-market health system running a 5-10 year old EHR, you already know modernization is coming. The question is which strategy minimizes risk while getting you to a modern architecture.
I. How Do You Know Your EHR Needs Modernization?
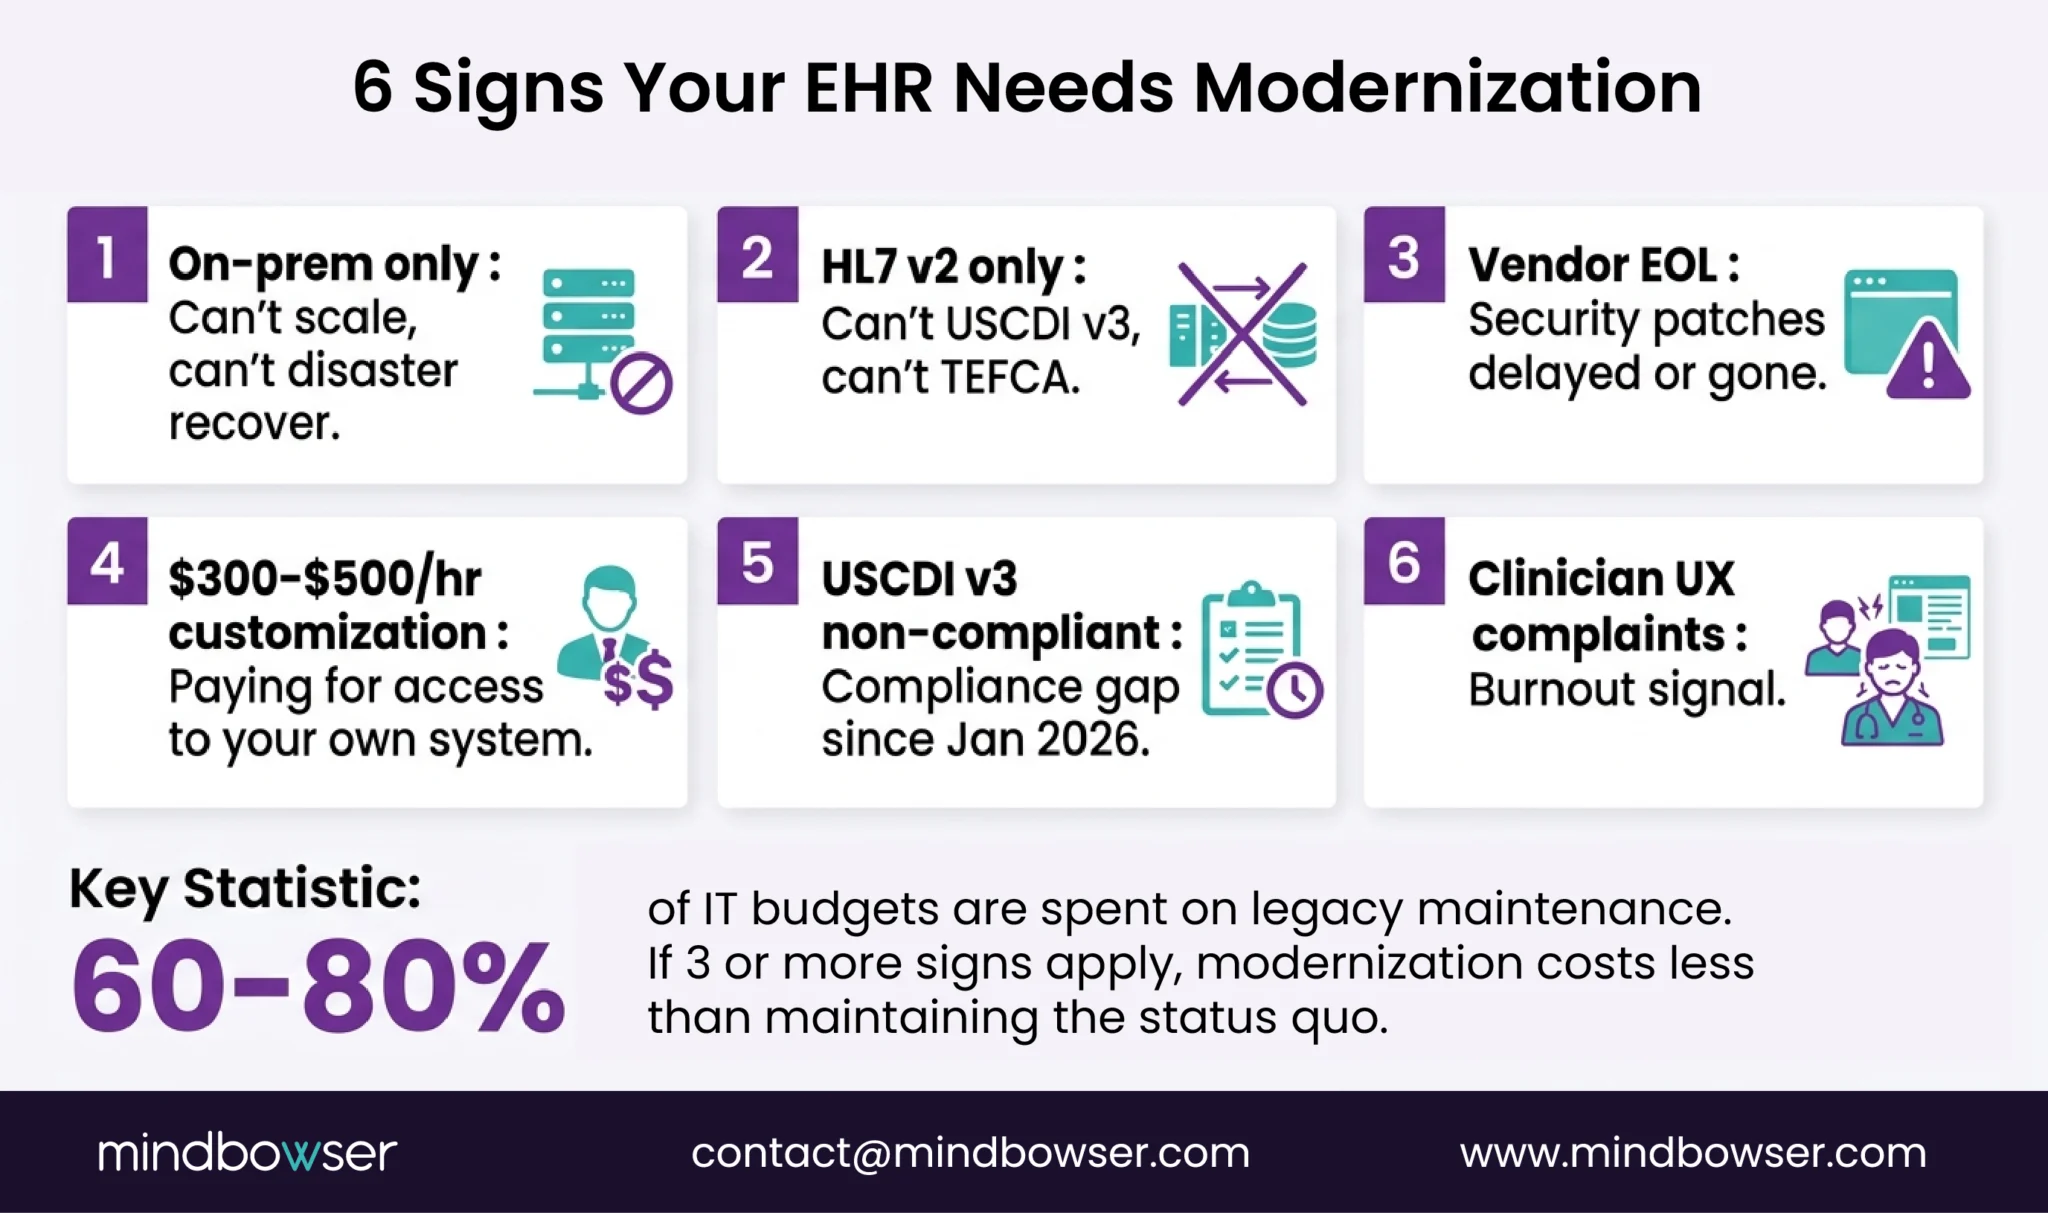
Six signs. If 3 or more describe your situation, modernization isn’t a strategic initiative — it’s an operational necessity.
- On-premise only, no cloud option. Your EHR runs on servers in your data center (or a closet). No cloud deployment path. Scaling means buying hardware. Disaster recovery means a second data center.
- HL7 v2 only, no FHIR APIs. Your system sends ADT messages and ORU results, but can’t expose patient data via FHIR R4 APIs. In 2026, that means you can’t participate in TEFCA, can’t connect modern applications, and can’t meet USCDI v3 requirements.
- Vendor no longer supports your version. End-of-life or extended support. Security patches are delayed or unavailable. You’re running on a platform the vendor has stopped investing in.
- Customization requires vendor professional services. Every template change, workflow modification, or report request goes through the vendor’s professional services team at enterprise rates. You’re paying for access to modify your own system.
- USCDI v3 compliance is not possible on current platform. USCDI v3 became mandatory for certified health IT in January 2026, with FHIR US Core 6.1.0 and SMART v2. If your platform can’t support this, modernization moves up the list.
- Clinicians complain about speed and UX. Slow load times. Excessive clicks for simple tasks. Mobile access either non-existent or barely functional. These complaints are burnout signals. The EHR-burnout link is settled science.
The budget signal: if most of your IT budget is keeping the old system alive, you may be paying maintenance costs that exceed the cost of modernization.
II. What Are the 4 EHR Modernization Strategies?
Four approaches, ranked from highest risk to lowest.
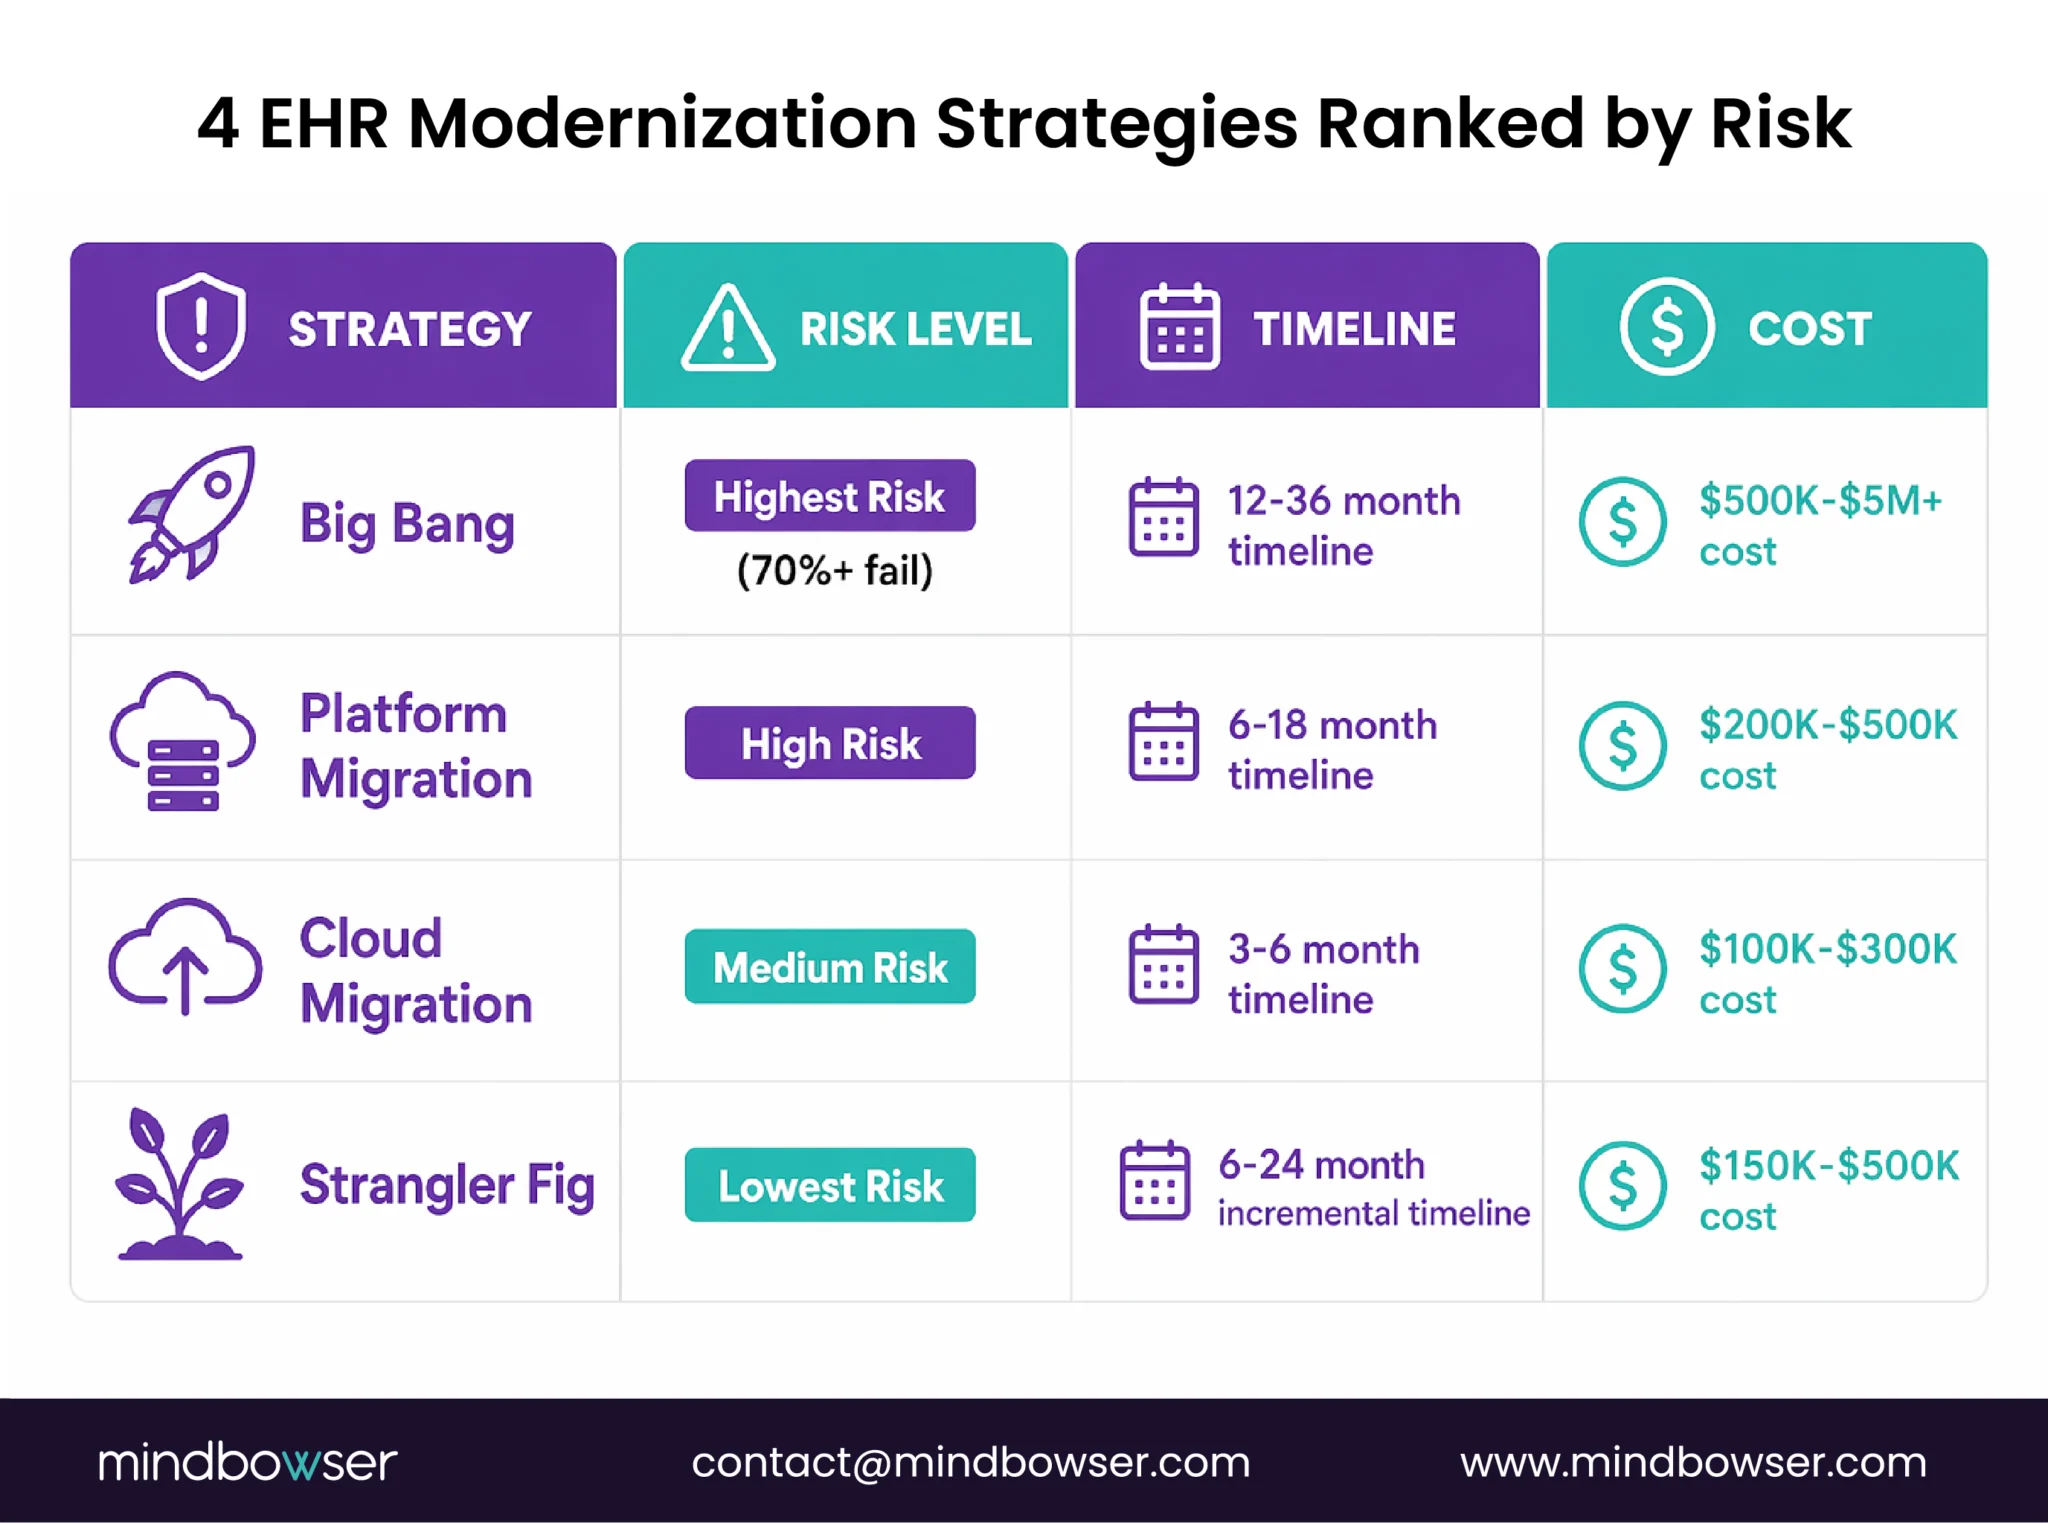
A. Strategy 1: Big Bang Replacement
Replace everything at once. New system, new data model, new workflows. Hard cutover.
- When it works: Legacy system is truly dead (vendor gone, no support, security risks unmanageable)
- Why it often fails: 70%+ of big-bang modernization projects fail or exceed budgets. Clinical continuity during the cutover is the biggest risk. If something breaks, patients are affected.
- The VA is the poster child for this risk.
B. Strategy 2: Headless Platform Migration
Move from legacy to a modern headless EHR platform (Medplum, Canvas, Oystehr). Rebuild the frontend and clinical logic on the new platform. Migrate data.
- When it works: You want a modern FHIR-native architecture AND are willing to rebuild clinical workflows
- Risk: Medium — you’re rebuilding, not just moving. But the platform handles infrastructure, so you’re rebuilding on a solid foundation.
- See our headless EHR comparison for platform selection guidance.
C. Strategy 3: Cloud Migration
Same application, new infrastructure. Move from on-premise to AWS/Azure/GCP. The clinical software doesn’t change. The hosting, database layer, networking, and cost structure do.
- When it works: Your application is viable, but your infrastructure is the bottleneck (cost, scaling, reliability)
- Our proof (a hosting move, not a full modernization): In one Azure-to-AWS migration for a US healthcare technology company, Mindbowser moved 180 production databases and roughly 30TB of EHR and telemedicine data without disrupting HIPAA-regulated operations. Full EHR migration details.
Cloud migration is “enough” when your application architecture is sound but your infrastructure isn’t. If the application itself is the problem (outdated data model, no FHIR support, poor UX), cloud migration just moves the problem to a different data center.
D. Strategy 4: Strangler Fig (Recommended)
The lowest-risk strategy for most legacy EHR systems. We recommend this as the default approach unless there’s a specific reason to choose otherwise.
Modernize Your EHR Without Disrupting Clinical Operations
III. How Does the Strangler Fig Pattern Work for EHR?
The strangler fig is a tree that grows around an existing tree, eventually replacing it. The software pattern does the same: gradually replace legacy components while keeping the system running.
4 steps, designed to keep clinical systems running:
A. Step 1: Wrap Legacy with a FHIR API Layer
Build a FHIR R4 API layer on top of your legacy EHR. The legacy system continues running. The API layer translates legacy data formats (HL7 v2, proprietary databases) into FHIR resources.
- Legacy system: unchanged
- New applications: connect through FHIR APIs, not directly to the legacy database
- USCDI v3 compliance: achieved at the API layer, even if the legacy system doesn’t natively support it
- This is “Type 5: FHIR API Wrap” from our data migration guide. Timeline and cost depend on your system; our EHR software cost guide covers typical build and integration ranges.
B. Step 2: Build New Modules on Modern Stack
With the FHIR API layer in place, build new clinical modules on a modern architecture – Medplum, custom React frontend, or a headless platform. These new modules read from and write to the FHIR API layer.
- New scheduling module replaces legacy scheduling
- New clinical documentation module with AI-native capabilities
- New patient portal with mobile access
- Each module is independent. If one has issues, the legacy system is still running.
C. Step 3: Route Traffic to New Modules
As new modules reach production quality, route users to them. The legacy system handles everything the new modules don’t cover yet. Over time, more and more functionality moves to the modern stack.
- Gradual user migration (department by department, or feature by feature)
- A/B testing possible: some users on the new system, some on legacy system
- Clinical continuity is maintained throughout – patients never experience a “switchover” moment
D. Step 4: Decommission Legacy Components
When all critical functionality has been migrated to the modern stack, the legacy system moves to read-only (for historical data access and audit trails), then full decommission.
- Keep legacy in read-only for 30-90 days, set by your retention and audit needs
- Migrate remaining historical data to the FHIR data store
- Decommission legacy infrastructure
Why strangler fig works for clinical systems: The #1 risk in EHR modernization is clinical continuity. Patients don’t stop getting treated during a system upgrade. The strangler fig ensures the old system runs until the new one proves itself in production. No hard cutover. No “go-live weekend” where everything has to work. Incremental risk instead of concentrated risk.
Evaluating modernization strategies for your legacy EHR? Tell us about your current system, and we’ll map the approach — strangler fig, cloud migration, platform migration, or a combination.
IV. When Is Cloud Migration Enough vs Full Modernization?
This is the decision most CIOs struggle with. The answer depends on where your technical debt lives.
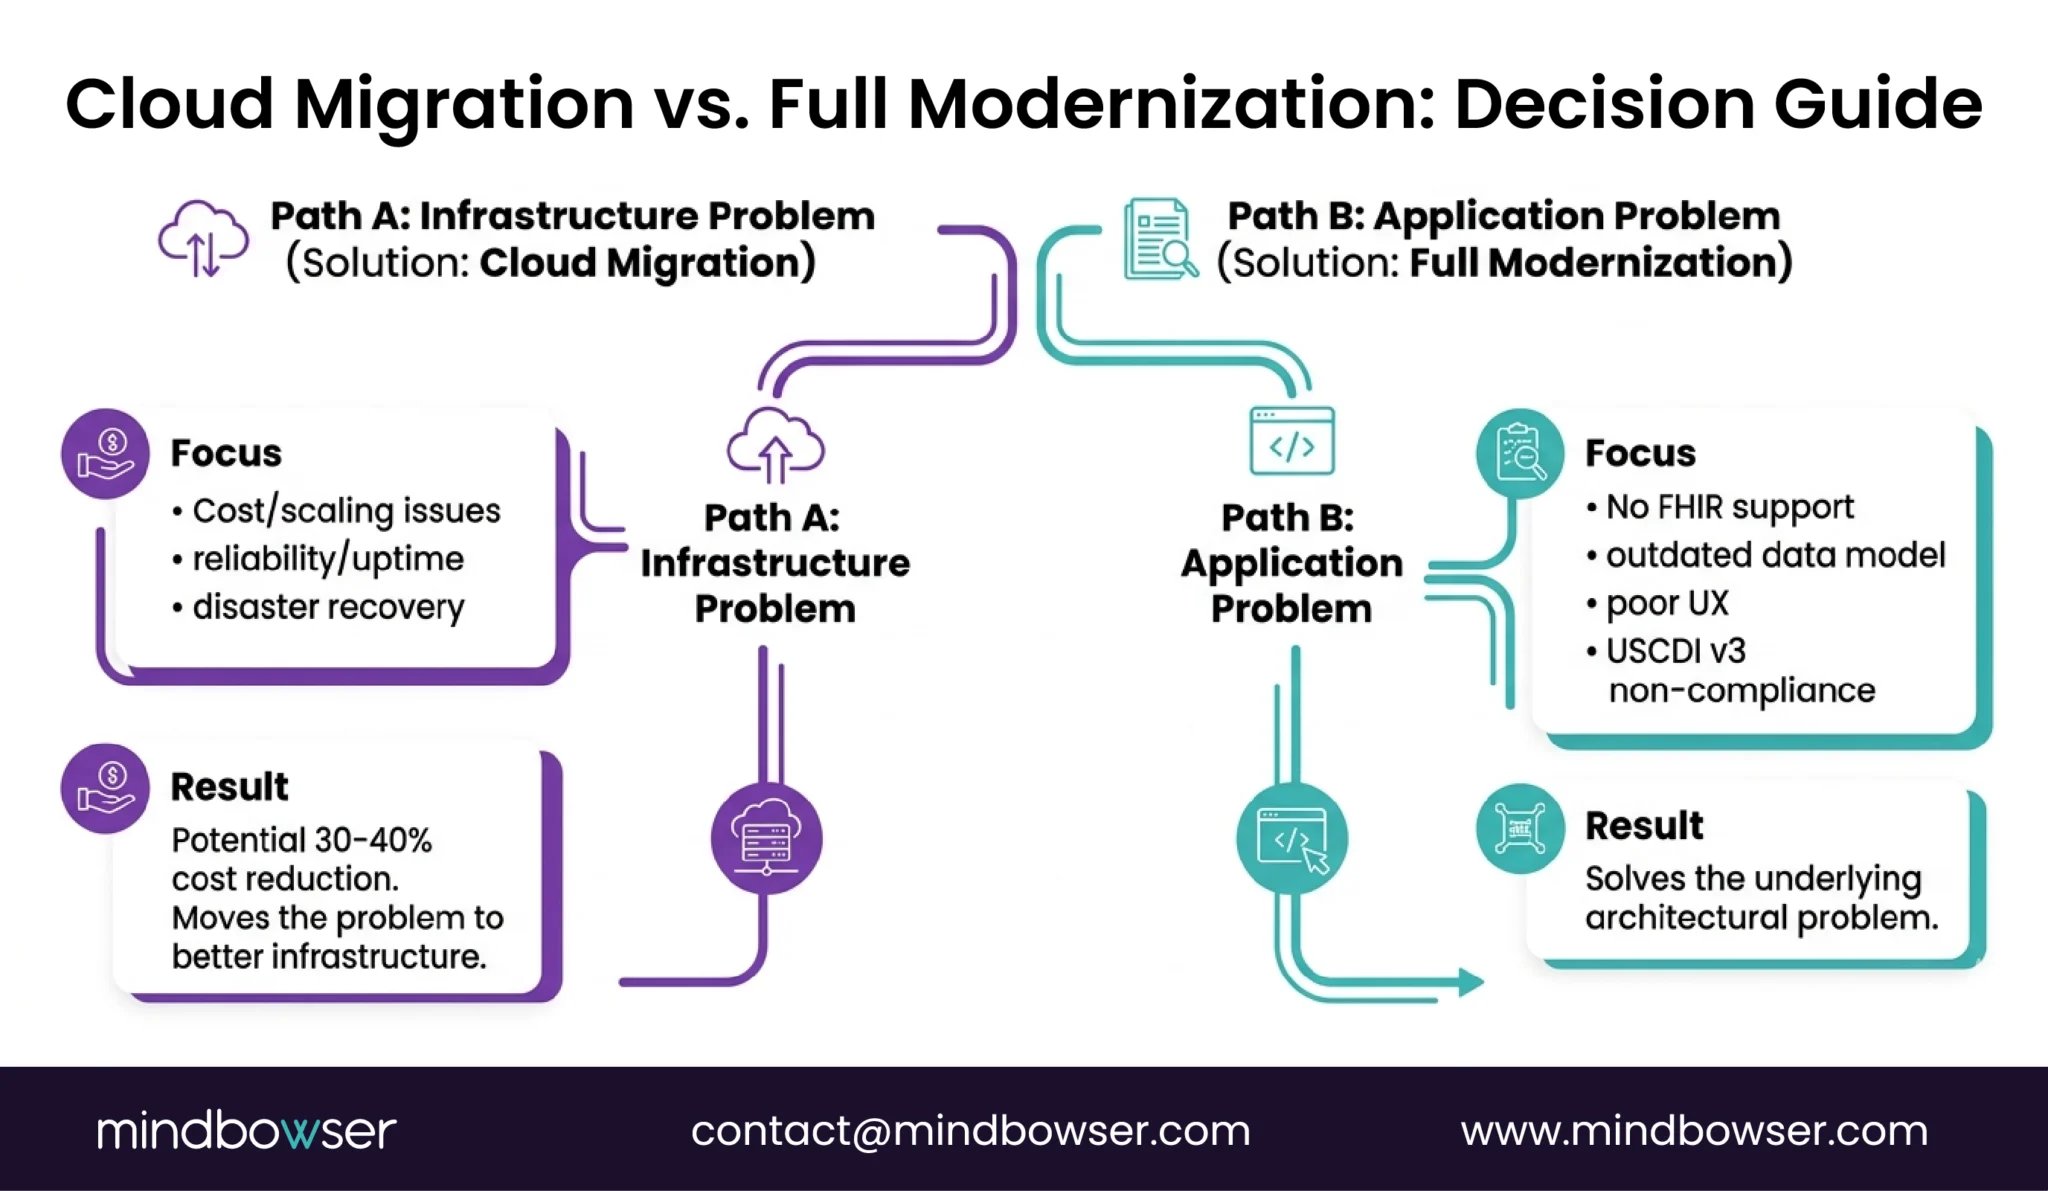
- Our cloud migration in numbers: A multi-specialty healthcare platform needed to move from Azure to AWS. The application was sound — the infrastructure was the bottleneck.
- Mindbowser moved 180 production databases and roughly 30TB of EHR and telemedicine data without disrupting HIPAA-regulated operations
The platform kept running throughout. That’s the cloud migration promise — better infrastructure, same application, no clinical disruption.
V. What Regulatory Deadlines Are Forcing Modernization?
Three deadlines that turn modernization from “should do” into “must do.”
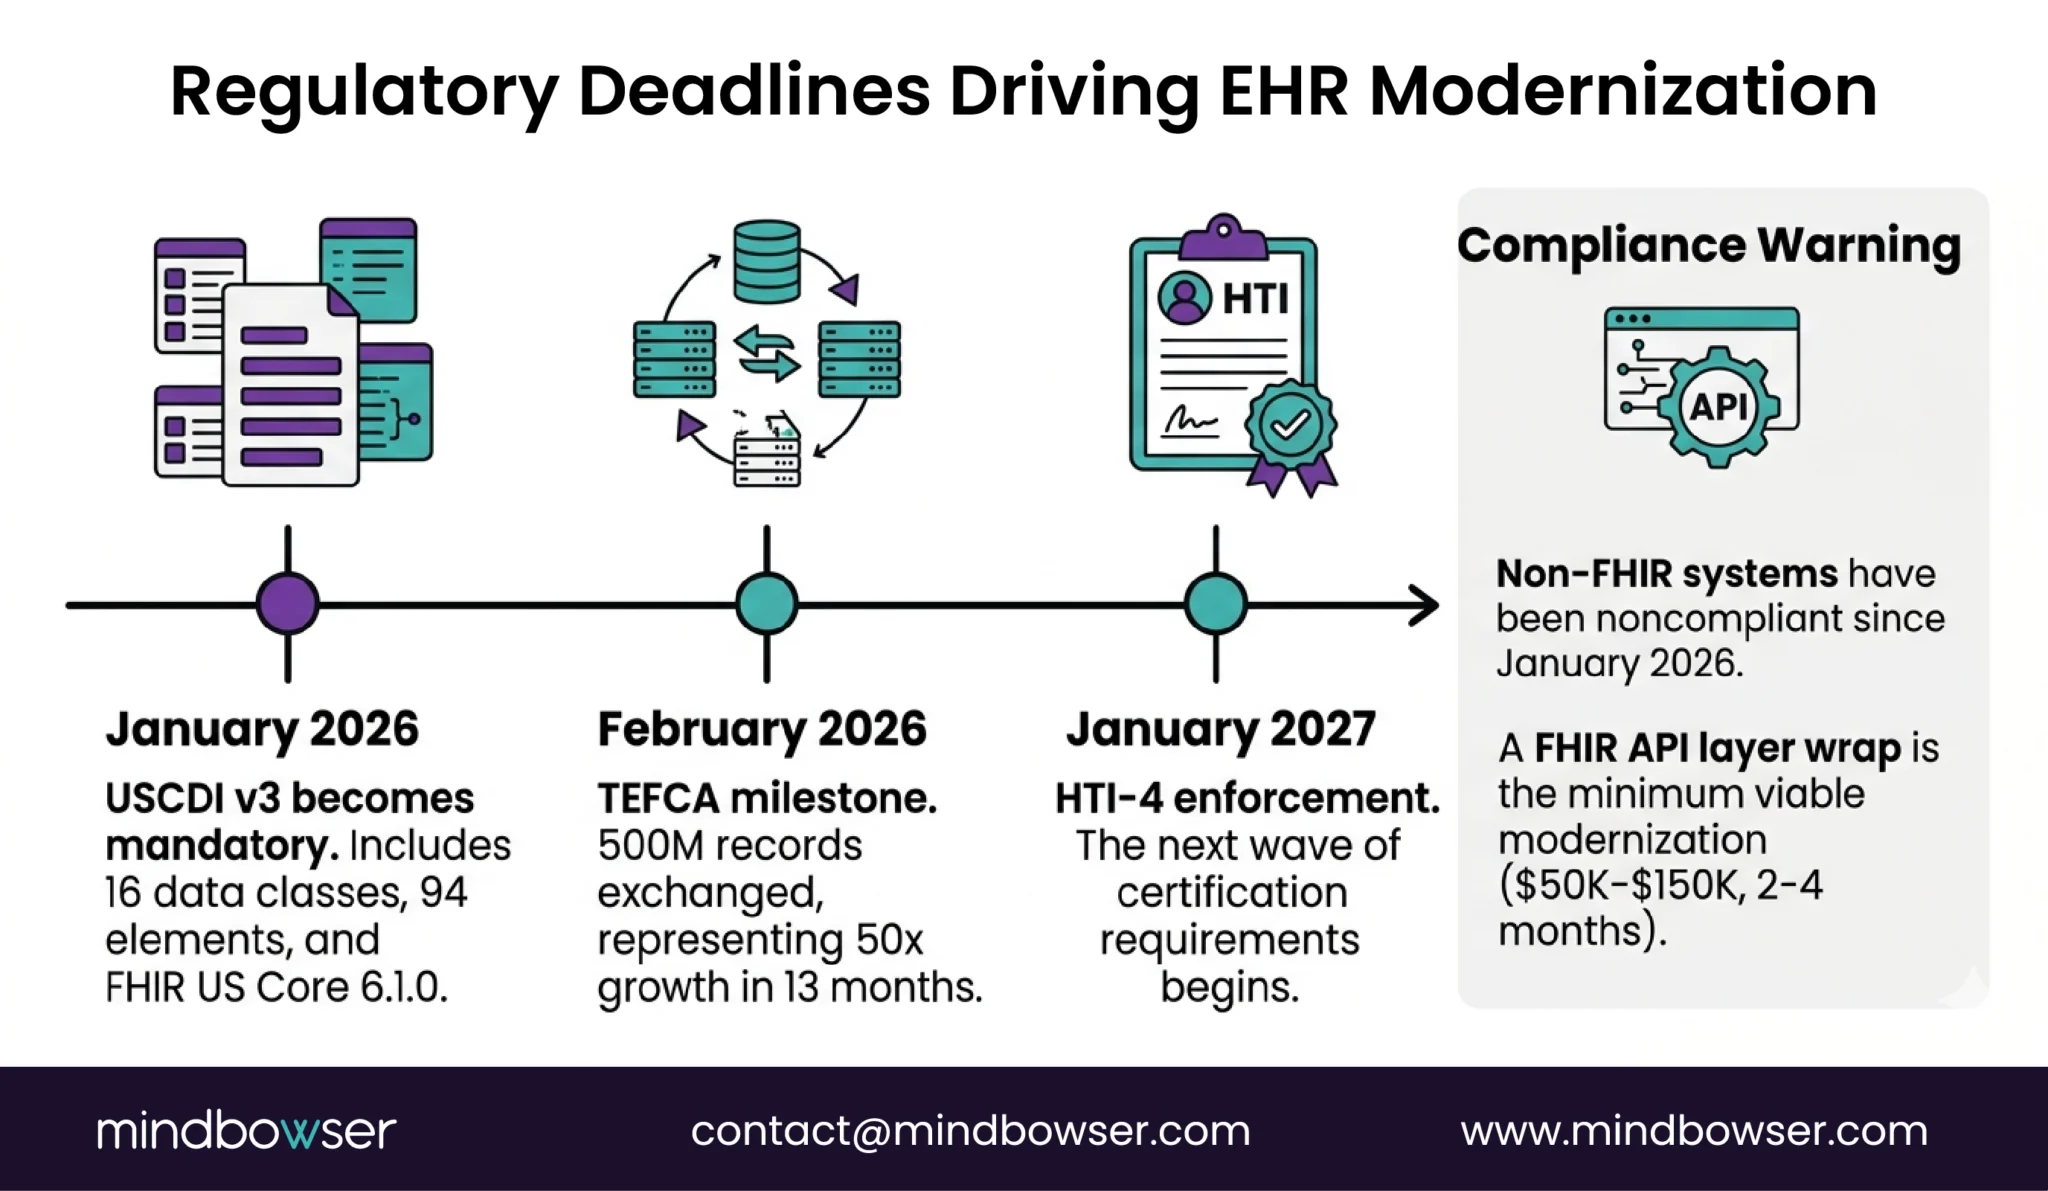
A. USCDI v3 – Mandatory since January 1, 2026
- FHIR US Core 6.1.0 required
- USCDI v3 binds certified health IT. If your legacy EHR can’t expose FHIR R4 APIs with v3 data elements, it falls behind what certified systems and exchange partners now expect
B. HTI-4: in effect since October 1, 2025, with staged compliance dates through 2027-2028
- Next wave of ONC certification requirements
- Legacy systems not on the HTI-4 path face increasing certification gaps
C. TEFCA – Interoperability at scale
- TEFCA participation is voluntary, but systems that can’t exchange through it miss a growing national network
- If you can’t exchange data via FHIR, you’re not just behind on compliance. You’re disconnected from the healthcare data ecosystem.
The practical implication: If your legacy EHR doesn’t support FHIR R4 APIs, the strangler fig Step 1 (FHIR API layer wrap) becomes your minimum viable modernization. It gives you a FHIR R4 interface for USCDI v3 data and a path to TEFCA exchange without replacing the underlying system, while you plan the longer modernization. Typical costs are in our EHR software cost guide.
Conclusion
For non-FHIR systems, the regulatory dates are here, and the cost of standing still keeps rising. If most of your IT budget is spent on maintenance, that is the clearest signal that the math now favors modernization. A strangler fig approach is a bounded investment, while legacy maintenance is an indefinite expense.
For most healthcare organizations, the strangler fig approach is the safer path compared to a big-bang replacement. Big-bang projects carry the most risk, while the strangler fig wraps the legacy system with FHIR, replaces modules incrementally, and retires the old system only after the new one has proven itself in production. This approach maintains clinical continuity, avoids downtime, and spreads risk over time instead of concentrating it into a single go-live event.
USCDI v3 also changes the conversation from strategic planning to immediate action. If your legacy EHR cannot support FHIR R4 APIs, the minimum viable modernization is a FHIR API layer wrap. That step is not the full modernization journey, but it provides the compliance bridge that allows you to meet current requirements while creating time to plan the broader transformation.