
















 BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR



























TL;DR
- Off-the-shelf SLP software (TherapyNotes, SimplePractice, ClinicSource) covers basic scheduling and billing but breaks on insurance pre-auth automation, state licensing enforcement, and multi-clinic referral coordination.
- Custom SLP EHR solves these by automating payer pre-auth lookup, enforcing state-specific supervision models in real-time, and wiring ENT-to-SLP and neurology-to-SLP referral workflows.
- Build vs. buy hinges on clinic size (under 10 clinicians: buy; 20+: custom), state regulatory complexity (multi-state networks: custom), and insurance payer mix (70%+ Medicaid/Medicare: custom ROI is 6-18 months).
Why Do SLP Practices Need Specialized EHR Software, Not Generic Practice Management?
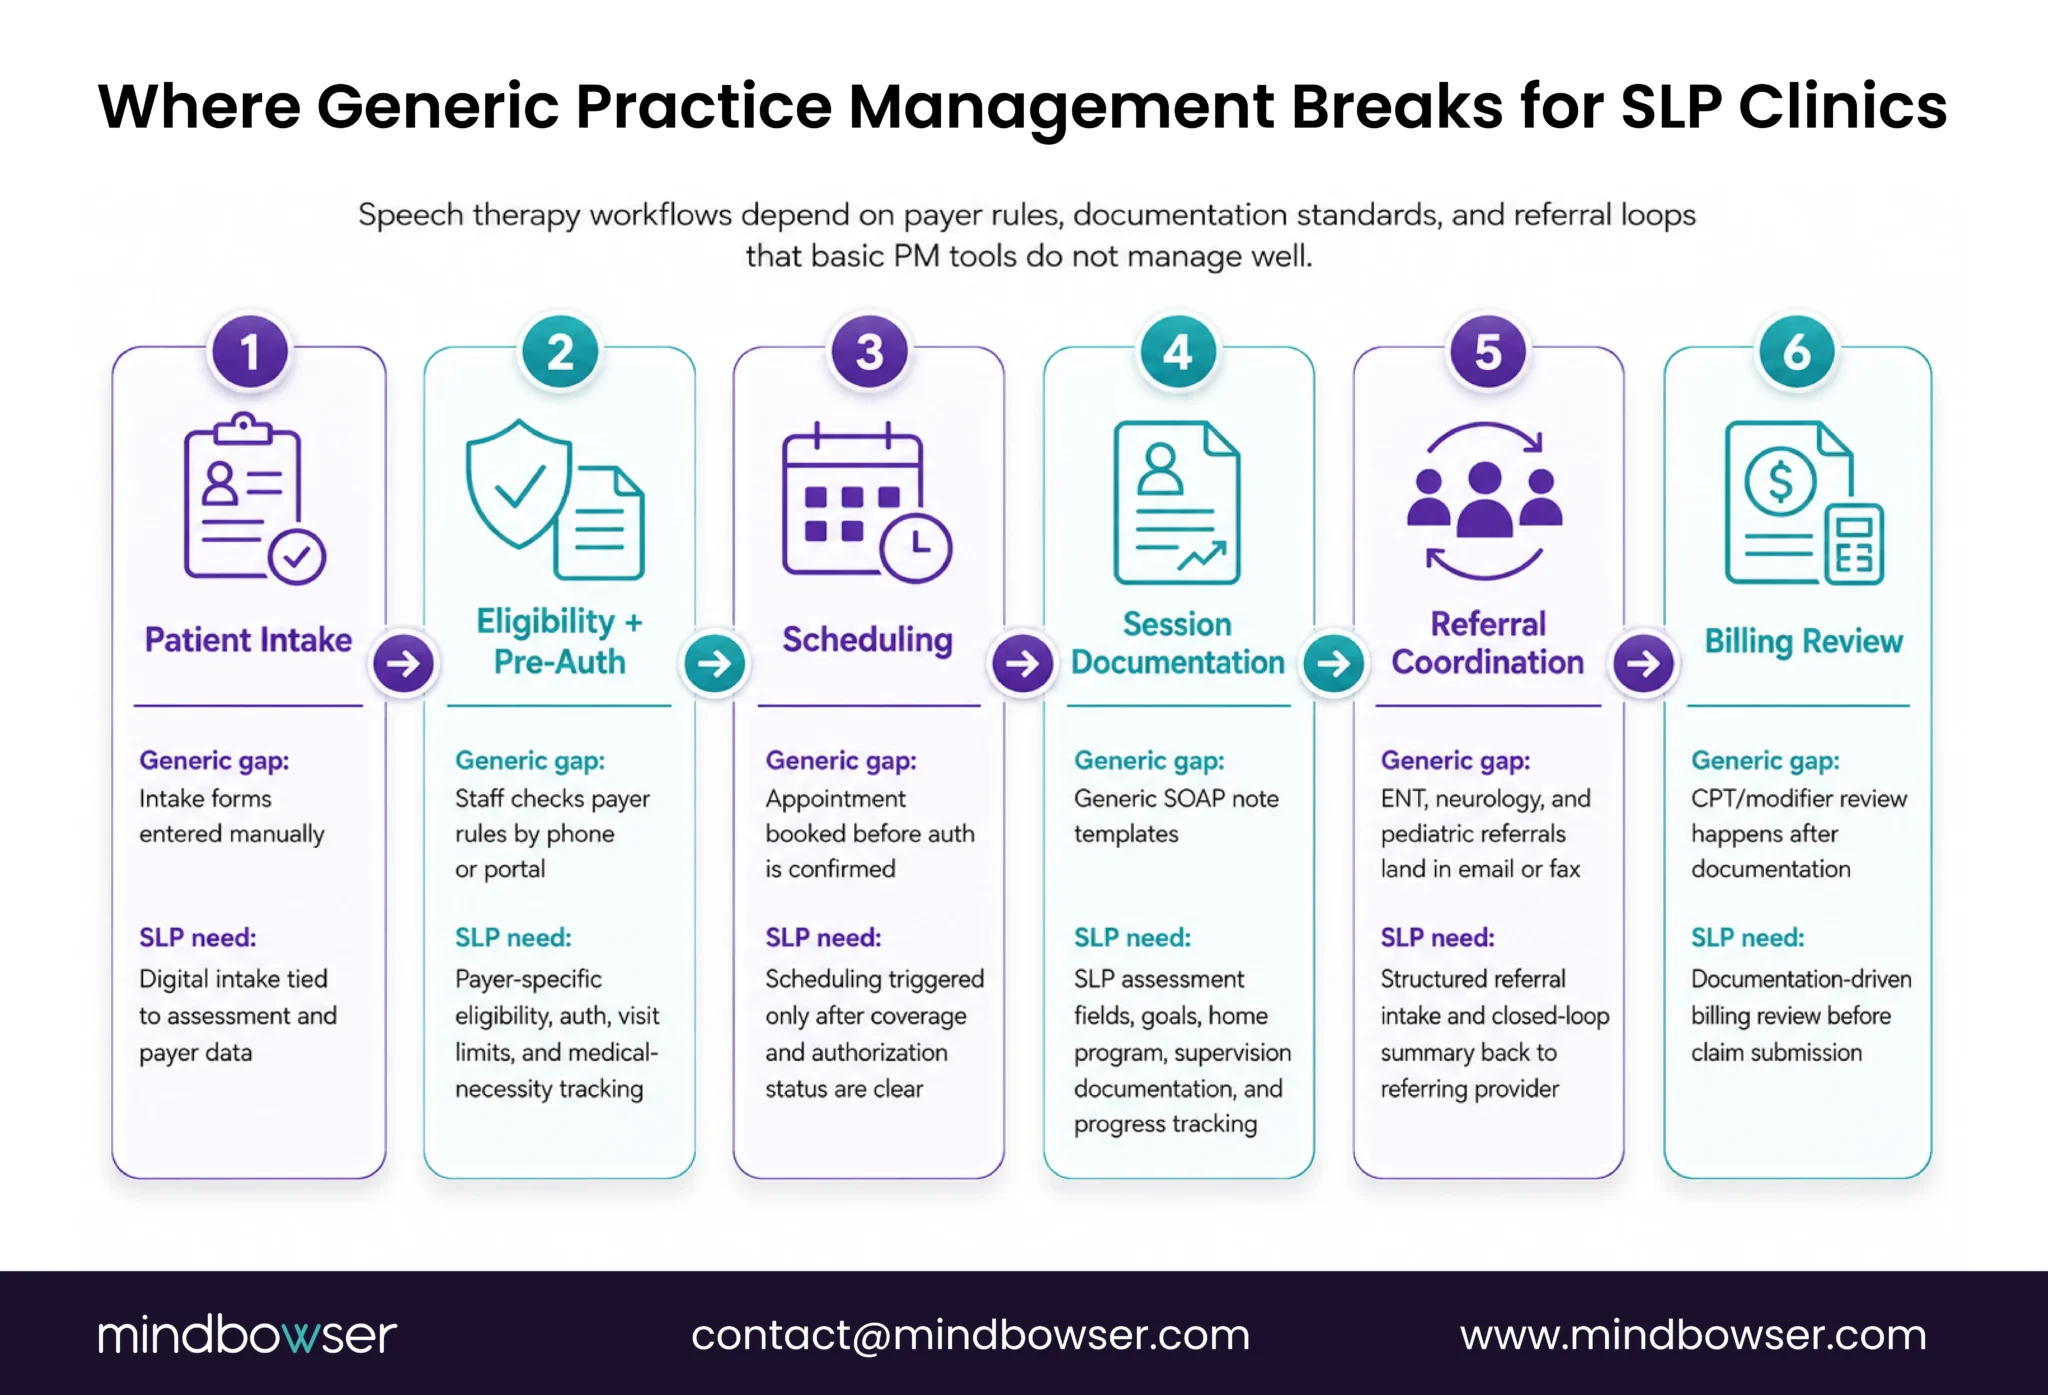
Generic practice management software breaks on three fronts for SLP clinics.
First: insurance pre-auth automation. Medicare and Medicaid require pre-auth verification for 40% of all SLP claims. That is dramatically different from other specialties. A typical SLP clinic with 20-30 patient intakes per week burns 75-150 hours per month on manual pre-auth checks across five to seven different payers, each with different rules.
ASHA’s 2024 Workforce Survey found that SLP clinicians spend 8-10 hours per week on documentation and insurance verification combined, versus 4-6 hours in systems with built-in SLP modules. Generic PM software has no concept of SLP-specific CPT codes (92507 treatment, 92508 group, 92521-92524 evaluation, 92526 swallowing/feeding, 92610 swallowing eval), CMS billing rules, or state-to-state variation.
The cost hits twice. First: labor. Those 75-150 hours per month are wages, burned on busywork. Second: denials. CMS data from 2024 shows SLP claims have a 12-15% denial rate, versus 8% for PT and 5% for MD office visits. The leading cause is CPT code mapping errors. Generic software tries to fit SLP into a PT template, misses state-specific CPT scope rules, and bakes errors into every claim.
Second: state licensing variation. Thirty-eight states regulate SLPs. Twelve states do not. Of the 38 regulated states, supervision requirements vary sharply. California allows direct or indirect supervision, both documentable in the EHR. New York requires direct supervision (with rare exceptions), and the EHR must track this per session. Texas is deregulated for adult SLP.
Florida requires direct or indirect supervision, and documentation standards are state-specific. When you run a multi-site SLP clinic across two or three states, generic PM software can’t enforce per-state rules. You end up managing compliance in spreadsheets.
HIPAA adds another layer. SLP handles sensitive data: developmental milestones, cognitive assessment results, swallowing and aspiration history, dysphagia care plans. That data tier is higher sensitivity than a routine physical exam note. State privacy laws vary. Some states impose additional HIPAA rules for speech and language pathology records. Generic software doesn’t know this.
Third: referral coordination. SLP clinics don’t get walk-in traffic. Referrals come from ENT, neurology, pediatrics, and other medical providers. Those referrals land in your email, your fax, your phone, or (if you’re lucky) a web form. The referral data (patient name, diagnosis, medical necessity, insurance info) has to be re-entered into your system.
That is manual data entry waste. And when your clinic finishes the SLP evaluation, where does that summary go? Back to the ENT practice? Usually not automatically. The referral loop breaks.
Quick comparison: off-the-shelf generic PM software costs $100-150 per clinician per month. Off-the-shelf SLP-focused software (TherapyNotes, SimplePractice) costs $165-200 per clinician per month. Custom SLP EHR costs $80,000-250,000 upfront plus $5,000-15,000 per month in support. But custom solves all three problems. Generic doesn’t.
What Are the Best Speech Therapy EHR Platforms?
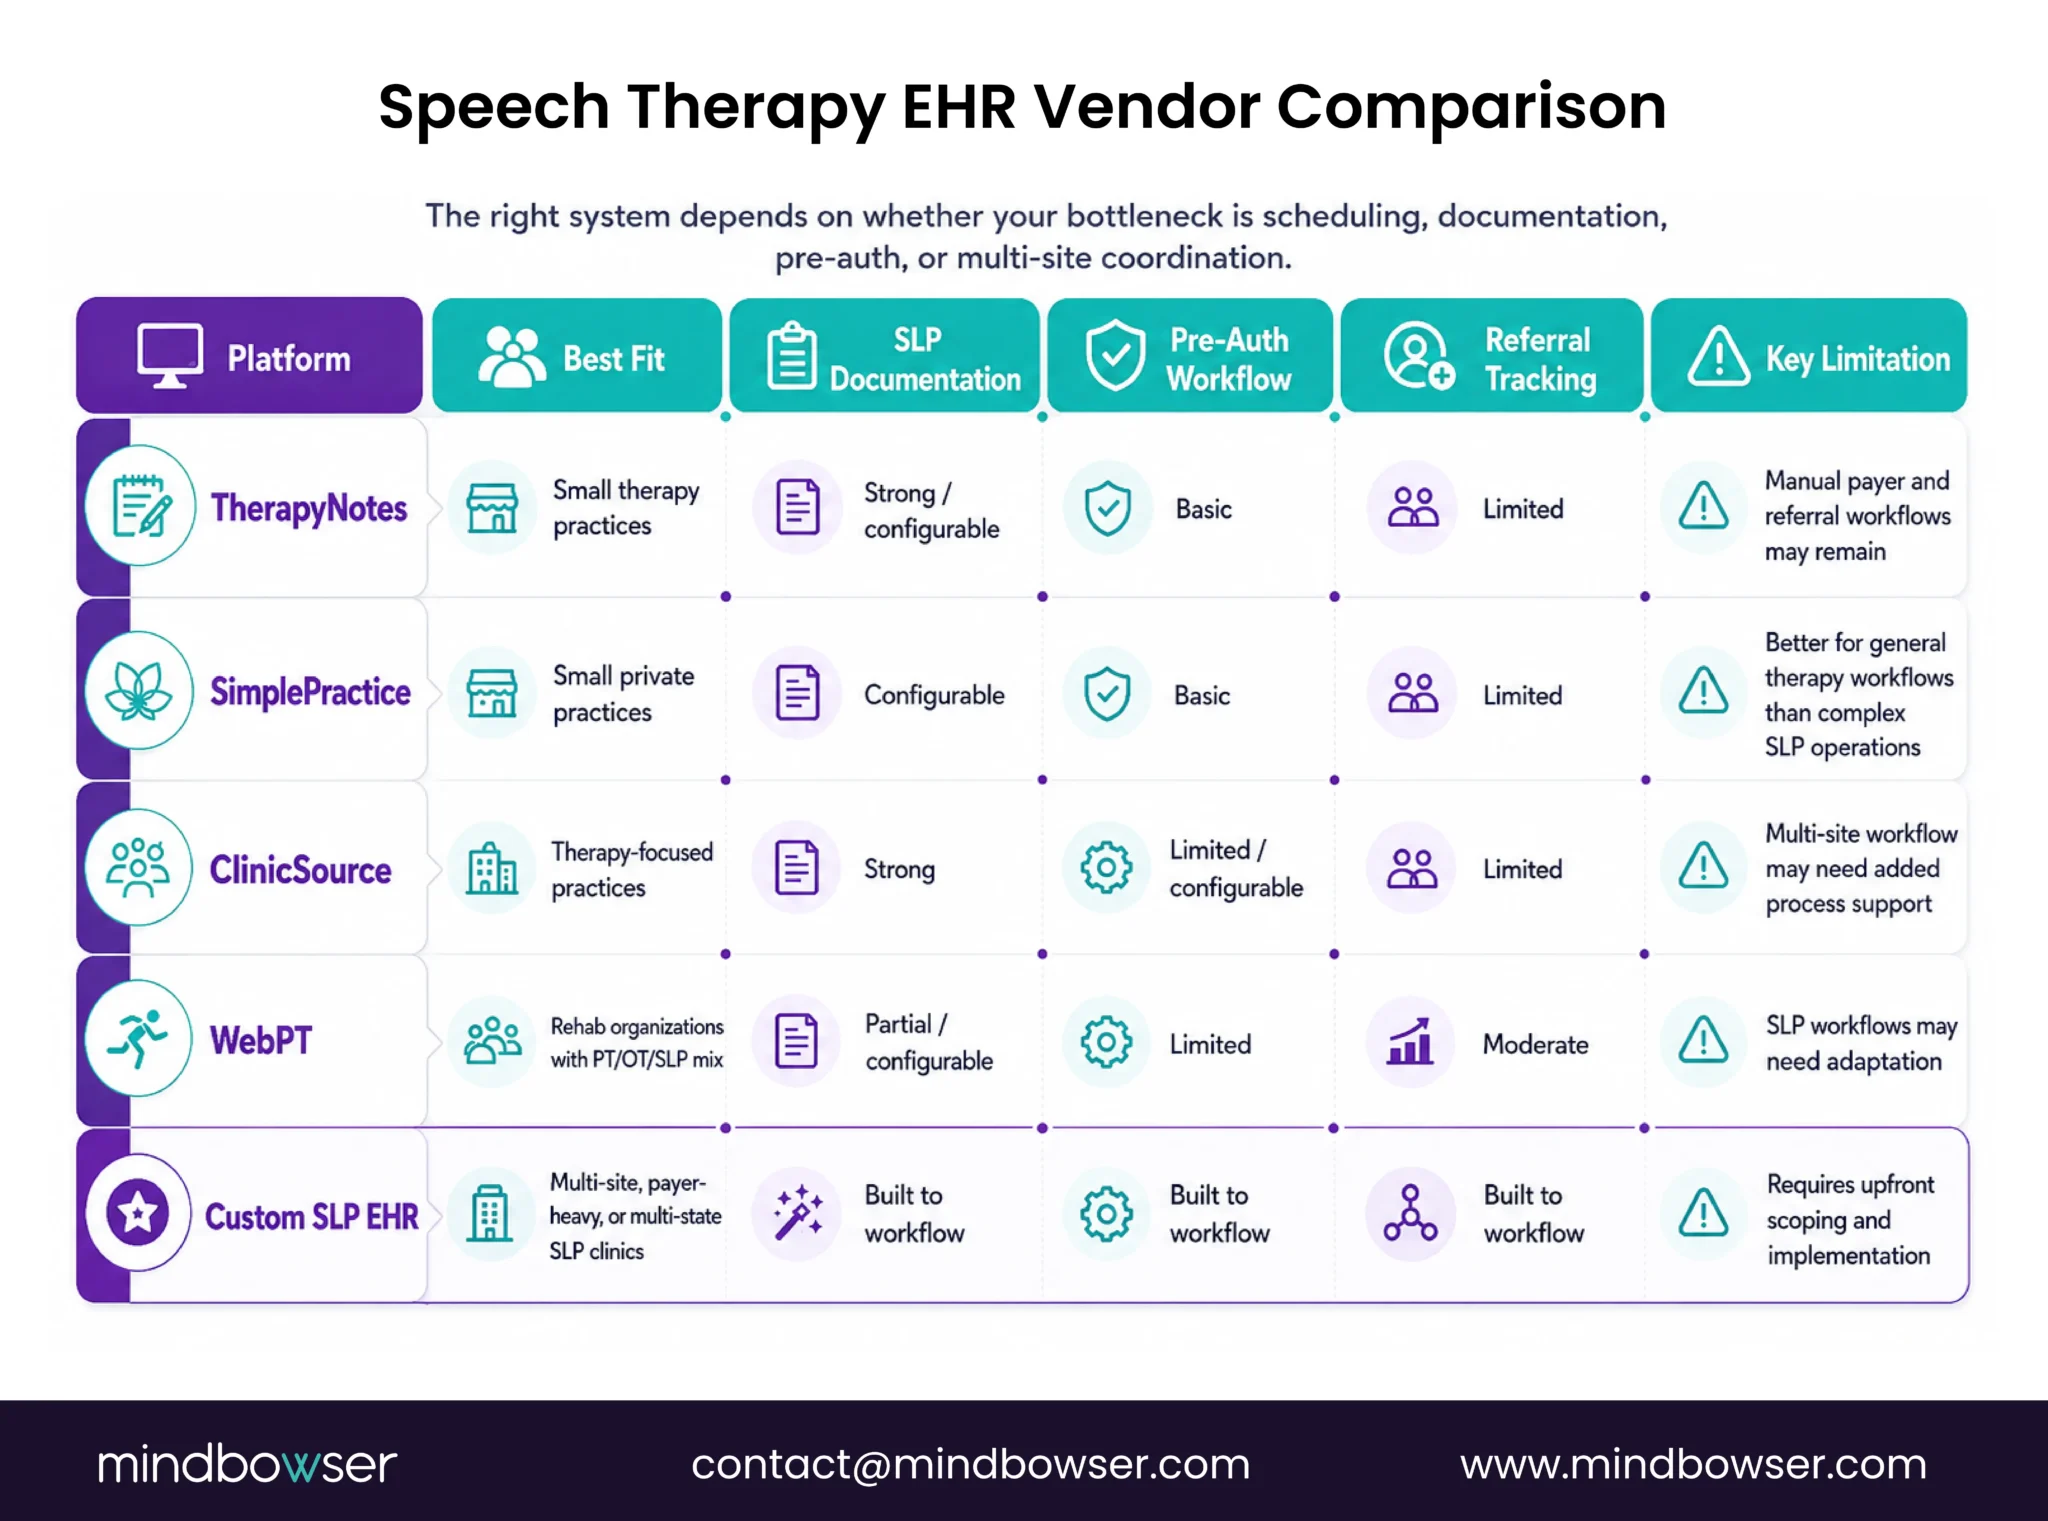
If you need off-the-shelf, here is what exists in the market.
1. TherapyNotes ($200/clinician/month)
Strengths: SLP-focused, built from the ground up for therapy practices, strong scheduling, basic insurance verification. Weaknesses: limited pre-auth automation (you still make some insurance calls), no state licensing enforcement (compliance is manual), limited multi-site referral tracking.
2. SimplePractice ($165/clinician/month)
Strengths: broad therapy PM (works for PT, OT, SLP), decent scheduling, low cost. Weaknesses: SLP module feels like an add-on to a PT template, pre-auth automation is weak, state licensing variation is not enforced, referral tracking is manual (spreadsheet-adjacent).
3. ClinicSource (varies, SLP-specific)
Strengths: dedicated SLP software, SLP-specific CPT codes (92507, 92508, 92521-92524) and progress note templates built-in, decent single-site operation. Weaknesses: scaling to multi-site is messy, pre-auth integration is limited, no real-time state licensing enforcement.
4. WebPT (varies)
Strengths: strong scheduling, multi-site capability. Weaknesses: primarily PT/OT, SLP module is an add-on, pre-auth automation designed for PT insurance rules (not SLP), state licensing variation not enforced.
Feature comparison matrix:
| Feature | TherapyNotes | SimplePractice | ClinicSource | WebPT | Custom EHR |
|---|---|---|---|---|---|
| SLP-specific modules | Yes | Partial | Yes | Partial | Yes |
| Pre-auth automation | Basic | Basic | Limited | Limited | Comprehensive |
| State licensing enforcement | No | No | No | No | Yes |
| Multi-site referral tracking | Basic | No | No | Yes (clunky) | Yes |
| Telehealth SLP billing | Yes | Yes | Yes | Yes | Yes |
| Cost per clinician/month | $200 | $165 | Varies | Varies | $333-833 (amortized) |
| Custom integration (FHIR/API) | Limited | Limited | Limited | Limited | Full |
The pattern is clear: off-the-shelf software trades cost for functionality. You get basic SLP capability for $165-200/month. You do not get automation.
But the cost gap closes faster than most clinic managers expect once you factor in admin labor and denial rates.
Why Is Insurance Pre-Auth the Biggest Bottleneck in SLP Clinics?
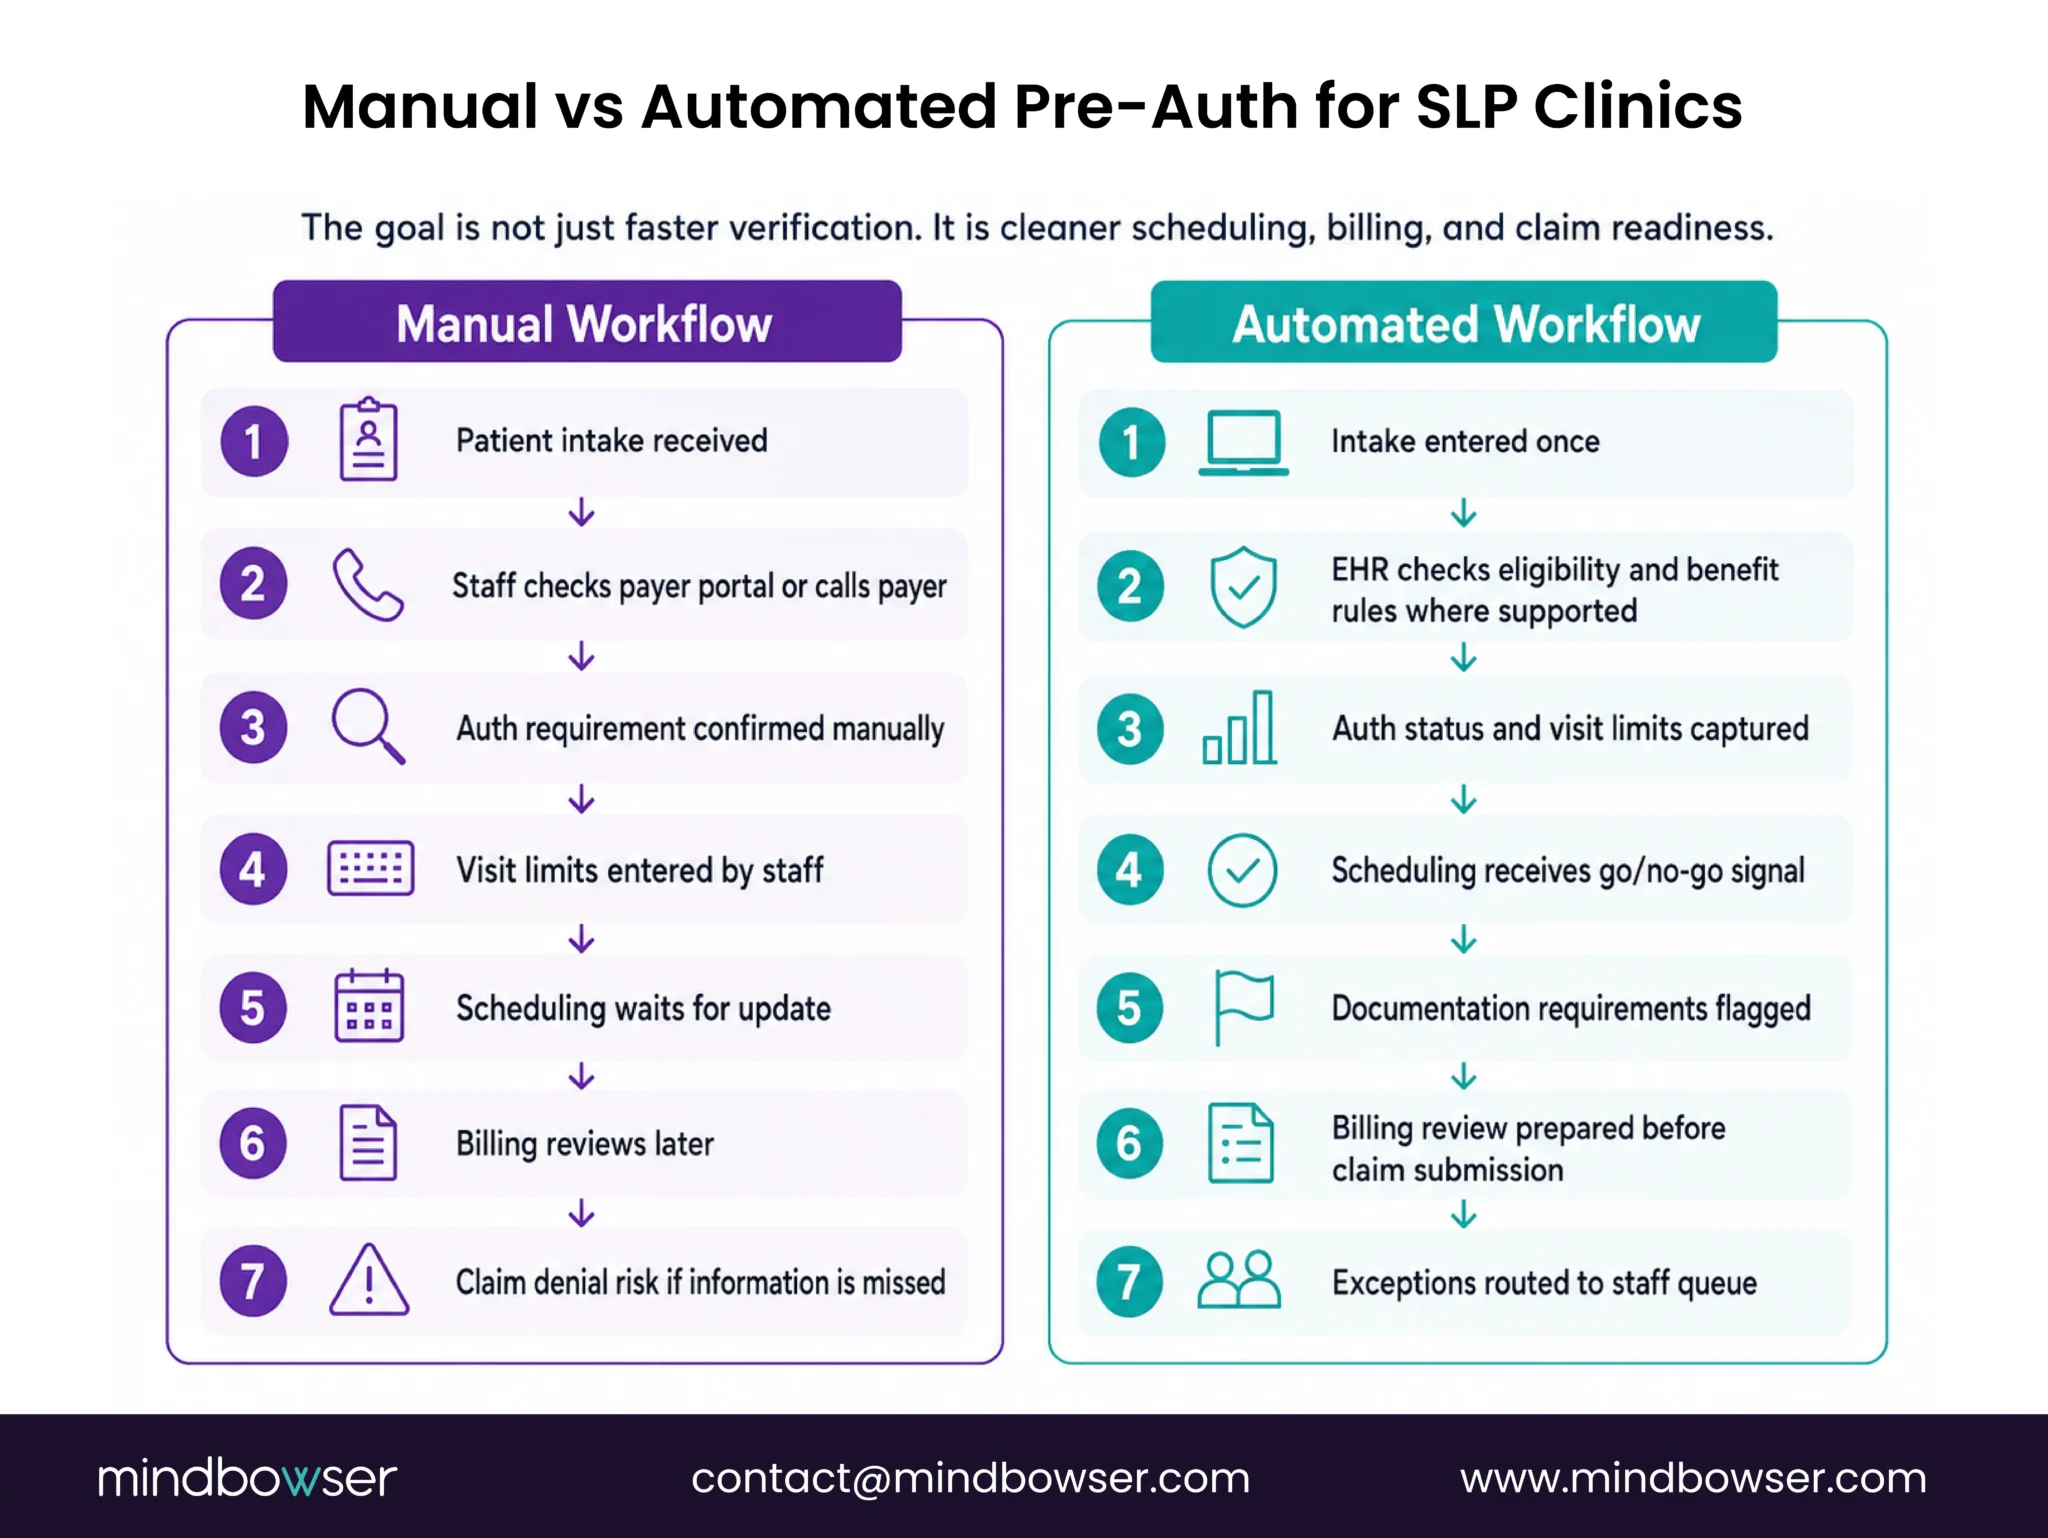
Here is where off-the-shelf breaks and custom wins.
Forty percent of SLP claims require pre-auth. Each pre-auth check is 15-20 minutes of work: look up the payer, call their pre-auth line, verify medical necessity, document the auth number, enter it into the EHR, repeat for the next payer if the patient has secondary insurance. A 15-clinician SLP clinic with 25-30 patient intakes per week runs 75-150 hours per month on this task alone.
Do the math. 75 hours per month at $35 per hour (all-in wage cost, per BLS Occupational Employment Statistics 2024 for medical billing and insurance verification staff) is $2,625 per month, or $31,500 per year, for one administrative task. One hundred fifty hours per month is $5,250 per month, or $63,000 per year.
That is not small.
And pre-auth failure compounds the problem. When your clinic misses a pre-auth on an SLP claim, the claim gets denied. The billing staff finds out days or weeks later. Then you appeal, resubmit, and wait 30-60 days for reconsideration. That is cash collection delay. For a $500,000-per-year SLP clinic, a 2-3% denial rate due to a pre-auth miss means $10,000-15,000 per year in revenue leakage, just sitting in denial queues.
How a custom EHR automates this.
A custom SLP EHR integrates with payer verification APIs. When a new patient arrives for intake, the front desk enters their name, date of birth, and insurance card number. The EHR queries the payer connections you have configured in real-time, typically the major national payers plus the state Medicaid systems you bill:
- Is this patient covered for SLP services?
- What medical necessity documentation is required?
- Is prior auth required before the first visit?
- What is the auth number?
- How many visits are authorized?
- What is the co-pay or deductible?
All in 60 seconds. The front desk sees a go/no-go signal before scheduling the first appointment. No phone calls. No guessing. No denial risk.
If the patient gets rescheduled and the date-of-service changes, the EHR re-checks the pre-auth in the background. If the authorization window closes, an alert pops up for the billing staff. If a claim gets denied, the EHR auto-suggests appeal documentation based on CMS rules. The appeal workflow is built into the system.
Custom SLP EHRs built at Mindbowser have cut pre-auth turnaround from 5-7 days (manual phone tag) to 3 hours (automated API queries). Clinics report a 2-3% improvement in claim approval rate, which translates to $10,000-20,000 per year in recovered revenue for a mid-sized practice.
What State Licensing Requirements Must Your SLP EHR Enforce?
Here is where it gets thorny for multi-site or multi-state operations.
SLP is unique among therapy disciplines: licensing and documentation requirements vary sharply by state. Your EHR must enforce YOUR state’s rules in real-time, and if you operate across multiple states, it must enforce each state’s rules by clinic location.
Let’s look at five states:
1. California: SLP license required, supervision can be direct or indirect (both documented in the progress note). Progress note format is not state-mandated but must be SOAP-aligned (Subjective, Objective, Assessment, Plan, the standard clinical note format). Mindbowser custom EHR: enforces licensing requirement, allows direct/indirect flag per session, templates auto-format notes.
2. New York: SLP license required, direct supervision mandatory (with rare exceptions). Progress note must follow New York-specific documentation standards. Mindbowser custom EHR: enforces direct supervision model per session, blocks indirect documentation, templates match state standards.
3. Texas: Adult SLP is deregulated (no state license required). Pediatric SLP may have school-district rules but not state licensure. Progress notes follow clinic/insurance standards. Mindbowser custom EHR: no license check, but HIPAA and insurance pre-auth rules still apply.
4. Florida: SLP license required, direct or indirect supervision allowed (documented per session). Progress notes must include functional outcomes and home program assignment. Mindbowser custom EHR: enforces supervision flag, templates require functional outcome statement and home program field.
5. Illinois: SLP license required, indirect supervision only (supervision model enforced by state board). Progress notes per Illinois SLP standards. Mindbowser custom EHR: enforces indirect-only model, blocks direct supervision workflows.
For a multi-site SLP clinic (say, three clinics in CA, NY, and FL), off-the-shelf software can’t handle this. You’d have to train staff in three different documentation standards, manually monitor compliance, and handle state board audits manually. Custom EHR bakes per-clinic rules into the system: log in at the CA site, direct/indirect flag appears; log in at the NY site, direct supervision only; log in at the FL site, functional outcome field is mandatory.
And when a state board auditor shows up, you pull the documentation in minutes, not days. State boards audit documentation. HIPAA audits documentation. Both are expensive and disruptive. Custom EHR keeps you audit-ready in minutes, not days.
Talk to Our Team About Your SLP EHR Requirements
When Should You Build Custom vs. Buy Off-the-Shelf SLP Software?
Three questions:
Question 1: Clinic size and structure. Under 10 clinicians, single location, broad patient mix (pediatric and adult, no specialty focus): off-the-shelf works. You can absorb the manual insurance work and compliance overhead. Ten to twenty clinicians, multi-site, specialty focus (aphasia specialists, dysphagia clinic, pediatric SLP only): it gets gray.
Twenty-plus clinicians, five-or-more sites, heavy specialty focus, and multi-site referral coordination: custom usually wins. The administrative burden of managing state rules across sites and insurance pre-auth across payers outweighs the upfront build cost.
Question 2: State licensing complexity. Single low-regulation state (Texas deregulated, or California with flexible supervision): off-the-shelf is sufficient. Multi-state network with different supervision models per state: custom is necessary. Compliance enforcement across state lines is not a spreadsheet problem; it is a system design problem.
Question 3: Insurance payer mix. Seventy percent or more private payer (self-pay, BlueCross, United, etc. with flexible pre-auth): off-the-shelf handles this fine. Pre-auth labor is low. Sixty percent or more Medicare and Medicaid (high pre-auth burden): custom EHR pays for itself in pre-auth automation savings alone. Mix of five or more payers with conflicting rules: custom required.
Build vs. buy scenarios:
| Scenario | Size | State complexity | Payer mix | Call |
|---|---|---|---|---|
| Small, simple | <10 clinicians, 1 site, broad mix | Low (1 state, flexible regs) | Mostly private pay | Buy off-the-shelf |
| Medium, moderate | 15-20 clinicians, 2-3 sites, specialty focus | Moderate (1-2 states) | Mixed (40% Medicare/Medicaid) | Hybrid (off-the-shelf + custom pre-auth module) |
| Large, high complexity | 25+ clinicians, 5+ sites, multi-specialty | High (3+ states, different rules per state) | 70%+ Medicare/Medicaid | Build custom |
Most SLP clinics underestimate their complexity. But custom isn’t right for everyone. The three questions above tell you which side you land on.
What Does a Custom SLP EHR Cost, and When Does It Pay Back?
Let’s talk real numbers.
Off-the-shelf cost: $165-200/clinician/month. For a 15-clinician clinic, that is $29,700-36,000 per year.
Custom EHR cost: $80,000-250,000 upfront (basic build to feature-rich), plus $5,000-15,000 per month in ongoing support (so $60,000-180,000 per year). Upfront varies by complexity: basic pre-auth + scheduling automation is $80,000; feature-rich with multi-site, FHIR integration, and advanced reporting is $180,000-250,000.
ROI scenario: 15-clinician SLP clinic, 60% Medicare/Medicaid, multi-site, high pre-auth volume.
Off-the-shelf annual cost: $36,000 (15 clinicians at $200/mo)
Manual pre-auth labor: 15 clinicians × 8 hours per week × 50 weeks per year × $35/hour all-in wage = $262,500/year
Custom EHR build (120K amortized over 3 years): $40,000/year
Custom EHR support: $96,000/year
Automated pre-auth labor: 3 hours per week × 50 weeks × $35/hour = $5,250/year
Claim denial rate improvement (2% better accuracy): $500,000 annual billings × 2% = $10,000/year savings
Comparison:
- Off-the-shelf annual cost: $36,000 + $262,500 labor = $298,500
- Custom annual cost: $40,000 + $96,000 + $5,250 labor = $141,250
- Annual savings: $157,250
- Payback period: 9 months (custom upfront cost divided by monthly savings)
Most SLP clinics see payback in 6-18 months. One multi-site network we worked with reported pre-auth turnaround cut from 60 days to 3 days, claim denial rate dropped from 12% to 2.1%, and clinician admin load fell from 10 hours per week to 3.5 hours per week. Annual ROI: $280,000+. Payback: 5.5 months.
The 9-month payback in the scenario above sounds clean. Let me be more precise: that’s the 60% Medicare/Medicaid, 15-clinician scenario with high pre-auth volume. Private-pay-heavy clinics typically see 18-24 months. The math still works, but the timeline stretches. And the compliance savings (avoided state board audit costs, reduced denial appeals) are not in that model at all. Add those and payback compresses for most clinics regardless of payer mix.
How Do You Implement a Custom SLP EHR? (20-Step Checklist)
If you have decided custom is right, here is the phased rollout.
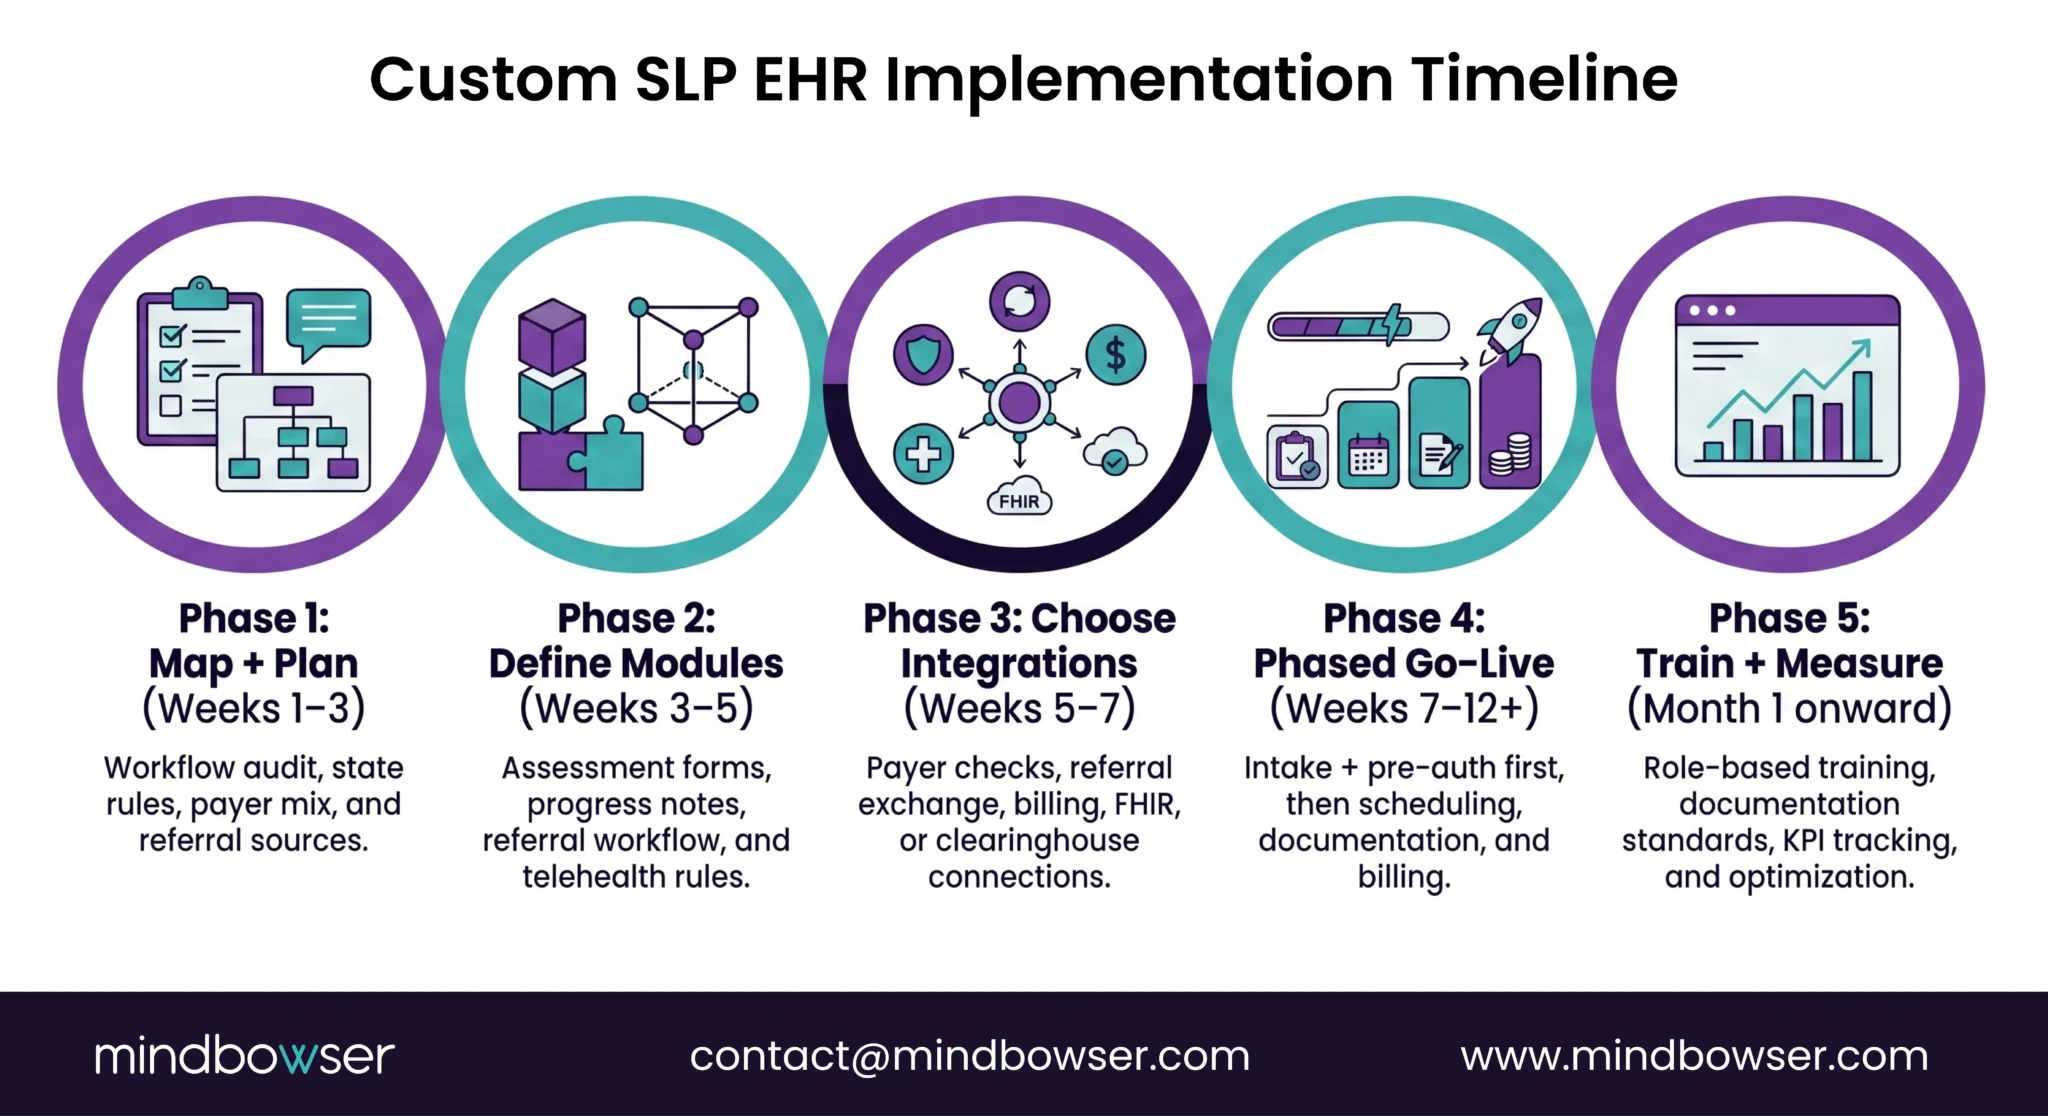
Phase 1 (weeks 1-3): Map and plan
- Document your current workflow: patient intake → insurance pre-auth → scheduling → session → progress note → billing → follow-up. Note which steps are in spreadsheets, which are fragmented across systems.
- Map state licensing requirements: does your state license SLPs? What supervision model is required? What documentation standard? Get this from your state board website.
- List your top 10 insurance payers and pull their SLP pre-auth rules: prior auth required? Medical necessity threshold? CPT code limits?
- Map referral sources: which specialists send you SLP cases (ENT, neurology, pediatrics)? What data do they need back?
Phase 2 (weeks 3-5): Define modules
- Assessment forms library: what do you actually use? GFTA-3, CELF-5, dysphagia screening, aphasia batteries. Custom EHR templates match your forms.
- Progress note template: SOAP format? Functional outcome tracking required? Home practice assignment? Define this upfront.
- Referral workflow: how should inbound ENT referrals land in your EHR? What auto-populates? What requires manual entry?
- Telehealth rules: can you document tele-sessions? Does your state allow remote SLP? What billing modifiers apply?
Phase 3 (weeks 5-7): Choose integrations
- EHR and practice management: if you keep a separate PM system, how do appointments sync?
- EHR and insurance verification: which payer APIs will you connect to (state Medicaid, CMS Medicare, private payer networks)?
- EHR and referral network: can you receive referrals via fax, HL7, or FHIR API?
- EHR and billing: auto-submit claims to your clearinghouse or directly to payers?
Phase 4 (weeks 7-12): Phased go-live
- Phase 1 go-live (week 1): intake and insurance pre-auth only. Highest pain, lowest risk.
- Phase 2 go-live (weeks 3-4): add scheduling and session documentation.
- Phase 3 go-live (weeks 6-8): add billing and claims tracking.
- Phase 4 (month 2+): advanced features (telehealth, multi-site sync, analytics).
Phase 5 (month 1+): Train and measure
- EHR usability training for clinicians: demo during staff meetings, hands-on with real workflows.
- Insurance compliance training: how to verify pre-auth, what to do if denied, appeal workflow.
- Documentation standards: how to document state-specific supervision, home practice assignment.
- KPI tracking: pre-auth turnaround (target <1 day vs. current 5-7 days), claim denial rate (target <3% vs. current 12-15%), clinician admin hours (target 2 hrs per patient per week vs. current 4-5), patient satisfaction (NPS on scheduling and tele-session quality).
Timeline: 6-12 months from requirements to full go-live. Off-the-shelf is 2-4 weeks; custom requires planning.
But the phased approach means your clinic is never fully offline. Each phase goes live before the next begins.
Which Accelerators Speed Up Custom SLP EHR Development?
When SLP clinics build custom, certain technology choices speed up delivery and reduce risk.
- Patient Questionnaire Form automates intake. Instead of paper or manual data entry, GFTA-3, CELF-5, and dysphagia screening forms go digital. Auto-populate EHR fields. No manual data re-entry. Faster chart review before the session. One SLP network reported intake time cut from 45 minutes to 15 minutes.
- Patient Referral Manager tracks inbound referrals end-to-end. ENT orders SLP evaluation: referral lands in the EHR, auto-routes to an available SLP, status tracked from intake to discharge, summary sent back to ENT automatically. Zero lost referrals. Zero follow-up phone calls. Multi-site referral network syncs across locations in real-time.
- AI Medical Summary auto-generates progress notes. Clinician documents session observations in freeform notes. AI drafts a standardized SOAP note in real-time. Clinician reviews, edits, approves. Documentation time cut from 30 minutes per patient to 15 minutes. Consistency improves because the template structure is enforced.
- PHISecure handles HIPAA and state compliance. HIPAA audit trails: who accessed what record, when, why. State board audit-ready in minutes. Bloodborne pathogen training logs (for SLP with dysphagia). Compliance tracking automated.
- FHIR integration connects your SLP EHR to hospital systems. If 30%+ of referrals come from hospital SLP departments or medical providers at health systems, FHIR auto-populates referral data, eliminates duplicate entry, and speeds intake. If most patients are direct-access (walk-in), FHIR is lower priority.
- Real-world example. Multi-site SLP clinic (28 clinicians across 4 locations) built custom EHR on a FHIR-native stack with Patient Questionnaire Form, Patient Referral Manager, and AI Medical Summary. Result: intake time from 45 minutes to 15 minutes, referral-to-scheduling from 7 days to 1 day, clinician documentation time from 30 minutes to 15 minutes per patient. Annual clinician time savings: 2,800 hours (equivalent to 1.3 FTE clinicians). Annual cost savings: $140,000+ in administrative overhead.
How Do You Choose the Right EHR Path for Your SLP Practice?
Here is the synthesis.
If you are spending more than 8 hours per week on insurance pre-auth and progress note documentation, the problem is not your software. It is your workflow design. Off-the-shelf software patches symptoms. Custom EHR redesigns the entire intake-to-billing workflow. You end up with automation where there was manual work, compliance enforcement where there was spreadsheet tracking, and referral coordination that actually works.
And state licensing variation adds a layer most clinics miss until a state board audit arrives. You end up managing state rules in spreadsheets, tracking supervision models in staff emails, documenting compliance manually. Custom EHR bakes all of it into the system.
Most importantly: ROI window is 6-18 months for SLP clinics that build custom (via pre-auth automation savings, billing accuracy gains, and clinician retention). Clinicians burn out when documentation eats their day. Custom EHR gives them their time back.
The question is not “Can we afford custom?” It is “Can we afford NOT to build?”
And for most clinics running 20+ clinicians across multiple states with a heavy Medicare/Medicaid book, the answer is already clear.
If your clinic checks two of three boxes below, custom is worth exploring:
- You operate across two or more states with different supervision rules.
- Your insurance payer mix is 70%+ Medicare and Medicaid.
- You have 20+ clinicians across multiple sites.
A custom SLP EHR should support the CPT codes used across speech-language pathology evaluations, treatment, re-evaluations, and applicable telehealth workflows. It should also account for payer and state-specific billing requirements so teams can reduce coding errors and avoid using workflows that fall outside applicable scope rules.
A custom SLP EHR can integrate with payer verification APIs, including Medicaid, Medicare-related payer workflows, and private payer platforms. During intake, the system can check coverage, medical necessity requirements, prior authorization rules, authorization status, and related eligibility details before scheduling.
This reduces manual calls and gives staff a clearer go or no-go signal before the first visit is booked.
Yes. A custom SLP EHR can support HIPAA-compliant video, real-time documentation, telehealth billing workflows, and configurable state-specific licensing or supervision rules.
Where applicable, telehealth modifiers and claim-routing logic can also be built into the workflow so staff do not have to manage telehealth and in-person billing separately.
A custom SLP EHR typically takes 6–12 months from requirements and design through development, testing, and phased rollout. Projects using pre-built healthcare modules and accelerators may be completed in approximately 4–6 months, depending on scope, integrations, and data migration complexity.
Off-the-shelf platforms generally go live faster because they require significantly less customization.
A speech therapy EHR is built around clinical SLP workflows, including assessment forms, SLP-specific documentation, billing workflows, supervision tracking, prior authorization, and referral coordination.
A general practice management system focuses primarily on administrative functions such as scheduling, billing, claims, and reporting. It may not support SLP-specific clinical or regulatory workflows without additional configuration or customization.
It depends on your referral sources. If a significant share of referrals comes from hospital departments or medical providers using systems such as Epic or Cerner, EHR integration can reduce manual data entry and speed up intake.
FHIR or other interoperability methods can help exchange referral data, clinical information, and follow-up documentation. If most patients are direct-access, hospital EHR integration may be a lower priority.
Custom EHR implementation is usually phased. A common rollout starts with intake and prior authorization, followed by scheduling, documentation, billing, and advanced features.
Staff are trained before each phase goes live, which helps reduce disruption and allows workflow issues to be resolved incrementally rather than changing the entire system at once.





