














 BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR
























TL;DR
- CDSS stands for Clinical Decision Support System. It is software that provides a clinician with relevant, patient-specific information at the moment they are making a decision, within the system they are already working in.
- Not a report they open later. A prompt that arrives while the decision is still open. That is the whole definition.
- The rest of this page is what it means in practice: the types, what it looks like in nursing and in physician workflows, what separates the ones clinicians use from the ones they switch off, and what it takes to build one.
What CDSS Stands For, and What the Words Are Doing

Clinical Decision Support System. Each word is load-bearing:
- Clinical: it operates on patient data in a care setting, which is why it carries regulatory weight that a business dashboard does not.
- Decision: it attaches to a specific choice: order this test, prescribe this dose, escalate this patient. A system that displays information without attaching to a decision is a report.
- Support: it informs a clinician; it does not decide. This distinction is not a courtesy. It is the legal line that determines whether the FDA regulates your software as a medical device.
- System: it is infrastructure with a data feed, a rules or model layer, and a delivery surface, not a feature.
You will also see CDS (clinical decision support), which refers to the practice, and CDSS, which refers to the software. In everyday use, they are interchangeable.
The plain-language version: cdss meaning is just “software that hands a clinician the right patient info at the moment they’re deciding, not a report they have to go dig up later.” When someone searches cdss medical, they’re almost always asking what the abbreviation means in a clinical setting, and the answer is the same thing: Clinical Decision Support System, the layer that supports a clinician’s judgment rather than replacing it. The cds vs cdss distinction that trips people up: CDS is the practice (the discipline of surfacing the right information at the right moment), CDSS is the software that does it. In everyday use people say them interchangeably, but CDS is the “what,” CDSS is the “how.”
What a CDSS Actually Does
Four jobs cover almost every real deployment:
| Job | What it looks like | Example |
|---|---|---|
| Catch something missing | Flags a required input that has not been supplied | Pre-operative labs not ordered before surgery |
| Catch something dangerous | Flags an interaction or contraindication | Drug-drug interaction at prescribing |
| Recommend a next step | Suggests an action based on guideline logic | Screening due based on age and history |
| Scores a risk | Produces a probability to prioritize attention | Readmission risk at discharge |
The first two are checks. The second two are predictions. That difference matters more than any other distinction in this field, and we come back to it below.
CDSS in Healthcare: What CDSS Healthcare Means and Where It Sits
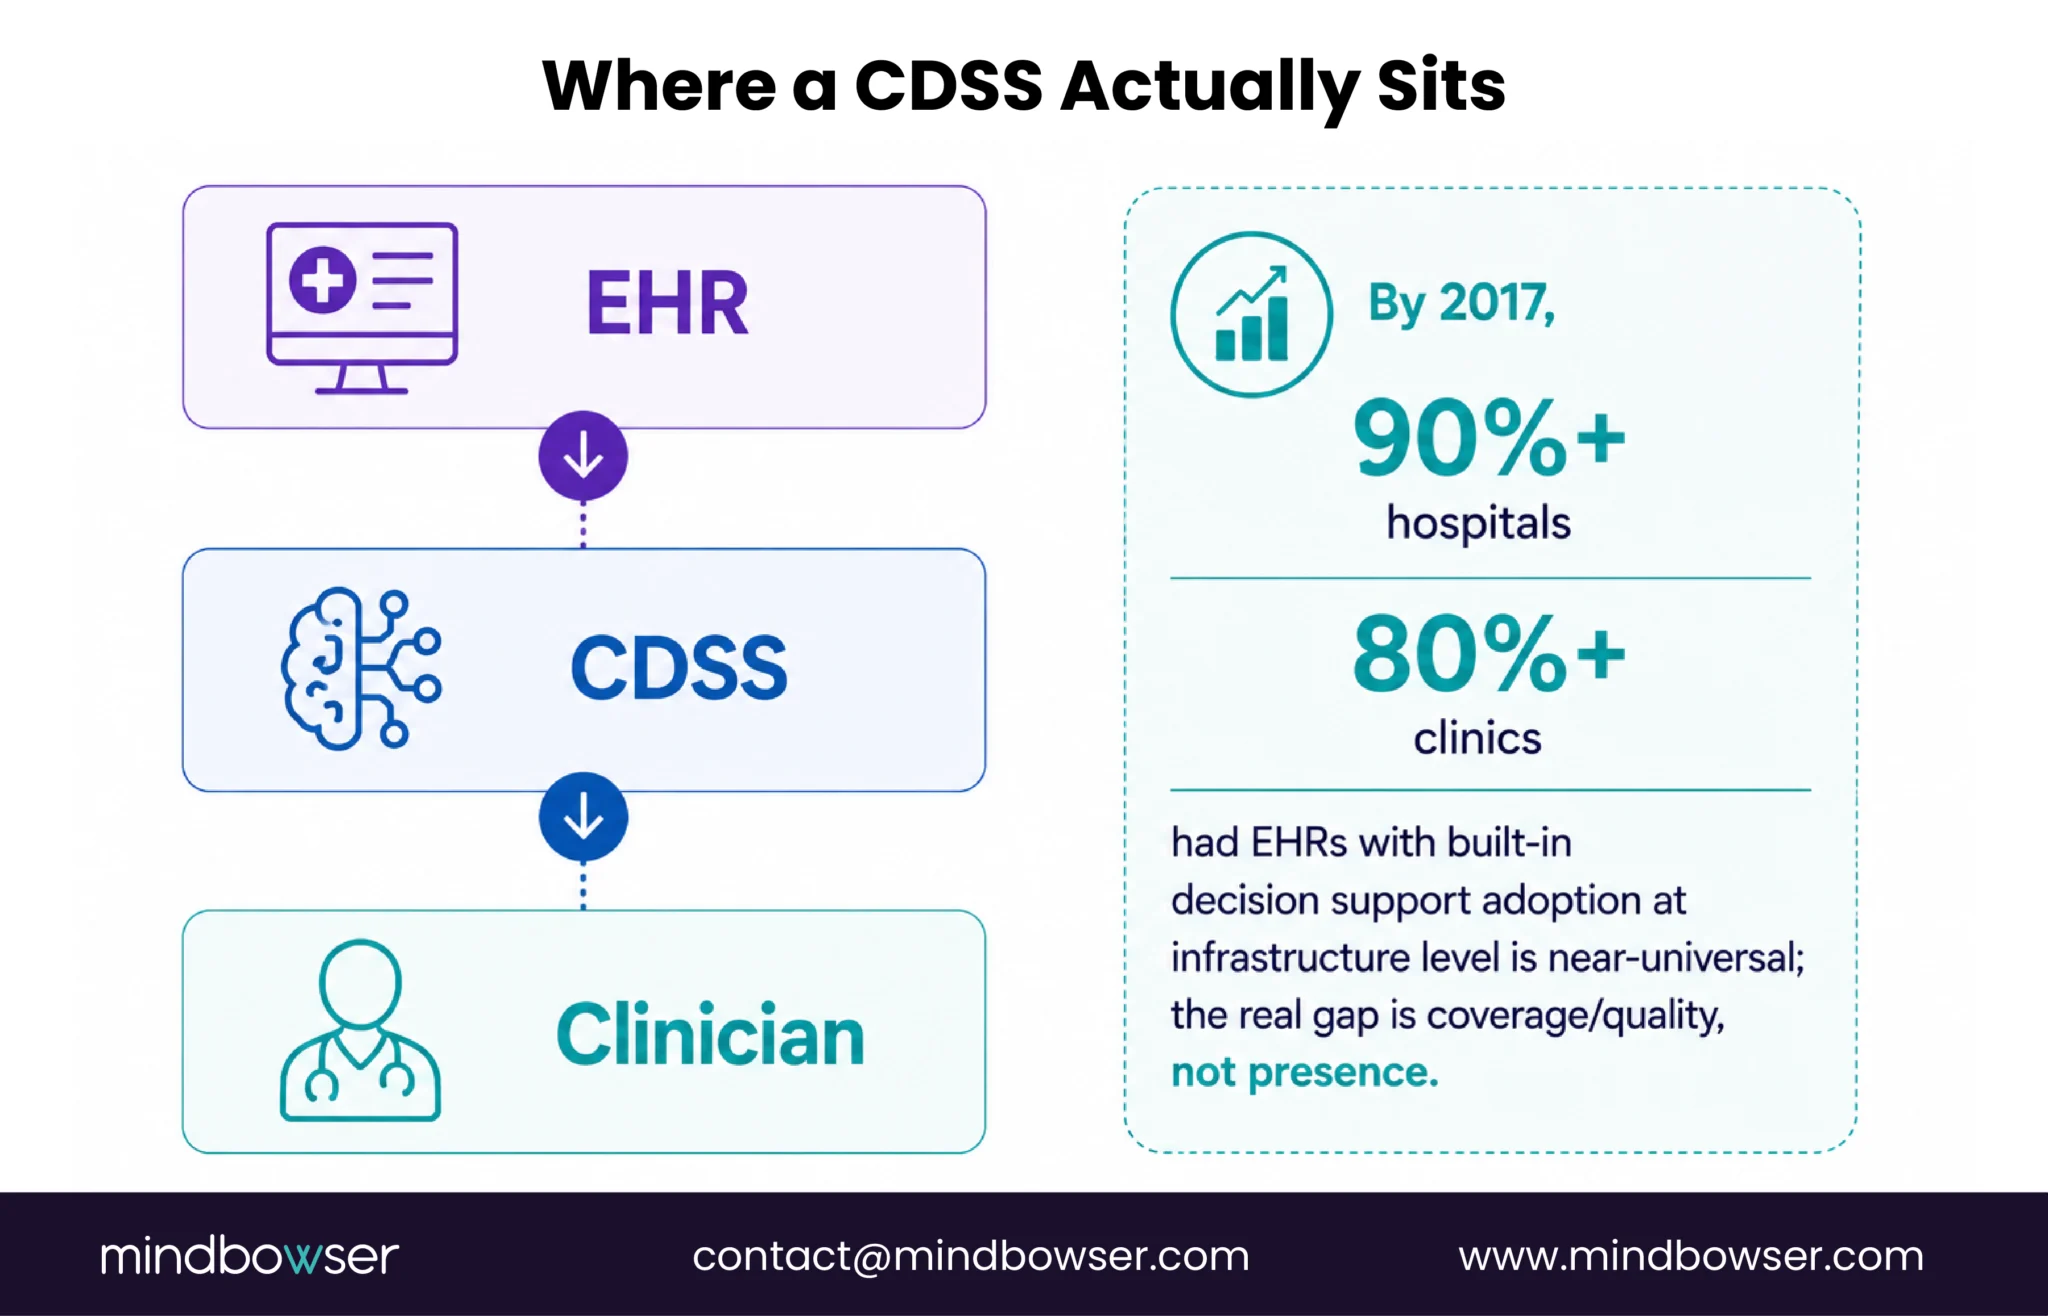
A CDSS rarely stands alone. It lives inside the EHR, because that is where the clinician already is.
Adoption is effectively universal at the infrastructure level. By 2017, more than 90% of hospitals and 80% of clinics had EHRs with some form of clinical decision support built in. So for most organizations, the question is not whether they have a CDSS. They do. The question is whether it is any good, and whether it covers the decisions that actually matter to them.
That is why “we need a CDSS” is rarely the real requirement. The real requirement is usually one of:
- The native EHR decision support does not cover our specialty or our protocol
- Our alerts fire so often that clinicians dismiss them without reading
- We have a model that predicts something useful and no way to get it in front of a clinician at the right moment
Types of CDSS
The classification most textbooks lead with is knowledge-based versus non-knowledge-based:
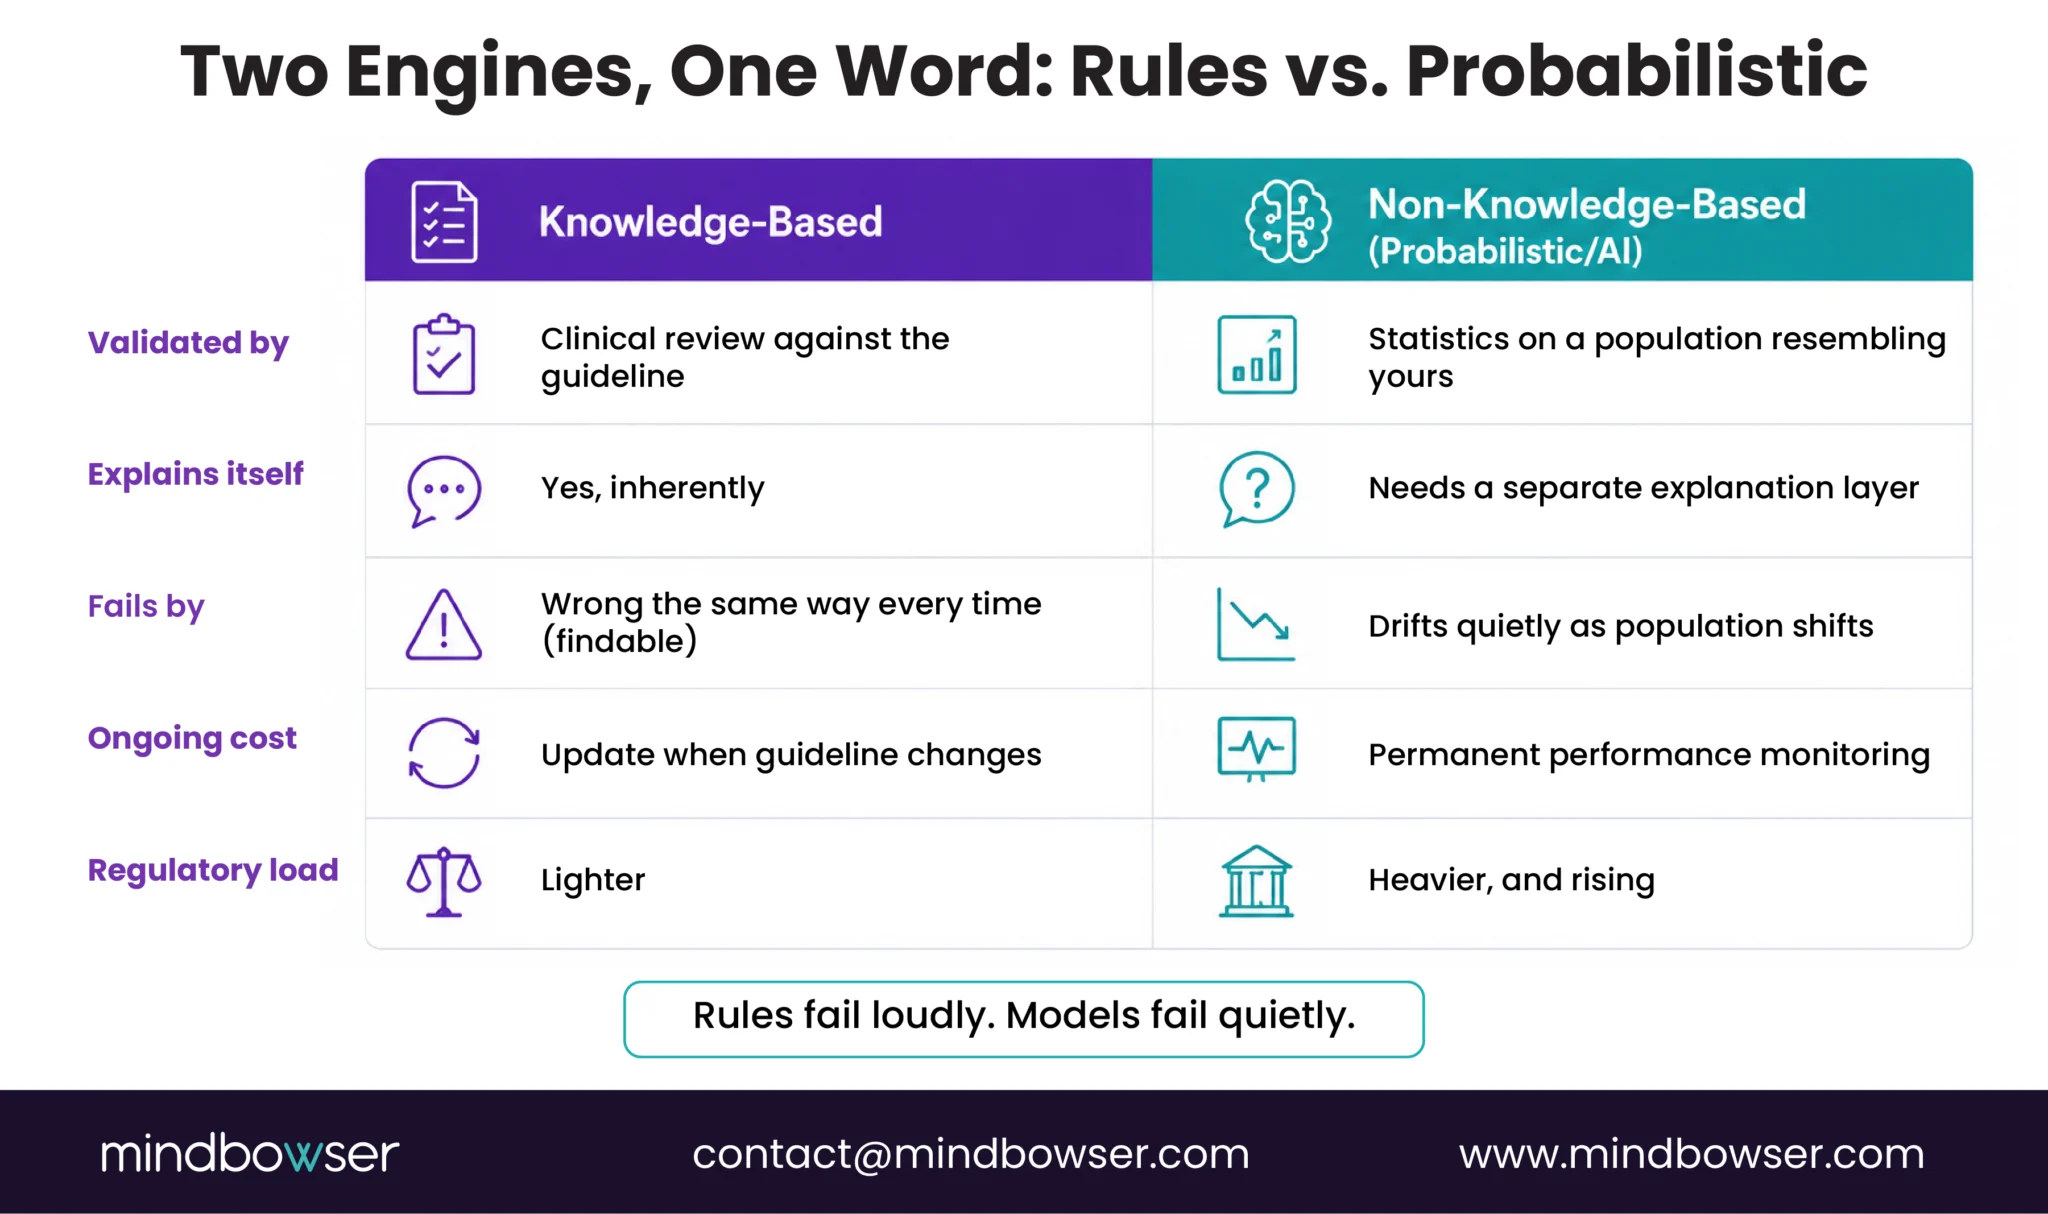
Knowledge-based CDSS encodes explicit clinical rules. Drug X interacts with drug Y. This procedure requires these three labs. A clinician wrote the rule, a clinician can read it, and a clinician can audit it.
Non-knowledge-based CDSS (also called probabilistic, or increasingly just AI CDS) learns patterns from historical data and outputs a score. Nobody wrote the rule. It emerged from a training set.
There are further splits: active versus passive (does it interrupt, or wait to be consulted), integrated versus standalone (does it live in the EHR, or in a separate application that requires manual data entry).
We break all of these down with the practical trade-offs in the types of clinical decision support systems.
The distinction that changes your build is knowledge-based versus probabilistic, because they differ on every axis your governance committee will ask about:
CDSS in Nursing
Nursing decision support gets less attention than physician-facing CDS and is often where the clearest wins sit, because nursing work is more protocolized and the decision points are more predictable.
Nursing-process CDSS is typically designed around the five steps of the nursing process: assessment, diagnosis, planning, intervention, and evaluation. In practice, that means things like risk screening prompts at admission, protocol reminders during a shift, and documentation checks before handoff.
The design constraint is different from physician CDS in one important way. Nurses are interrupted constantly, and an alert that adds another interruption to a shift that already has too many will be dismissed faster than a physician alert would be. Tiering and routing matter more here, not less.
Three patterns that tend to hold up in nursing workflows:
- Screen at admission, not mid-shift: Risk screening prompts land better at a moment the nurse is already gathering structured information, rather than interrupting an active task.
- Route by who can act: An alert that a nurse cannot resolve without paging someone should go to the person who can resolve it. Sending it to the nurse anyway trains them to dismiss.
- Check before handoff, not during care: Documentation completeness prompts work at the shift boundary, where the nurse is already reviewing, and fail during care delivery, where they are not.
The common thread is that nursing CDS works when it attaches to a moment already built into the shift, and fails when it creates a new one.
CDSS vs EHR vs CPOE: The Three That Get Confused
These get used interchangeably, and they are three different things. Getting them straight saves a lot of scoping confusion:
| What it is | What it does | |
|---|---|---|
| EHR | The record system | Stores the chart. The system of record for patient data |
| CPOE | Computerized Provider Order Entry | The ordering surface. Where a clinician places an order electronically |
| CDSS | Decision support | The intelligence layer that reacts to what is in the EHR, often at the moment of CPOE, and tells the clinician something useful |
The practical relationship: CDSS reads the EHR and usually fires at CPOE. That is why an order-entry moment is the single most common trigger point for clinical decision support, and why CDS that is not wired into the ordering workflow tends to go unused.
It also explains a common procurement mistake. Buying a CPOE upgrade does not get you decision support, and buying a CDSS without access to structured EHR data gets you a system with nothing to reason over. We cover the integration requirement in why clinical decision support apps fail without deep EHR integration and the EHR side in the role of the EHR in clinical decision support.
Build and Integrate a CDSS That Works With Your EHR
Why Most CDSS Get Ignored
This is the part that decides whether a CDSS is worth building.
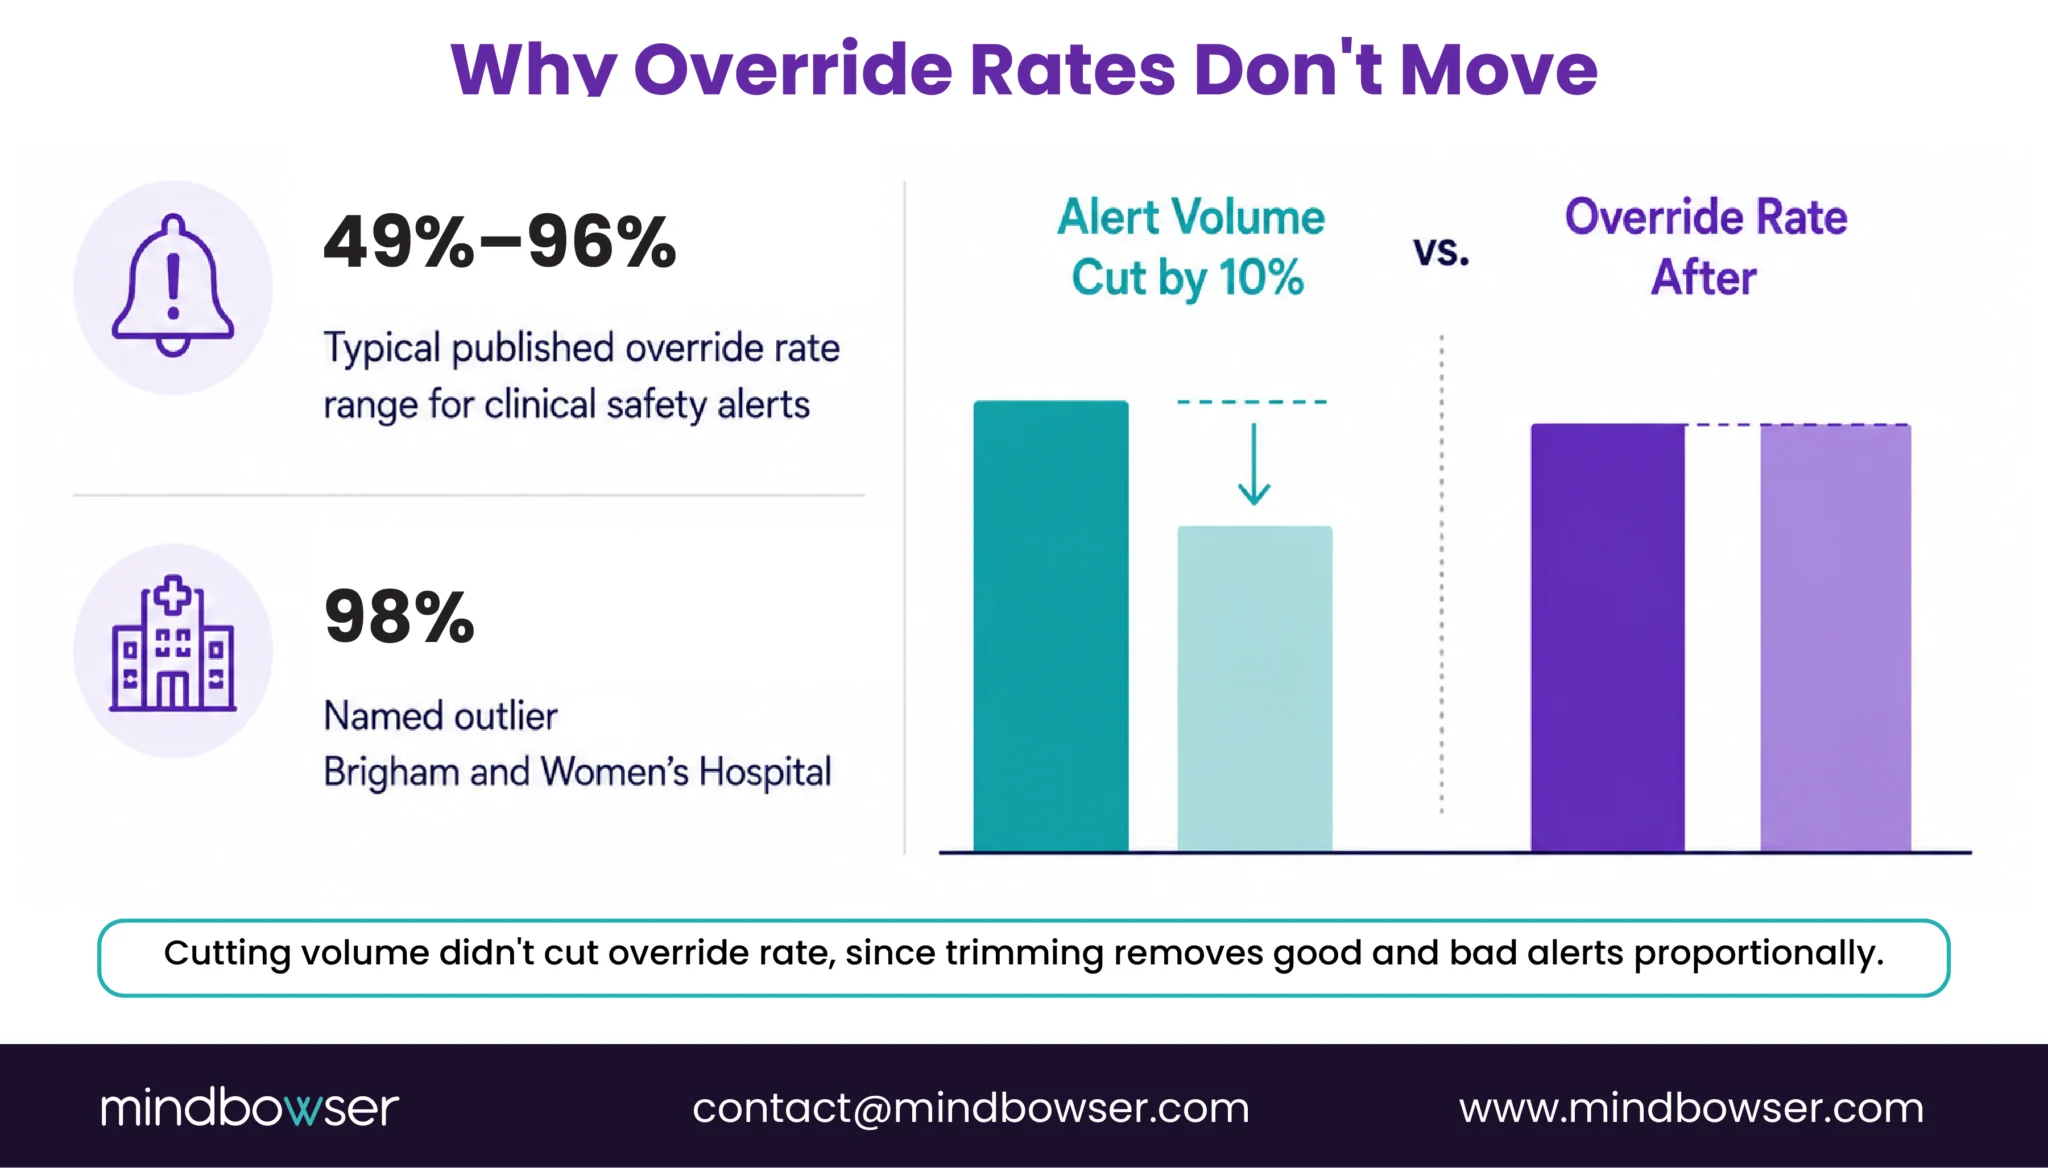
Published override rates for clinical safety alerts run from 49% to 96%. At Brigham and Women’s Hospital, clinicians were overriding 98% of alerts.
The instinct is to fix that by having fewer alerts. It does not work: in one study, cutting alert volume by 10% left the override rate unchanged. Clinicians already treating alerts as noise kept treating them as noise.
The reason is that trimming across the board removes good alerts and bad alerts in the same proportion. To cut selectively you need to know which alerts are bad, and that requires capturing why clinicians dismiss them. Most systems do not. Every dismissal looks identical, so a genuinely useless alert and a good alert firing on the wrong patients produce the same data: dismissed.
The HL7 CDS Hooks specification has a mechanism for this called `overrideReasons`. When a card includes them, the clinician must pick a reason before dismissing, and that reason comes back to the service. It turns dismissals into a tuning dataset. It is optional; most implementations skip it, and skipping it is the single most common reason a CDSS decays.
Full treatment in our guide to reducing CDSS alert fatigue.
Is a CDSS Regulated?
Sometimes. It depends on design decisions you make early.
Section 3060 of the 21st Century Cures Act excludes certain clinical decision support software from device regulation. The exclusion sits at Section 520(o)(1)(E) of the FD&C Act and rests on a four-part test, all four parts of which have to be met.
The one that decides most real cases: the software has to let the healthcare professional independently review the basis for its recommendation, so they are not relying primarily on it. A system that shows a score with no visible reasoning fails that by construction. One that shows the score alongside its inputs, legibly, in the seconds a clinician actually has, does not.
The FDA issued revised guidance on January 6, 2026, re-issued January 29, replacing the September 2022 version, and the revision widens the set of tools falling outside device oversight.
Two other threads worth knowing:
- ONC HTI-1 created a Decision Support Interventions criterion at 45 CFR 170.315(b)(11), requiring certified health IT to surface structured “source attributes”: 13 for evidence-based interventions, 31 for predictive ones. Four times the transparency load for a model versus a rule.
- CMS-1850-P, published July 7, 2026, proposes a “Software as a Medical Service” payment category. Comments close August 31, 2026.
One thing to strike from any older business case: the CMS Appropriate Use Criteria program was rescinded at 42 CFR 414.94 effective January 1, 2024. It was never enforced.
More detail in our guide to FDA clinical decision support regulations.
What a Working CDSS Looks Like
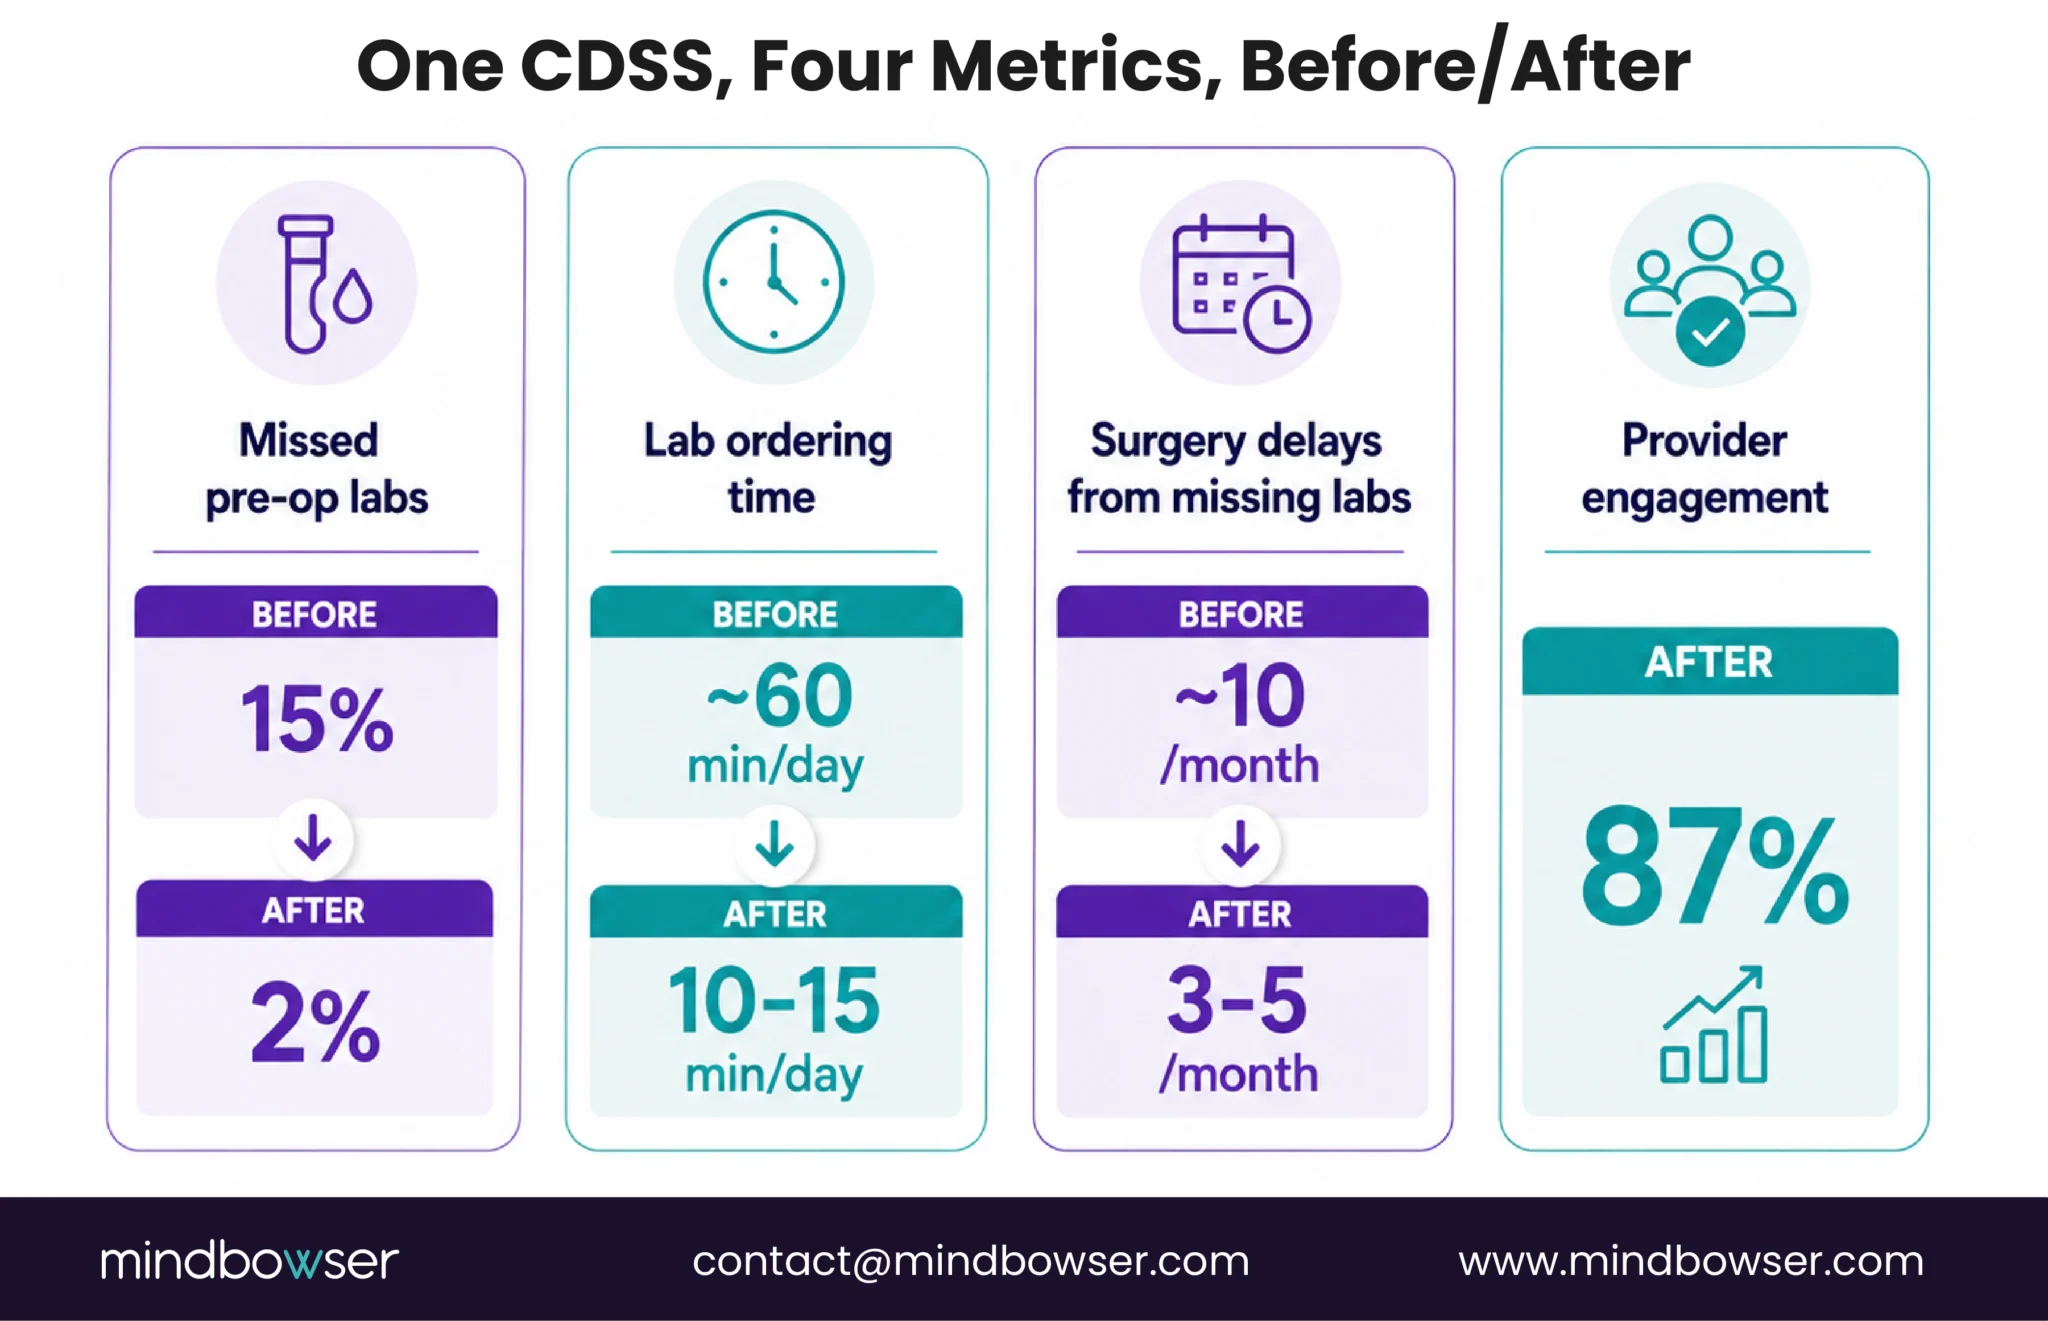
A perioperative readiness platform was losing surgical slots to pre-operative labs that turned out to be missing or out of date on the day of surgery, when the only options left were delay or proceed without the result.
We built a CDS Hooks service registered against the order-signing event in Epic. When a surgeon signs a pre-operative order set, the service checks the patient’s lab history against that procedure’s requirements and returns anything missing as one-click orders, inside the workflow, before the order is committed.
- Missed pre-operative labs fell from 15% to 2%
- Lab ordering time dropped from about 60 minutes a day to 10 to 15
- Surgery delays from missing labs went from around 10 a month to 3 to 5
- Provider engagement with the tool: 87%
The engagement number is the one that matters. It held because the prompt arrived at the moment of ordering rather than after, carried an action that took one click, and was narrow enough to be almost always right when it appeared.
More worked cases in clinical decision support system examples, and the build detail in CDS Hooks technical implementation.
What It Takes to Build One
Short version, in the order the questions actually come up:
1. Name the decision and the moment: Not “improve medication safety.” Rather: at the instant a prescriber signs this order, what should they know?
2. Check the data is structured: A rule keyed on structured allergy data does nothing for an allergy recorded in a free-text note.
3. Pick rule or model, honestly: If a defensible explicit rule exists, use it. Models earn their complexity only where no such rule exists.
4. Design the override path before the alert: Structured dismissal reasons, or you will have no way to improve it.
5. Budget for the latency: An interactive hook has roughly 500 milliseconds round trip before the EHR times out or the clinician has moved on.
6. Decide the regulatory posture at design time, not at launch.
Cost and timeline vary enough that a range here would mislead. We break down the real drivers in the CDS implementation budget guide, and the buy-versus-build question in the clinical decision support software buyer’s guide.
Conclusion
Everything on this page comes back to one question: does the information arrive while the decision is still open, inside the workflow the clinician is already in? A CDSS that passes that test gets used. One that shows up after the decision, or outside the tool the clinician is already working in, gets ignored, no matter how accurate it is.
That’s also the honest answer to “do we need a CDSS.” Most organizations already have one, buried in the EHR. The real question is whether it covers the decisions that matter to your specialty, whether clinicians trust it enough to act on it, and whether you’re capturing why they override it. Get those three right and the rest, rule-based or model-driven, active or passive, is implementation detail.
Clinical Decision Support System. Software that delivers patient-specific information to a clinician at the point where a clinical decision is being made, inside the system they are already using.
It is the layer that turns patient data into a prompt at the moment of a decision: flagging a missing lab before surgery, a drug interaction at prescribing, a screening that is due, or a risk score at discharge. Most EHRs ship with some form of it built in.
CDSS is the medical abbreviation for Clinical Decision Support System. You will also see CDS, which refers to clinical decision support as a practice rather than the software.
Nursing-focused decision support, usually built around the five steps of the nursing process: assessment, diagnosis, planning, intervention, and evaluation. Common uses are risk screening prompts at admission, protocol reminders during a shift, and documentation checks before handoff.
Knowledge-based systems, which use explicit clinical rules written and reviewed by clinicians, and non-knowledge-based (probabilistic or AI) systems, which learn patterns from historical data and output a score. They differ in how they are validated, how they explain themselves, how they fail, and how much regulatory scrutiny they attract.
Some is. The 21st Century Cures Act excludes clinical decision support software meeting a four-part test, the deciding element usually being whether a clinician can independently review the basis for the recommendation. The FDA’s current guidance is dated January 6, 2026.
Because alert quality decays without a feedback channel. Published override rates run 49% to 96%. Cutting alert volume alone does not help; one study found a 10% reduction left the override rate unchanged. Capturing structured reasons for dismissals is what makes selective tuning possible. —





