














 BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR
























TL;DR
- CPT 99495 pays $220.11 and needs a face-to-face visit inside 14 days. CPT 99496 pays $298.60 and needs it inside 7. Both are 2026 national averages in a non-facility setting and both vary by locality. Both codes need interactive contact inside 2 business days of discharge.
- In 2024, against that year’s published rates, two haircuts stacked. Locality took the measured allowed amount about 10% below the published national rate on both codes, to $213.79. Coinsurance, deductible and sequestration then took it to the $166.17 Medicare paid.
- Two documented unsuccessful contact attempts do not sink the claim. CMS says the opposite: make 2 or more, document them, meet the other requirements, and you may report the service. The deadline that actually kills claims is the face-to-face visit.
- You do not have to wait until day 30 to bill. The date of service is the face-to-face visit, and CMS says you need not hold the claim. The most-read provider page on this topic still says otherwise.
- CMS publishes a 42-code table of care management services billable concurrently with TCM, the CCM family among them, and tells you to report medically necessary E/M separately.
A TCM claim almost never dies because someone chose the wrong code.
In outcomes research on Medicare claims, the same shape kept appearing: the patients readmitted inside 30 days were rarely the ones who got worse care in the hospital. They were the ones nobody reached afterward. TCM exists because CMS arrived at the same conclusion and attached a payment to it.
CMS wrote countable deadlines: 2 business days, 7 or 14 calendar days, 30 days total. What makes the money disappear is that the whole episode depends on knowing a discharge happened, and most practices find out late. Everything below is the code detail, the payment, what the episode requires, when you can bill, and where the claim breaks. For the readmission-penalty and risk-contract framing, transitional care management under value-based contracts covers that lens.
What CPT 99495 and 99496 Pay For, and Which Discharges Qualify
TCM covers the coordination work in the 30 days after a patient leaves an inpatient setting. Two CPT (Current Procedural Terminology) codes carry it, split on medical decision-making complexity.
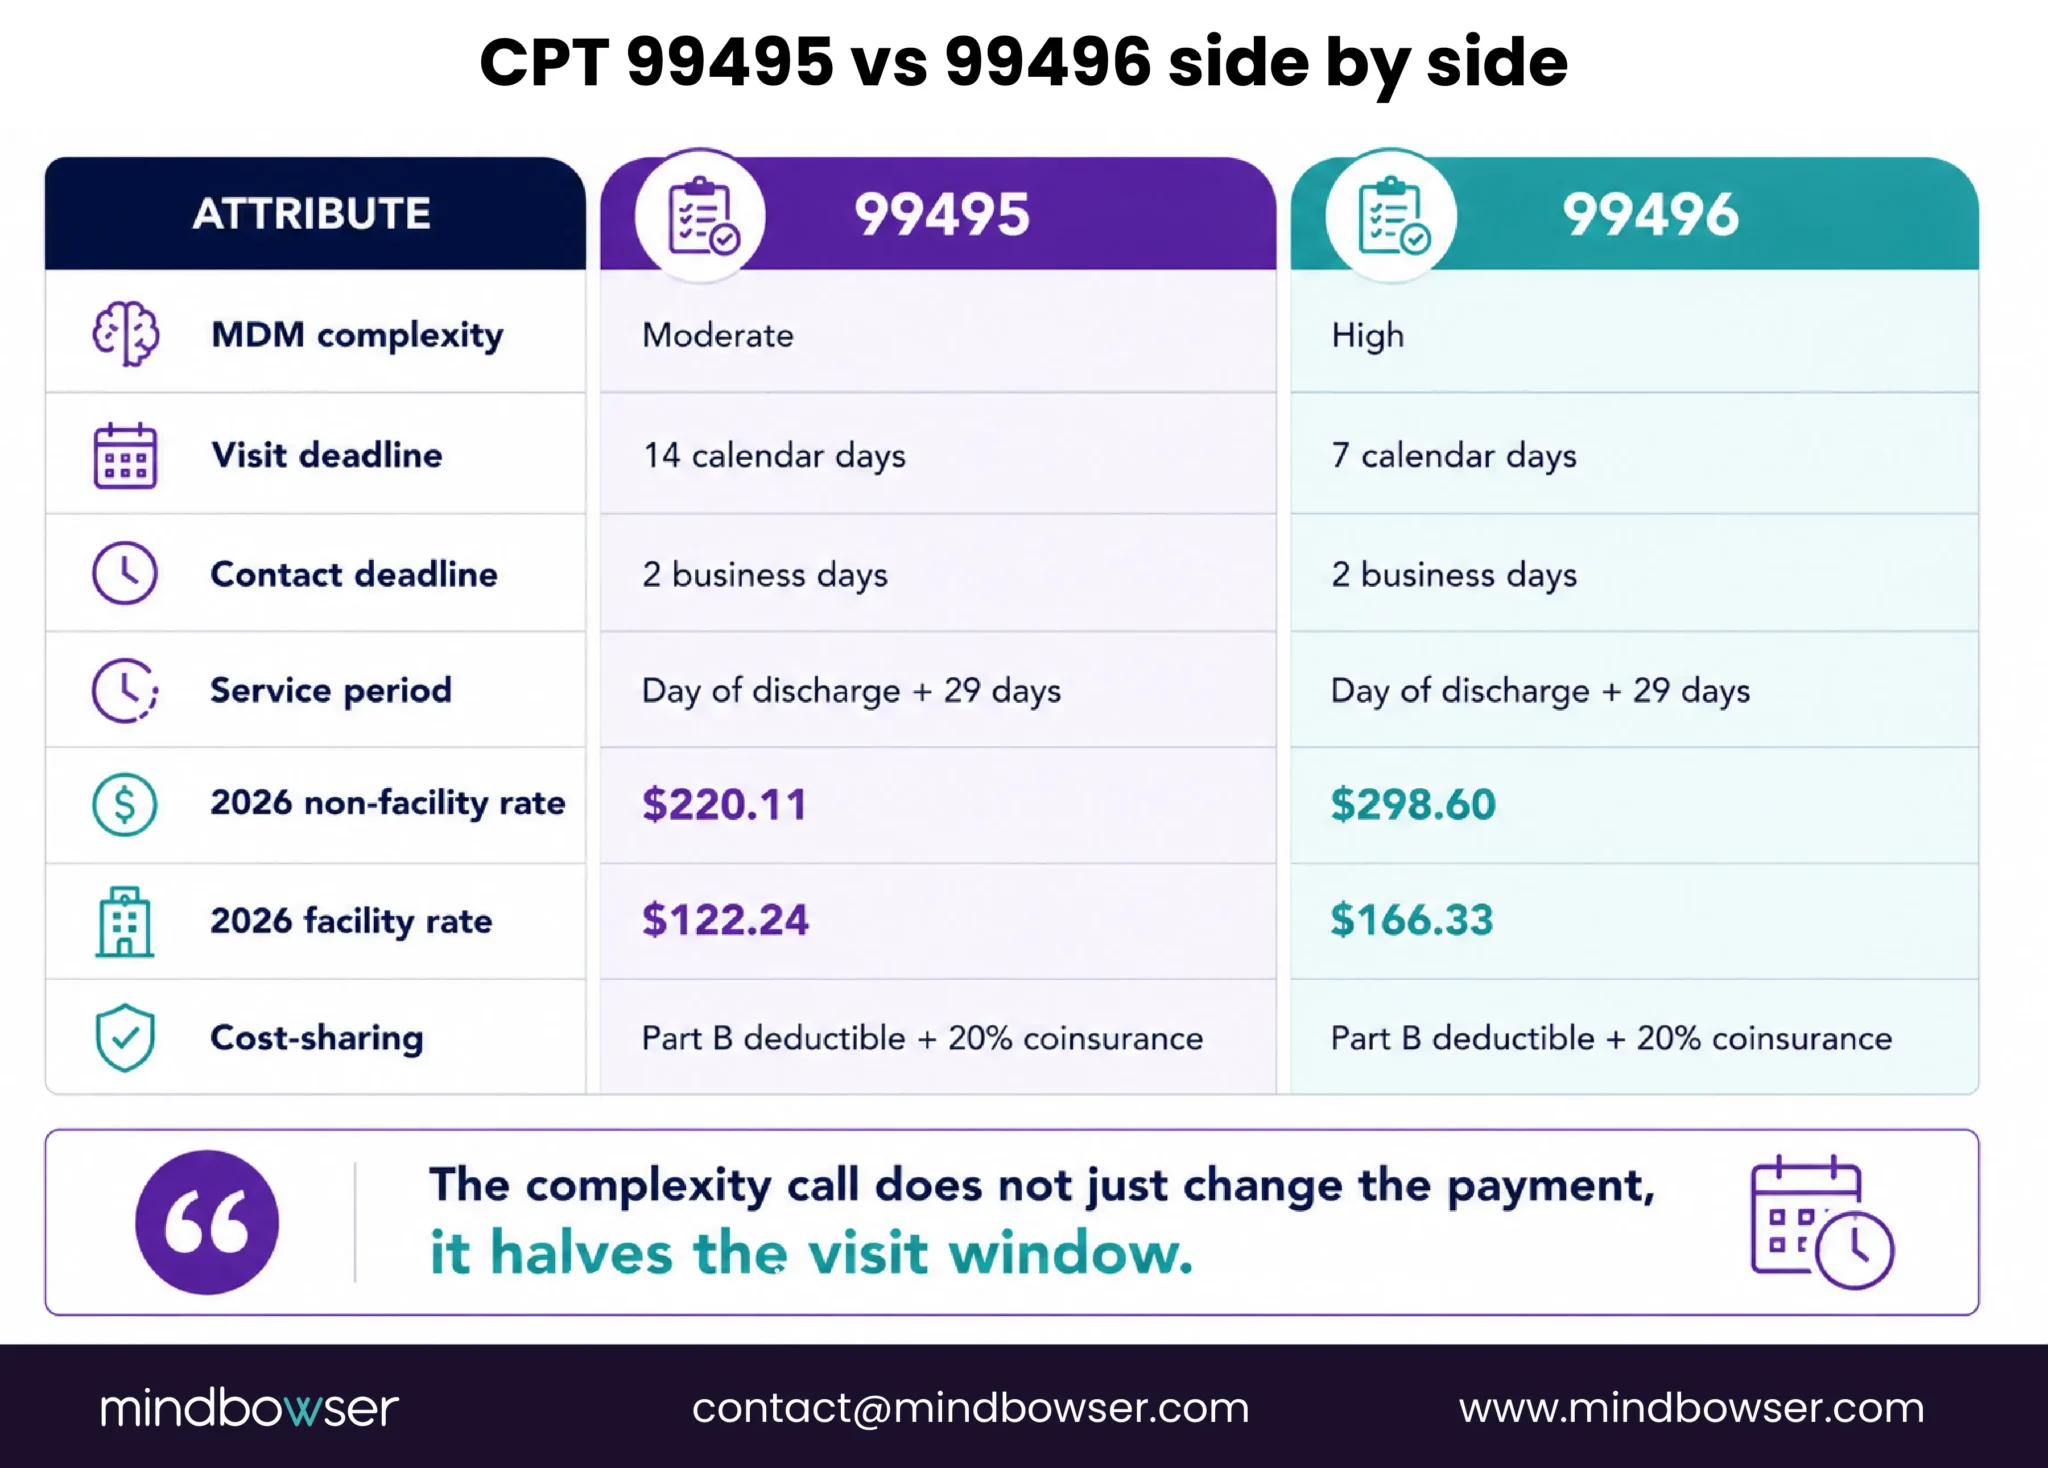
CPT 99495 covers at least moderate-complexity medical decision-making and requires a face-to-face visit within 14 calendar days of discharge. CPT 99496 covers high-complexity decision-making and requires that visit within 7 calendar days. Both require interactive contact with the patient or caregiver within 2 business days of discharge, and both cover a single 30-day service period that begins on the day of discharge and runs the next 29 days.
That call gets made at intake, often by whoever opens the episode, and it commits the practice to a schedule. Choosing 99496 when the documentation supports moderate complexity invites an adjustment. Choosing 99495 on a genuinely high-complexity patient means the visit can land on day 12, inside the 14-day window but outside the 7-day one, with no way to recover the difference.
The discharging setting matters as much as the code. CMS enumerates seven: an inpatient acute care hospital, an inpatient psychiatric hospital, an inpatient rehabilitation facility, a long-term care hospital, a skilled nursing facility, hospital outpatient observation or partial hospitalization, and partial hospitalization at a community mental health center. The patient must return to a community setting, which CMS lists as home, a domiciliary such as a group home or boarding house, a nursing facility, or an assisted living facility.
For 2026, the national average payment is $220.11 for 99495 and $298.60 for 99496 in a non-facility setting, calculated from the CMS relative value file at the non-qualifying-APM conversion factor of $33.40. In a facility setting the same codes pay $122.24 and $166.33. Geographic adjustment moves all four figures, so these are national averages rather than what any specific practice collects. Each is the full allowed amount, from which the patient’s 20% coinsurance comes out, so Medicare itself pays less than the published number. The next section treats that as its own line item.
Both non-facility rates are about 9.5% above 2025, and the conversion factor explains only 3.26% of it. Total non-facility RVUs did the rest, rising 5.9% for 99495 and 6.0% for 99496, which compounds with the conversion factor to the 9.4% and 9.5% actually observed. Work RVUs are unchanged, because CMS exempted care management services from the 2026 efficiency adjustment that cut work RVUs elsewhere by 2.5%. The movement is entirely practice expense: CMS finalized a reallocation recognizing greater indirect costs in office-based settings than facility ones, lifting non-facility practice expense RVUs 10.7% and 11.6%.
The same reallocation ran the other way in the hospital outpatient department. Facility rates fell: 99495 from $134.24 to $122.24, 99496 from $182.43 to $166.33, both down about 9%. Office-based TCM pays about 9.5% more in 2026 and hospital-based TCM about 9% less, from one methodology change. If your TCM visits happen in a provider-based clinic, revenue per episode went down while the published headline went up.
What TCM Actually Pays, Across Medicare and Commercial
Published rates describe what a clean claim earns. They are not what lands in the bank, and the difference is a line item most TCM revenue models leave out.
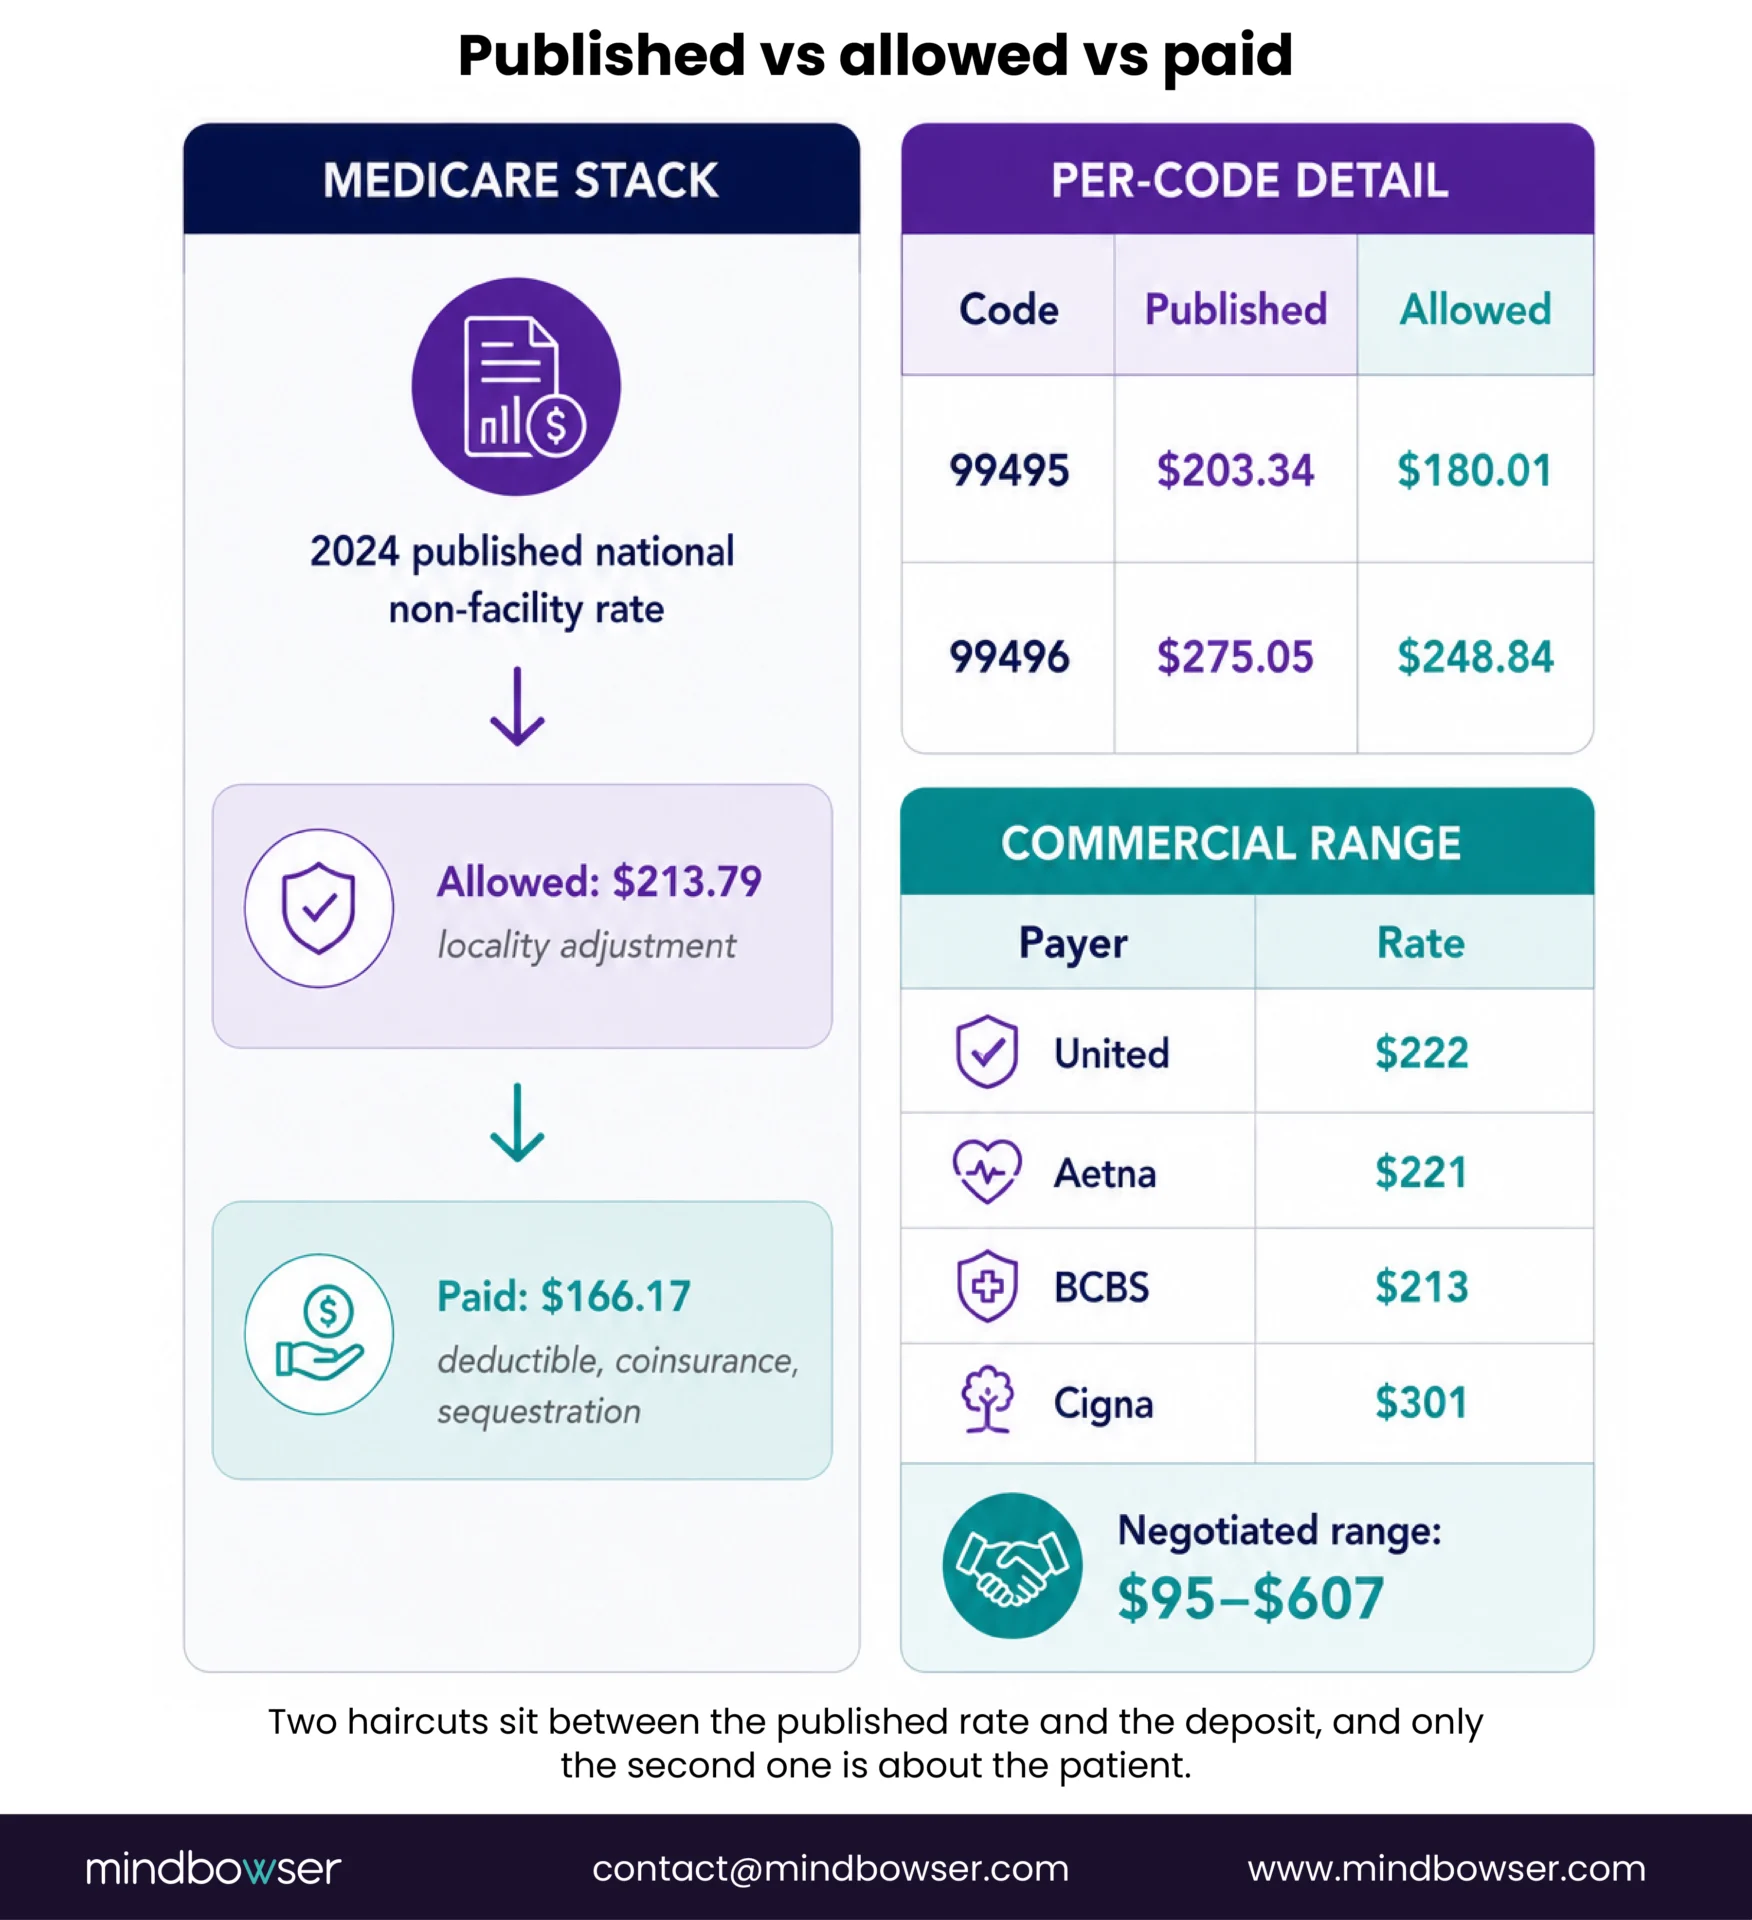
In the 2024 data year, the most recent published, Medicare allowed $303,823,005 for TCM across 1,421,106 services delivered to 1,242,197 beneficiaries, and paid $236,150,458 of it. Both figures come from the CMS Medicare Physician and Other Practitioners public dataset at the national level, summed across both codes and both places of service. Divide each by services: Medicare allowed $213.79 per TCM service and paid $166.17.
Two separate haircuts sit between the published rate and the deposit, and they stack.
The first is locality. Against the 2024 published national non-facility rates of $203.34 and $275.05, measured allowed amounts were $180.01 for 99495 and $248.84 for 99496, roughly 10% under on both codes. Two explanations can be ruled out with the same file. Not code mix: the gap appears within each code separately. Not facility drag either, since facility claims are about 4% of each code’s volume, and restricting to non-facility leaves 99495 at $182.49 against $203.34 and 99496 at $252.28 against $275.05. What remains is geographic adjustment. A published national average is unweighted; real allowed amounts are GPCI-adjusted and volume-weighted toward localities below it.
The second is cost-sharing, and it splits three ways. Medicare’s payment lands at $166.17, $47.62 under allowed: $42.76 patient coinsurance, $1.44 annual Part B deductible spread across services, and $3.42 sequestration, which is billable to nobody and simply gone. So $44.20 per service is collectible from the patient or a secondary and $3.42 is not. Across 1,421,106 services, $62.8 million to collect and $4.9 million that evaporates. Most beneficiaries carry Medigap or a secondary that picks up coinsurance on crossover, so the collectible part is rarely bad debt. It is still a billing step off the Medicare remittance.
Stack them and a practice modelling TCM at the published national rate, then reconciling against Medicare deposits, finds roughly a quarter of its expected revenue missing and concludes the program underperforms. One haircut is geography, one is patient billing, and a sliver is statutory. None of it is a coding error.
Commercial plans reimburse TCM too. payerprice.com, which aggregates payer transparency-in-coverage filings, put national averages for 99495 close to Medicare when accessed in August 2026, clustering between roughly $213 and $301 across the four largest carriers. The average is not the story. Negotiated rates across individual provider contracts in that data run from about $95 to about $607, more than 6x for the same code and the same work. If your payer mix is half commercial and nobody has checked where your TCM rates sit in that range, that is a larger number than anything in the denial list below.
100,735 provider records billed 99495 in 2024, and 83,929 billed 99496, counting each place of service separately, so a practice billing in both settings appears twice. Even discounted, that is one of the widest provider bases of any Medicare care-management program, which means the denial patterns below are repeating at scale.
What Has to Happen Inside the 30 Days
Before the failure modes, the sequence. The episode has four components, and their order matters as much as their presence.
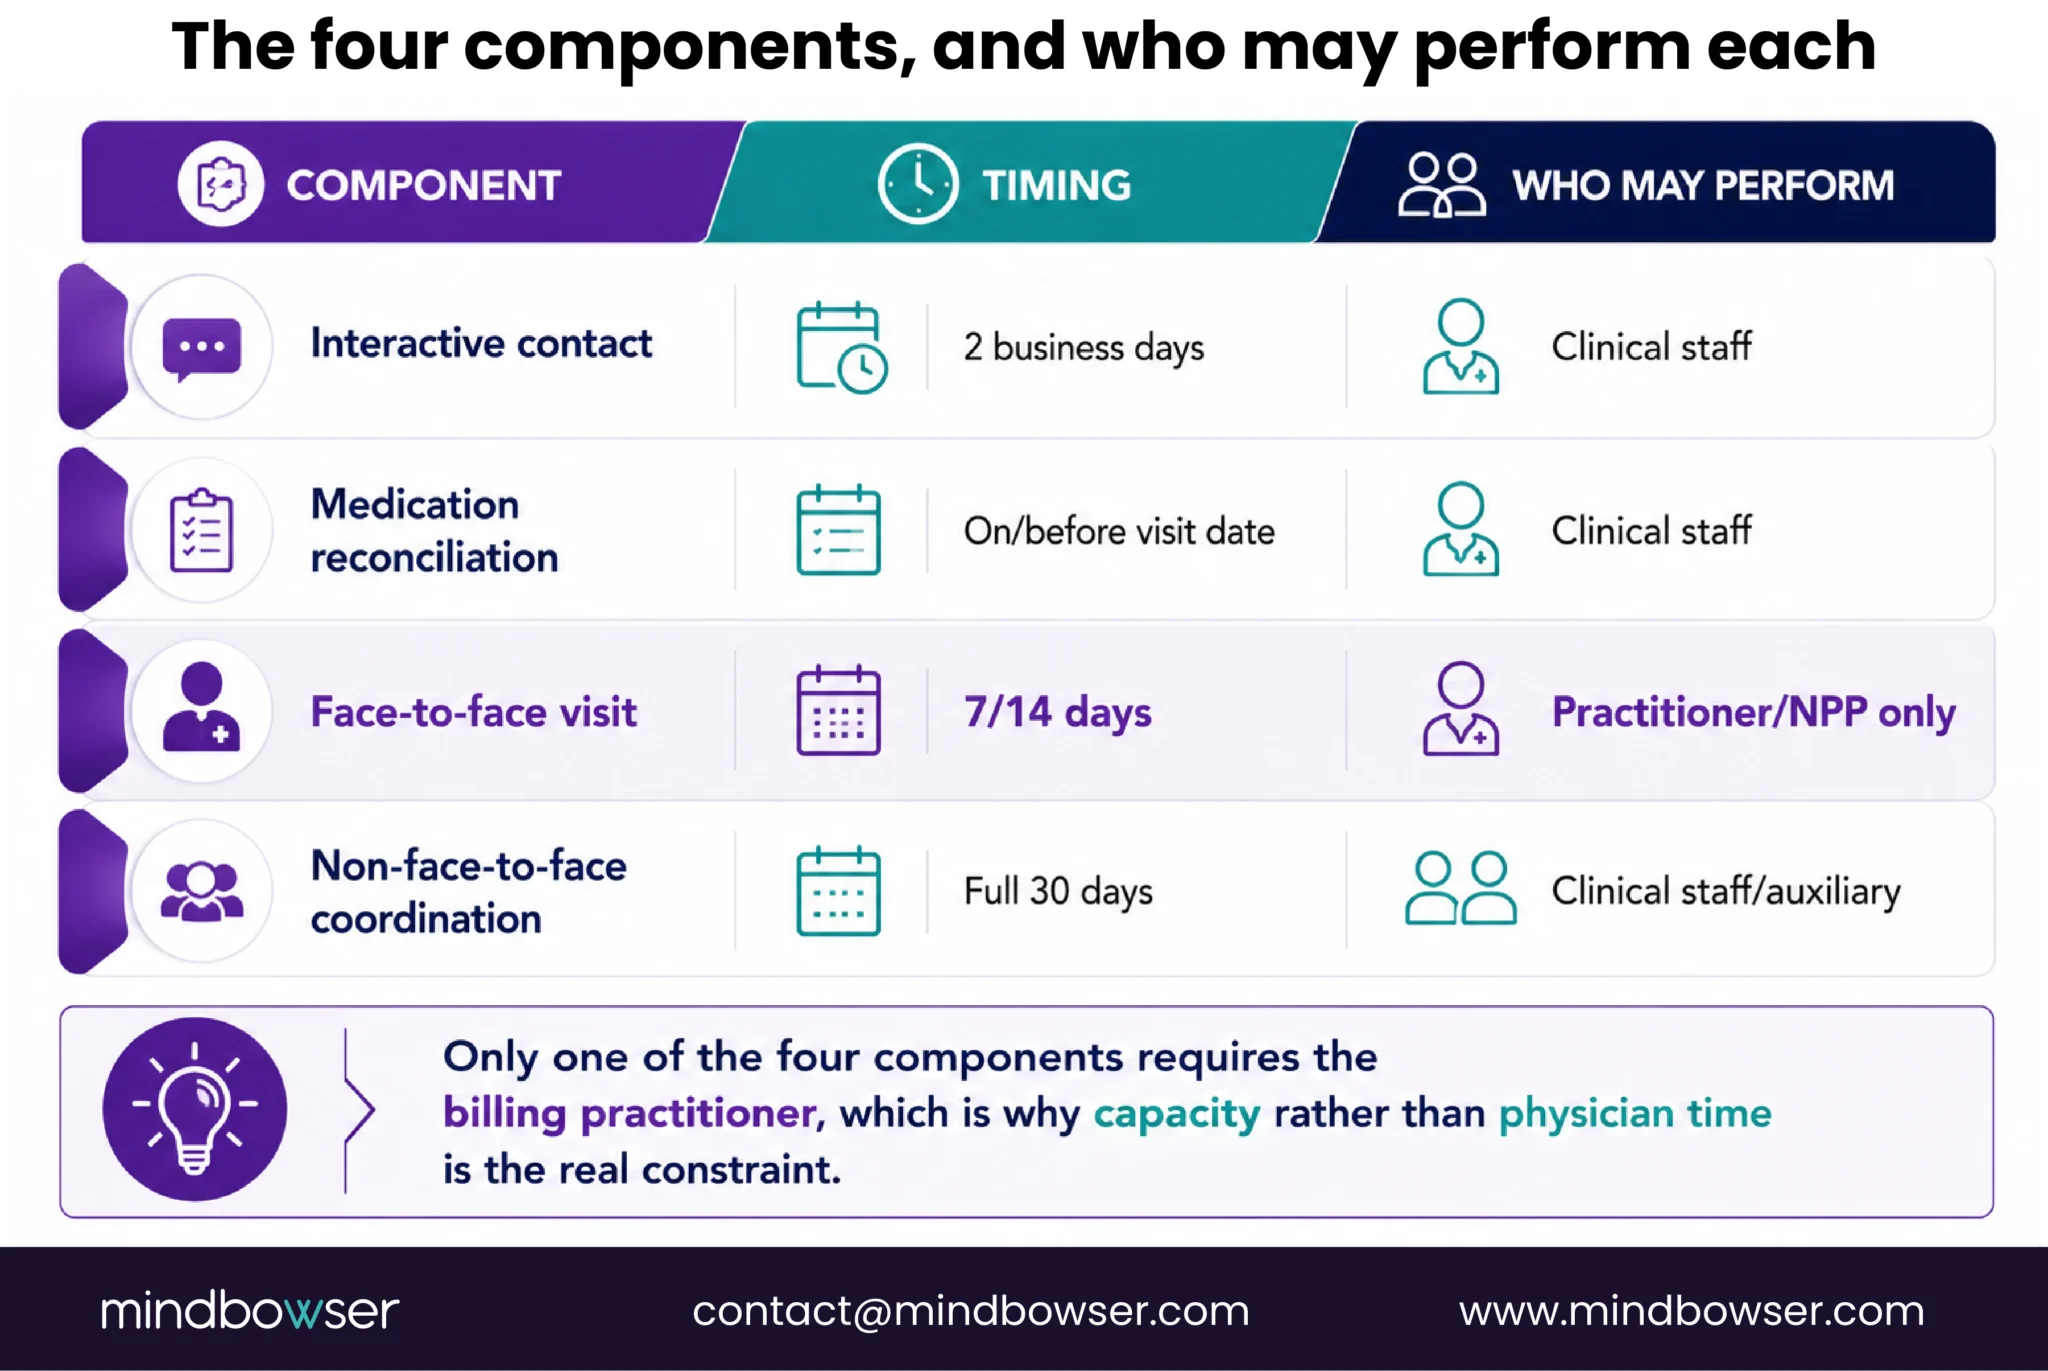
- Interactive contact comes first, inside 2 business days of discharge, by phone, email, or face-to-face, and clinical staff can make it under the billing practitioner’s direction. CMS is specific about who counts as clinical staff: someone able to address patient status and needs beyond scheduling follow-up care.
- Medication reconciliation and management must be furnished on or before the date of the face-to-face visit. That sequencing is the requirement itself. It is one of the few places where doing the work late counts the same as not doing it.
- The face-to-face visit follows inside its window, and it is the one component the billing practitioner or an NPP furnishes rather than delegates. The rest of the episode may be delivered by auxiliary personnel under general supervision, which MLN908628 states directly. (A 2016 CMS FAQ additionally described direct supervision as applying to the face-to-face visit; the August 2025 booklet does not repeat that, so treat it as dated guidance rather than current text.) It is not reported separately from the TCM code, and it cannot fall on the same day the practice reports discharge day management services.
- Non-face-to-face coordination runs the full 30 days: reviewing discharge information, following up on pending diagnostics, communicating with other professionals who may resume the patient’s care, establishing referrals, arranging community resources, and educating the patient or caregiver.
The delegation line is where practices get this wrong. Every component except the visit itself can be delivered by clinical staff under general supervision, so the constraint on running TCM at volume is care team workflow capacity, not physician time. Practices where nursing management already owns post-discharge outreach usually have the staffing right and the trigger wrong.
The 2-Business-Day Clock, Counted the Way CMS Counts It
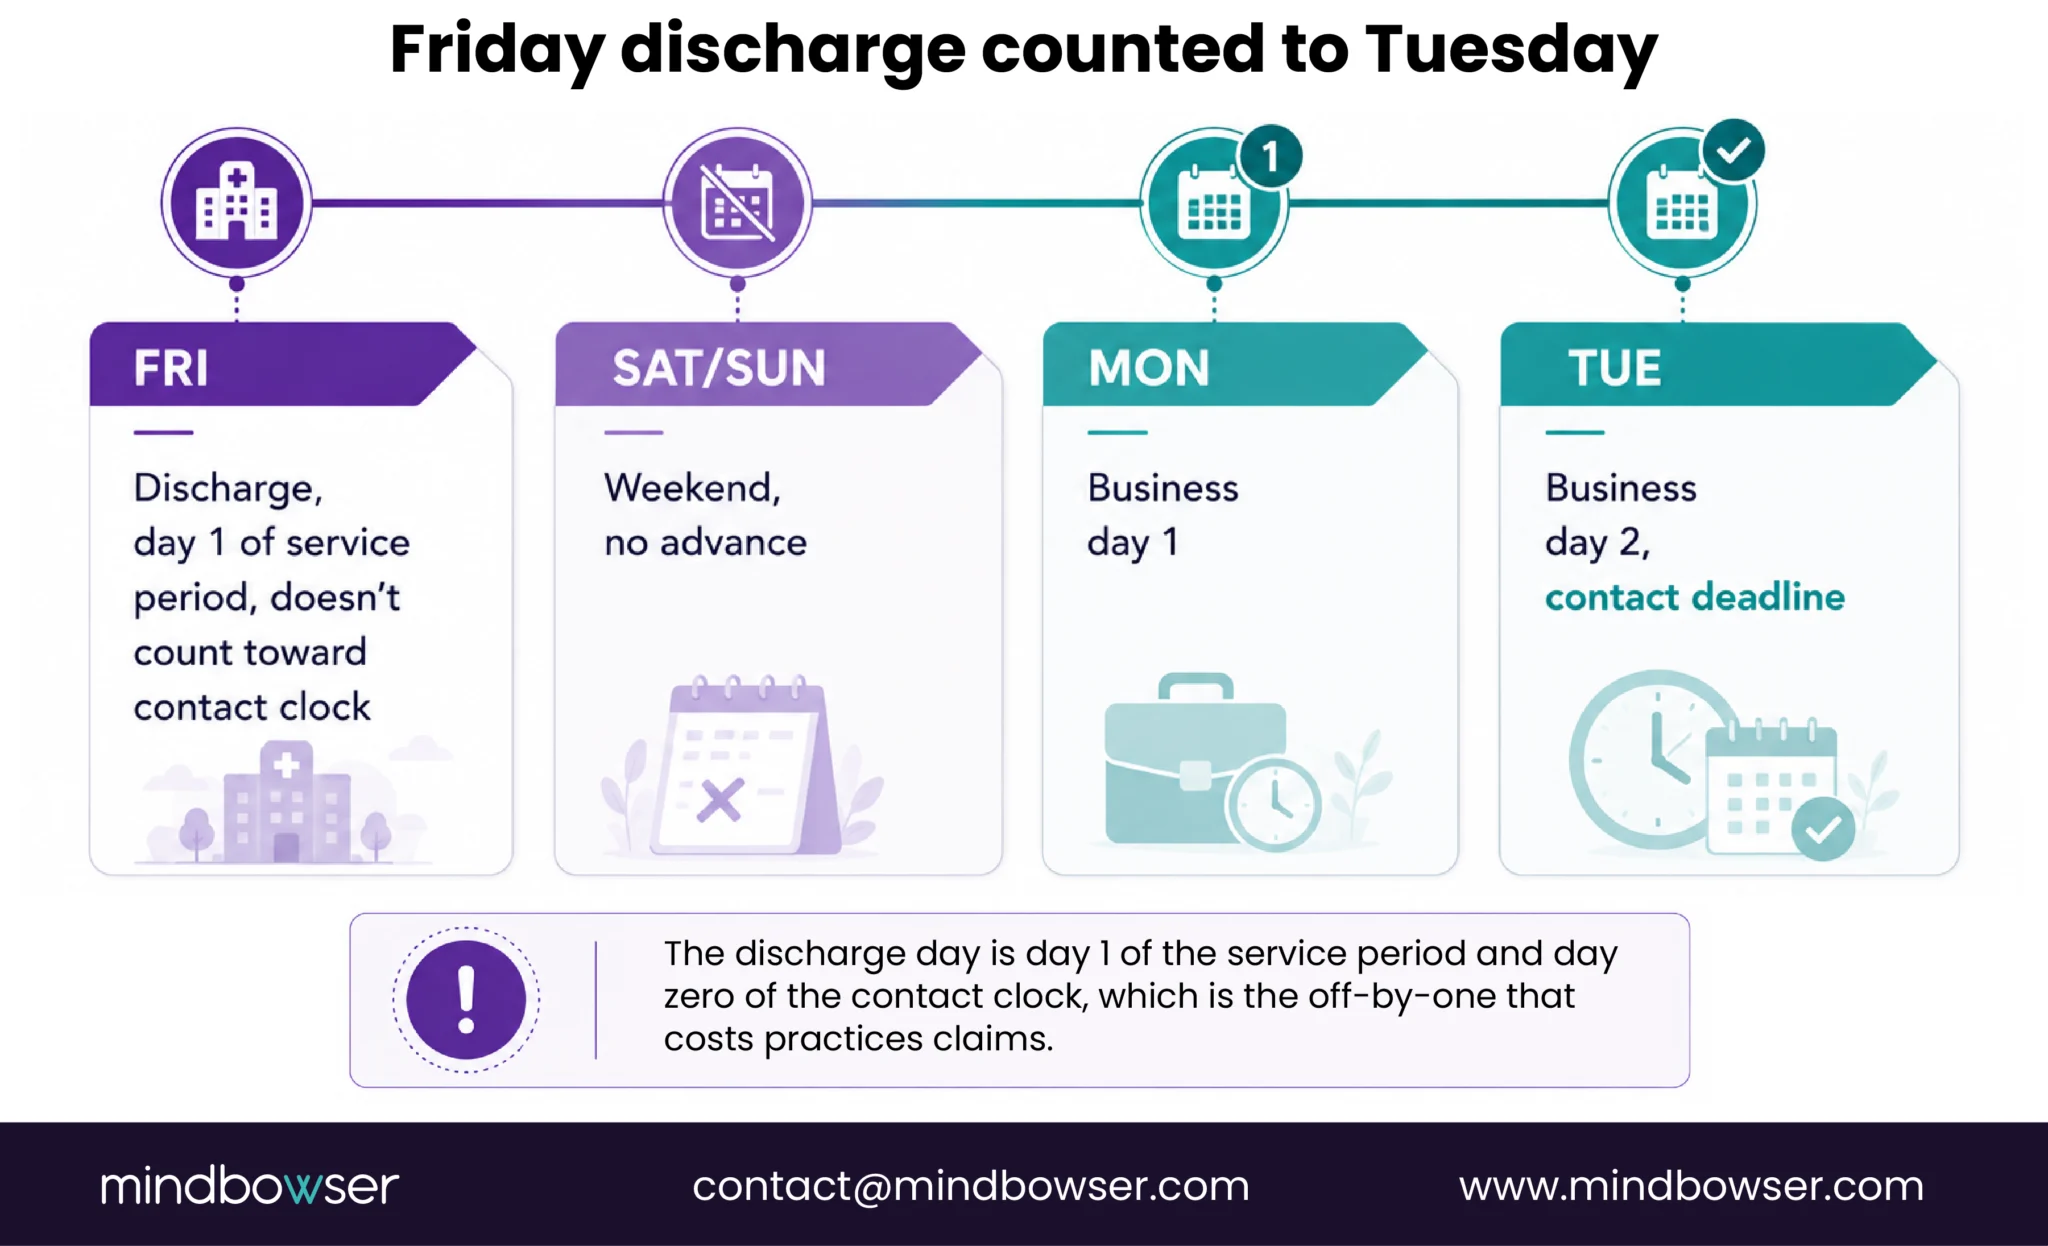
This is the rule practices get wrong most often, and it fails on arithmetic rather than on clinical judgment.
Business days run Monday through Friday, excluding holidays, and the day of discharge does not count. CMS worked the example itself: a patient discharged on a Monday at 4:30pm has until the end of the day Wednesday, the second business day following the day of discharge. Apply the same counting to a Friday discharge and the deadline is Tuesday, not Sunday, which surprises practices counting calendar days out of habit.
Two documented unsuccessful attempts do not sink the claim. They are what saves it. CMS states it twice, in the booklet and in the billing FAQ: if you make 2 or more separate contact attempts in a timely manner, document them in the medical record, and meet the other service requirements including a timely face-to-face visit, you may report the service. CMS still expects attempts to continue until they succeed. But a practice that called twice, logged both, and never reached the patient has a billable episode, not a write-off.
The safe harbor is conditional on one thing: the face-to-face visit inside its window. If the visit is not furnished within the required timeframe, you cannot bill TCM services. No attempt log, no documentation and no appeal recovers a missed visit window.
So the hierarchy is the opposite of how it is usually taught. The contact requirement is forgiving and has an explicit escape hatch. The visit requirement is absolute. Both start from the same event, and that event is the one thing in this program the practice does not control.
The two clocks in this program count the discharge day differently. For the 30-day service period, the day of discharge is day 1. For the 2-business-day contact requirement, the discharge day does not count and the clock starts on the next business day. Same episode, same date, opposite conventions. Apply one rule to both and you will either log the contact a day late or close the service period a day early. The visit window is a third case, and the worked example below shows why it is the one to count conservatively.
Where the Discharge Signal Comes From, and Why the Clock Is Already Running
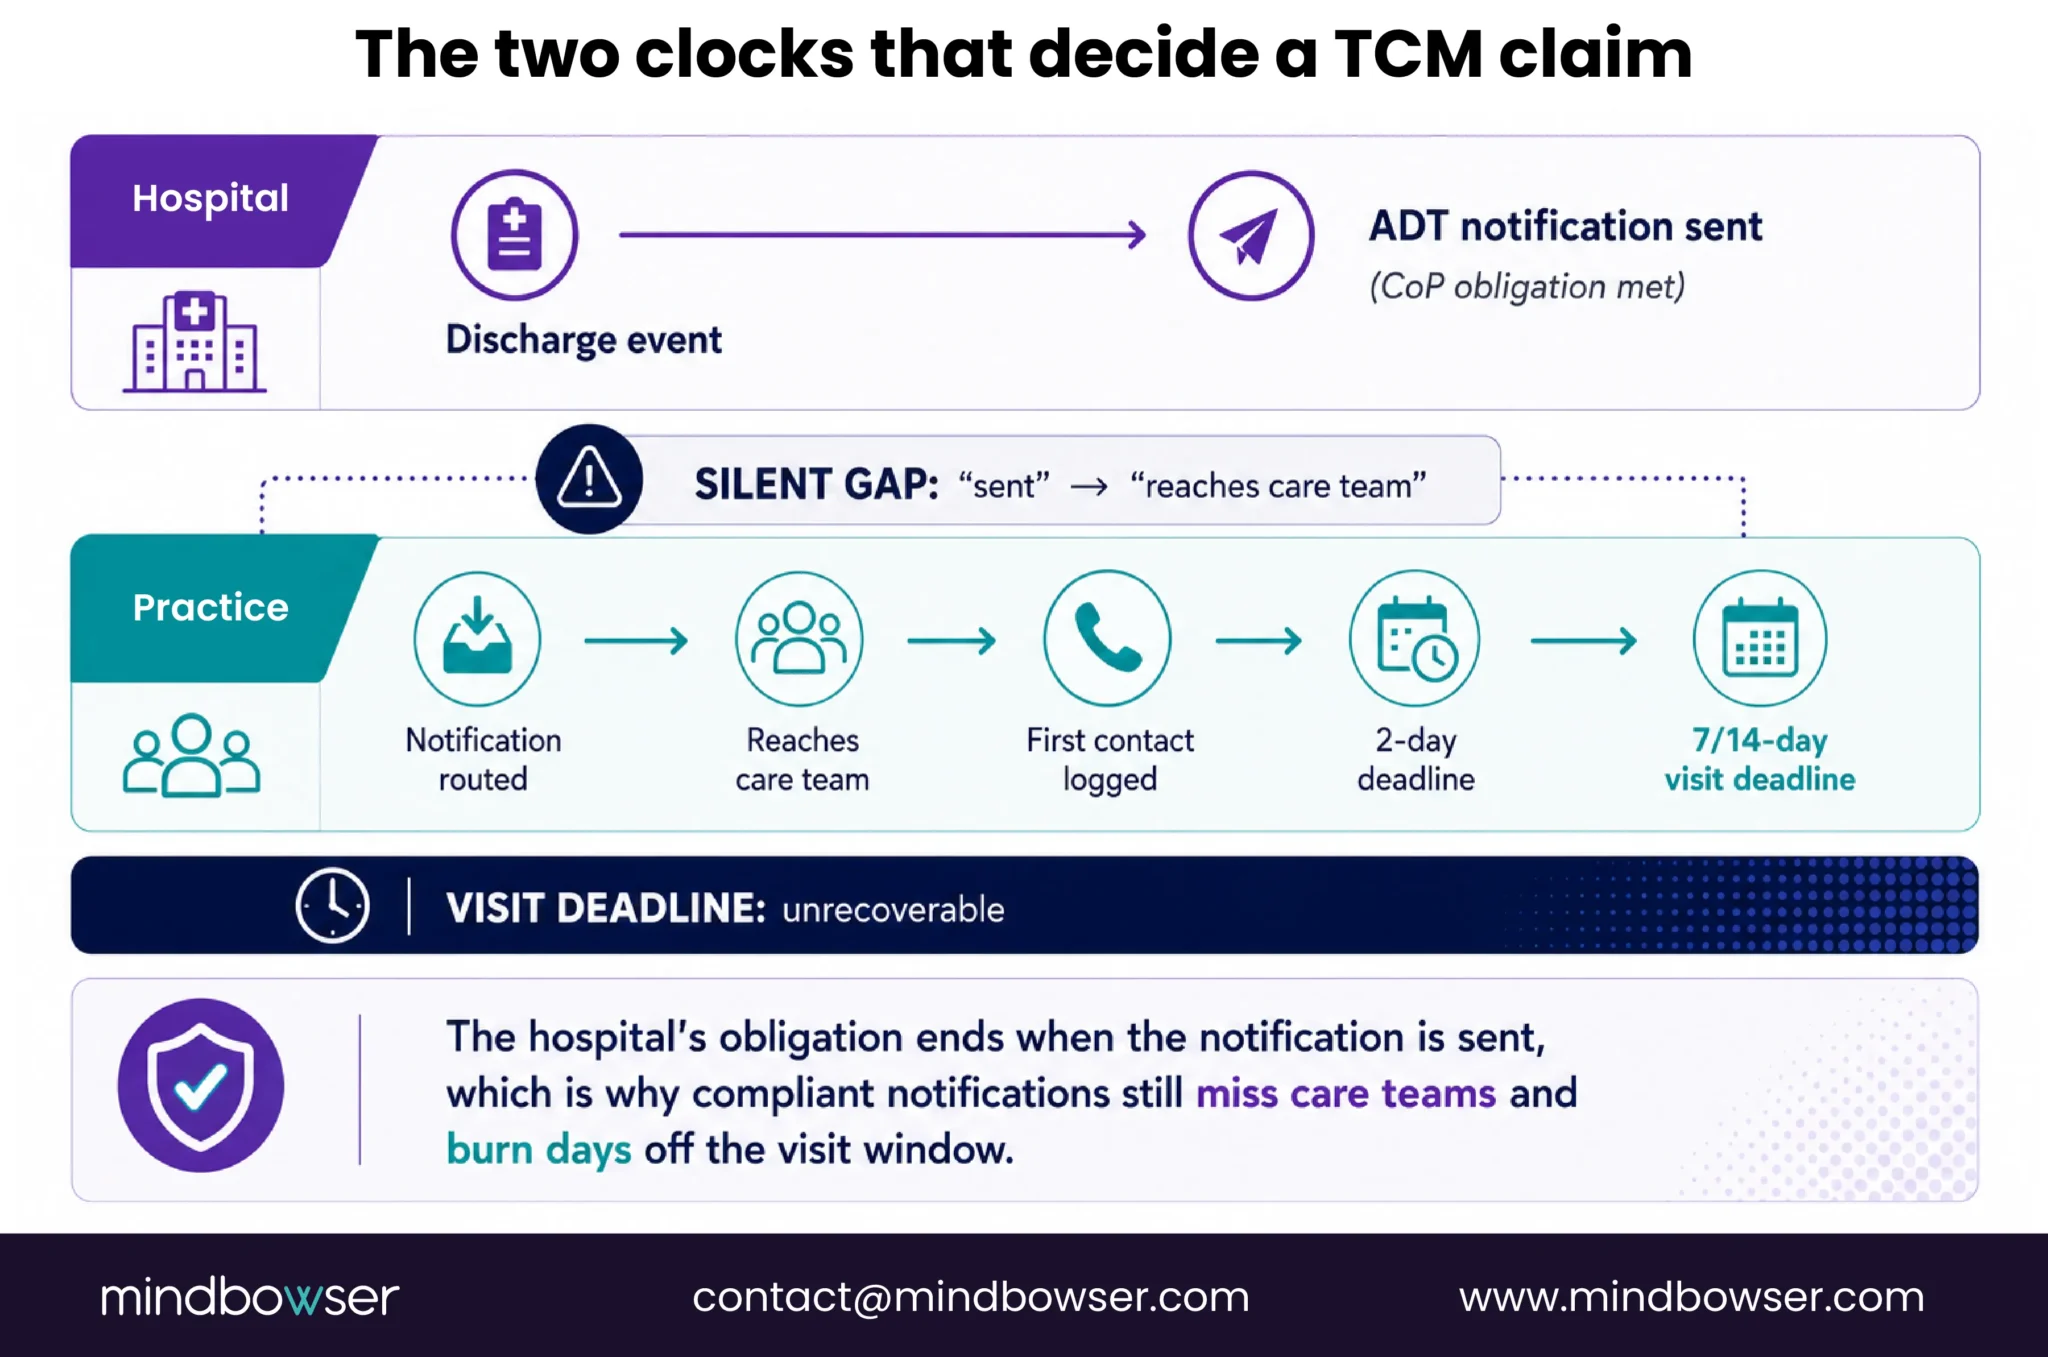
I have watched practices lose the same episode twice: once clinically, when nobody reached the patient, and once financially, three weeks later at the billing review. Both failures start in the same place, and almost no billing guide covers it. You cannot start a 2-business-day clock, or schedule a 7-day visit, from a discharge you have not been told about.
Most practices learn about a discharge one of three ways: the patient calls, a fax arrives, or someone notices at the next appointment. All three are slower than the deadline. The mechanism meant to solve it exists in regulation. Under the CMS Interoperability final rule published on 1 May 2020, hospitals, psychiatric hospitals, and critical access hospitals using conformant electronic systems must send electronic patient event notifications, the Admission, Discharge, and Transfer (ADT) messages, at the time of discharge or transfer. The requirement sits at 42 CFR 482.24(d), with parallel provisions at 482.61(f) and 485.638(d), and has been a Condition of Participation since 1 May 2021. CMS reads “immediately” as at the time of discharge, without intentional delay.
That obligation is narrower than it first appears, and the gap is where the claims go. As the American Medical Association has pointed out, hospitals are not required to deliver those notifications into a specific physician’s electronic health record inbox. A notification can be fully compliant with the Condition of Participation and still land somewhere your care team never looks. The hospital has met its obligation. Your clock has been running since Friday.
The previous section is why this matters more than it looks. A late notification does not just risk the contact requirement, which CMS is willing to forgive. It eats into the visit window, which CMS will not. A 99496 episode gives you a week to get a patient in front of the billing practitioner. Lose three days to routing and a single missed appointment closes it.
So a working TCM program is an integration problem before it is a billing problem. The feed has to arrive, be parsed, and reach a person or a queue that acts on it the same day, which is ordinary EHR integration platform work. Inside a large health system, Epic integration usually carries the ADT feed already and the question is routing.
One Episode, With Real Dates
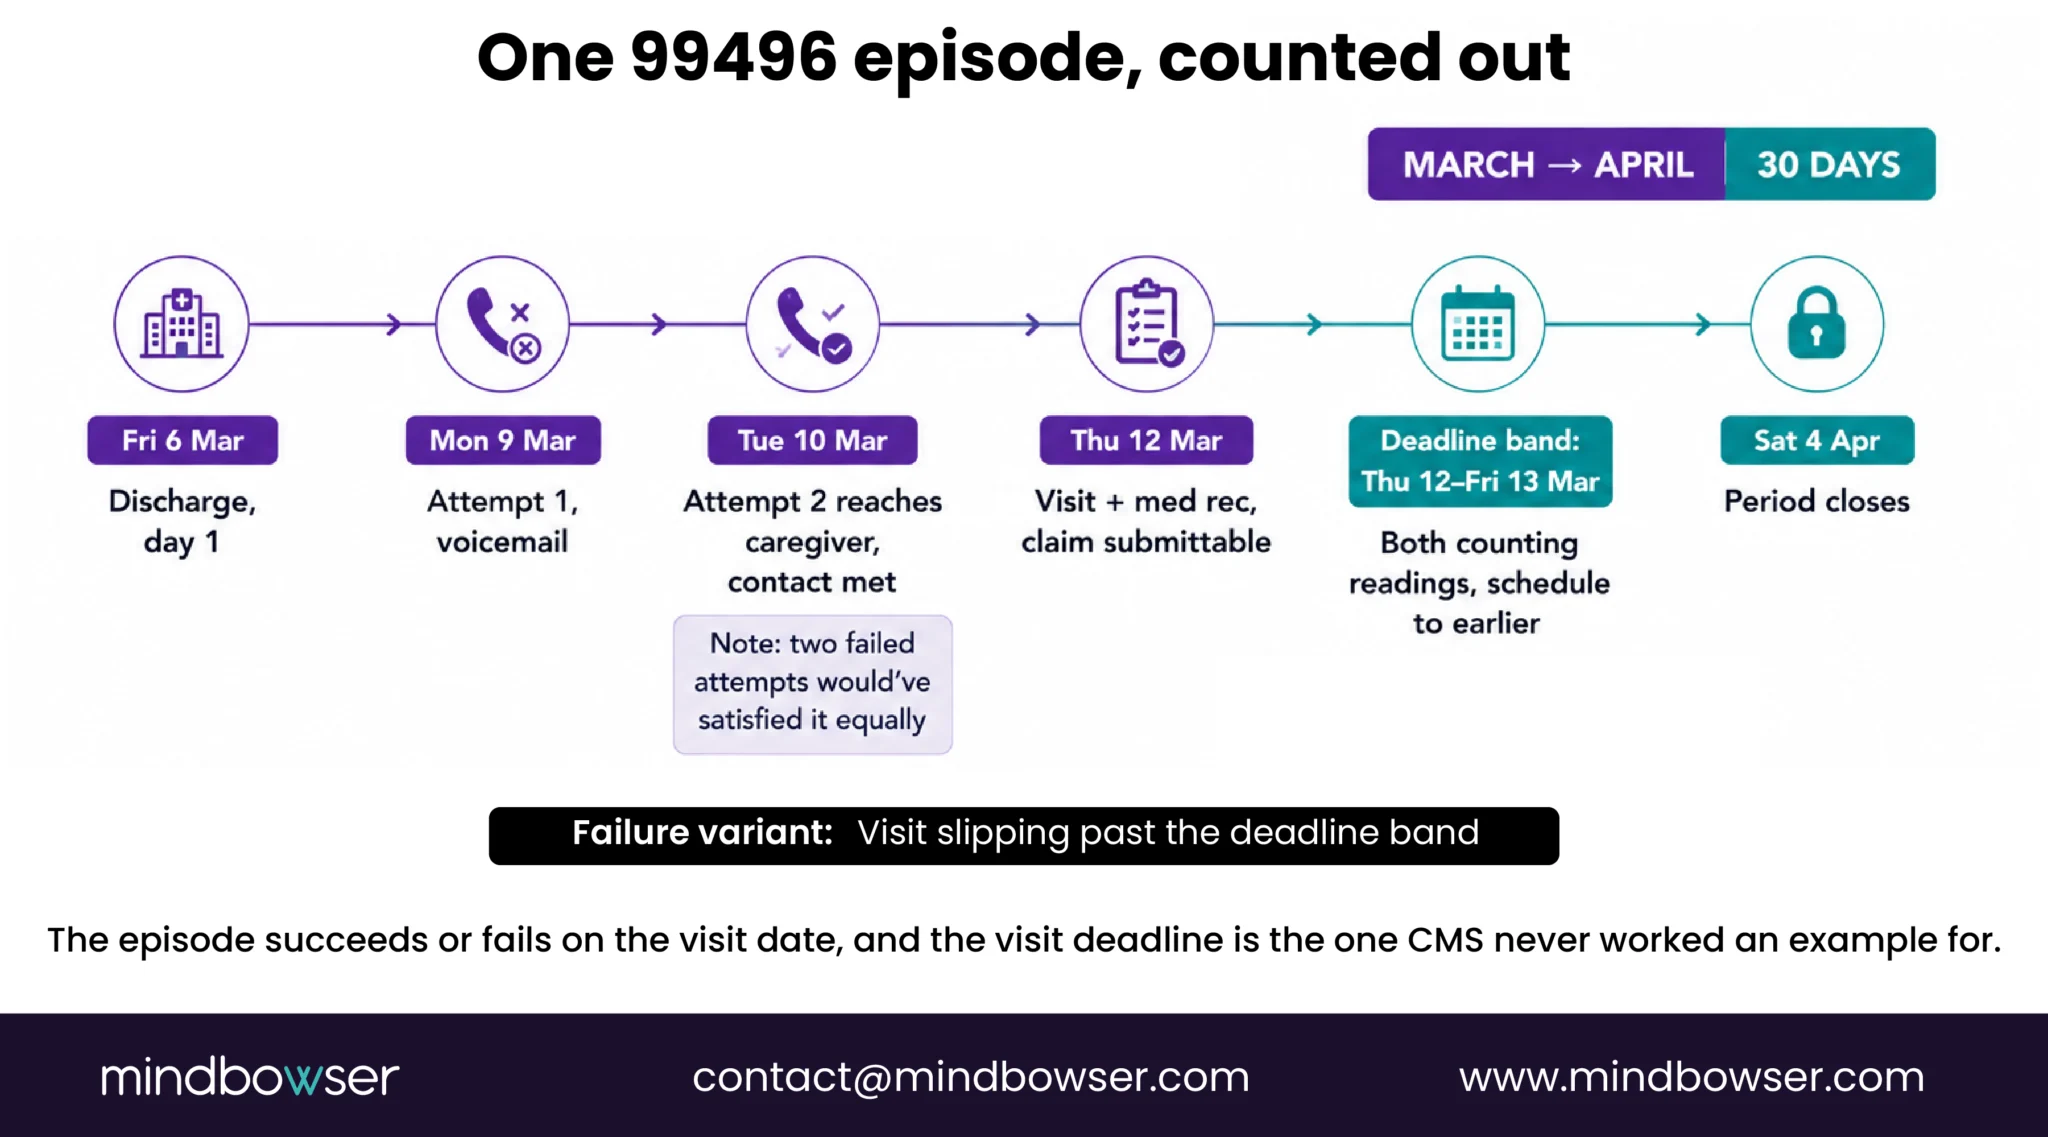
A patient is discharged from an acute care hospital on Friday 6 March, home to an assisted living facility. The discharge is high complexity, so this is a 99496 episode.
Friday 6 March is day 1 of the service period and day zero for the contact clock. The ADT notification fires at discharge; whether anyone sees it that day is the whole question. Monday 9 March is business day 1. A coordinator calls, gets voicemail, logs the attempt. Tuesday 10 March is business day 2 and the contact deadline. A second call reaches the patient’s daughter, which counts as interactive contact with a caregiver.
Note what just happened. Had that second call also gone to voicemail, the episode would still be billable: two timely documented attempts are enough for CMS provided the visit lands inside the window, though CMS still expects outreach to continue until it succeeds. Reaching the daughter was better care, and it was not what made the claim payable.
The visit is due within 7 calendar days of discharge, and here a third counting question appears that CMS never worked an example for. Count the discharge day as day 1, as the service period does, and the deadline is Thursday 12 March. Count from the day after, as the contact clock does, and it is Friday 13 March. CMS’s text says only “within 7 calendar days of discharge.” Schedule to the earlier date. The visit happens Thursday 12 March, which clears the deadline under either reading, and the claim can be submitted that same day with 12 March as the date of service. The service period still runs to Saturday 4 April, and coordination continues across it, but the money does not wait.
Now move the notification. If the practice does not learn about the discharge until Wednesday 11 March, the safe harbor goes with it, because there were no attempts inside the window to document. The attempts have to be timely; two calls placed after the deadline are not two timely attempts. And 11 March leaves one day to get a high-complexity patient in front of the billing practitioner before the visit window closes. Both failures came from a routing delay rather than anything clinical, and the visit one has no documentation-based recovery at all.
Request an Assessment
The Seven Ways a TCM Claim Dies

Each of these traces back to a nameable step in the workflow, which is what makes them preventable.
- The face-to-face visit lands outside its window. CMS states plainly that TCM cannot be billed if the visit is not furnished within the required timeframe. First on the list because it is the only one with no documentation-based cure.
- A component is missing or undocumented. CMS names four things that must be in the record: the discharge date, the date of first interactive contact, the visit date, and the level of medical decision-making. A gap in any is a gap in the claim.
- Date-of-service mismatch. The claim carries a date that does not match when the qualifying visit happened. Related and separate: the required visit cannot fall on the same day the practice reports discharge day management services.
- Medication reconciliation logged after the visit. CMS requires it on or before the visit date. Completing it two days later does not cure it.
- Complexity billed does not match the documentation. Reviewers compare the code against the visit note, and 99496 on a moderate-complexity note is a predictable adjustment.
- A second TCM inside the same 30 days. One practitioner, once per patient per TCM period. Where two could each plausibly claim the episode, Medicare pays the first eligible claim and denies the rest.
- TCM inside a post-operative global surgery period. CMS does not pay TCM if any part of the 30-day period falls within a global surgery period for a procedure billed by the same practitioner. This one is invisible from inside the care management workflow, because the conflict lives in the surgical schedule.
What to do with a denial you already have
Most of these are appealable when the underlying work happened and the documentation exists somewhere. A date-of-service mismatch is usually a corrected claim rather than an appeal. A complexity mismatch is worth a redetermination when the visit note supports the level billed and the reviewer read it narrowly. A denial for missed contact is worth challenging if two timely attempts were logged, because the safe harbor is on your side, though it lives in sub-regulatory guidance rather than the regulation, so expect to cite it. A missed visit window is the one to stop working, which is why the fix belongs upstream at the ADT feed.
Track denials by pattern rather than dollar value, since one routing failure can generate dozens of the same denial before anyone notices the shape. Ordinary denial management discipline, applied to a program whose failures are unusually uniform.
When the episode is genuinely lost, the medication reconciliation you performed is still reportable for quality purposes. CPT II code 1111F records it, on the date performed, and feeds the medication reconciliation post-discharge quality measure. It carries a Medicare status indicator of I and zero relative value units, so fee-for-service Medicare will not pay it and may reject it outright. Report it where a quality program or a plan asks for it, never as a way to recover the TCM fee.
Build a TCM Workflow That Catches Deadlines CMS Won't Waive
When You Can Actually Bill, and the Rule Most Guides Still Get Wrong
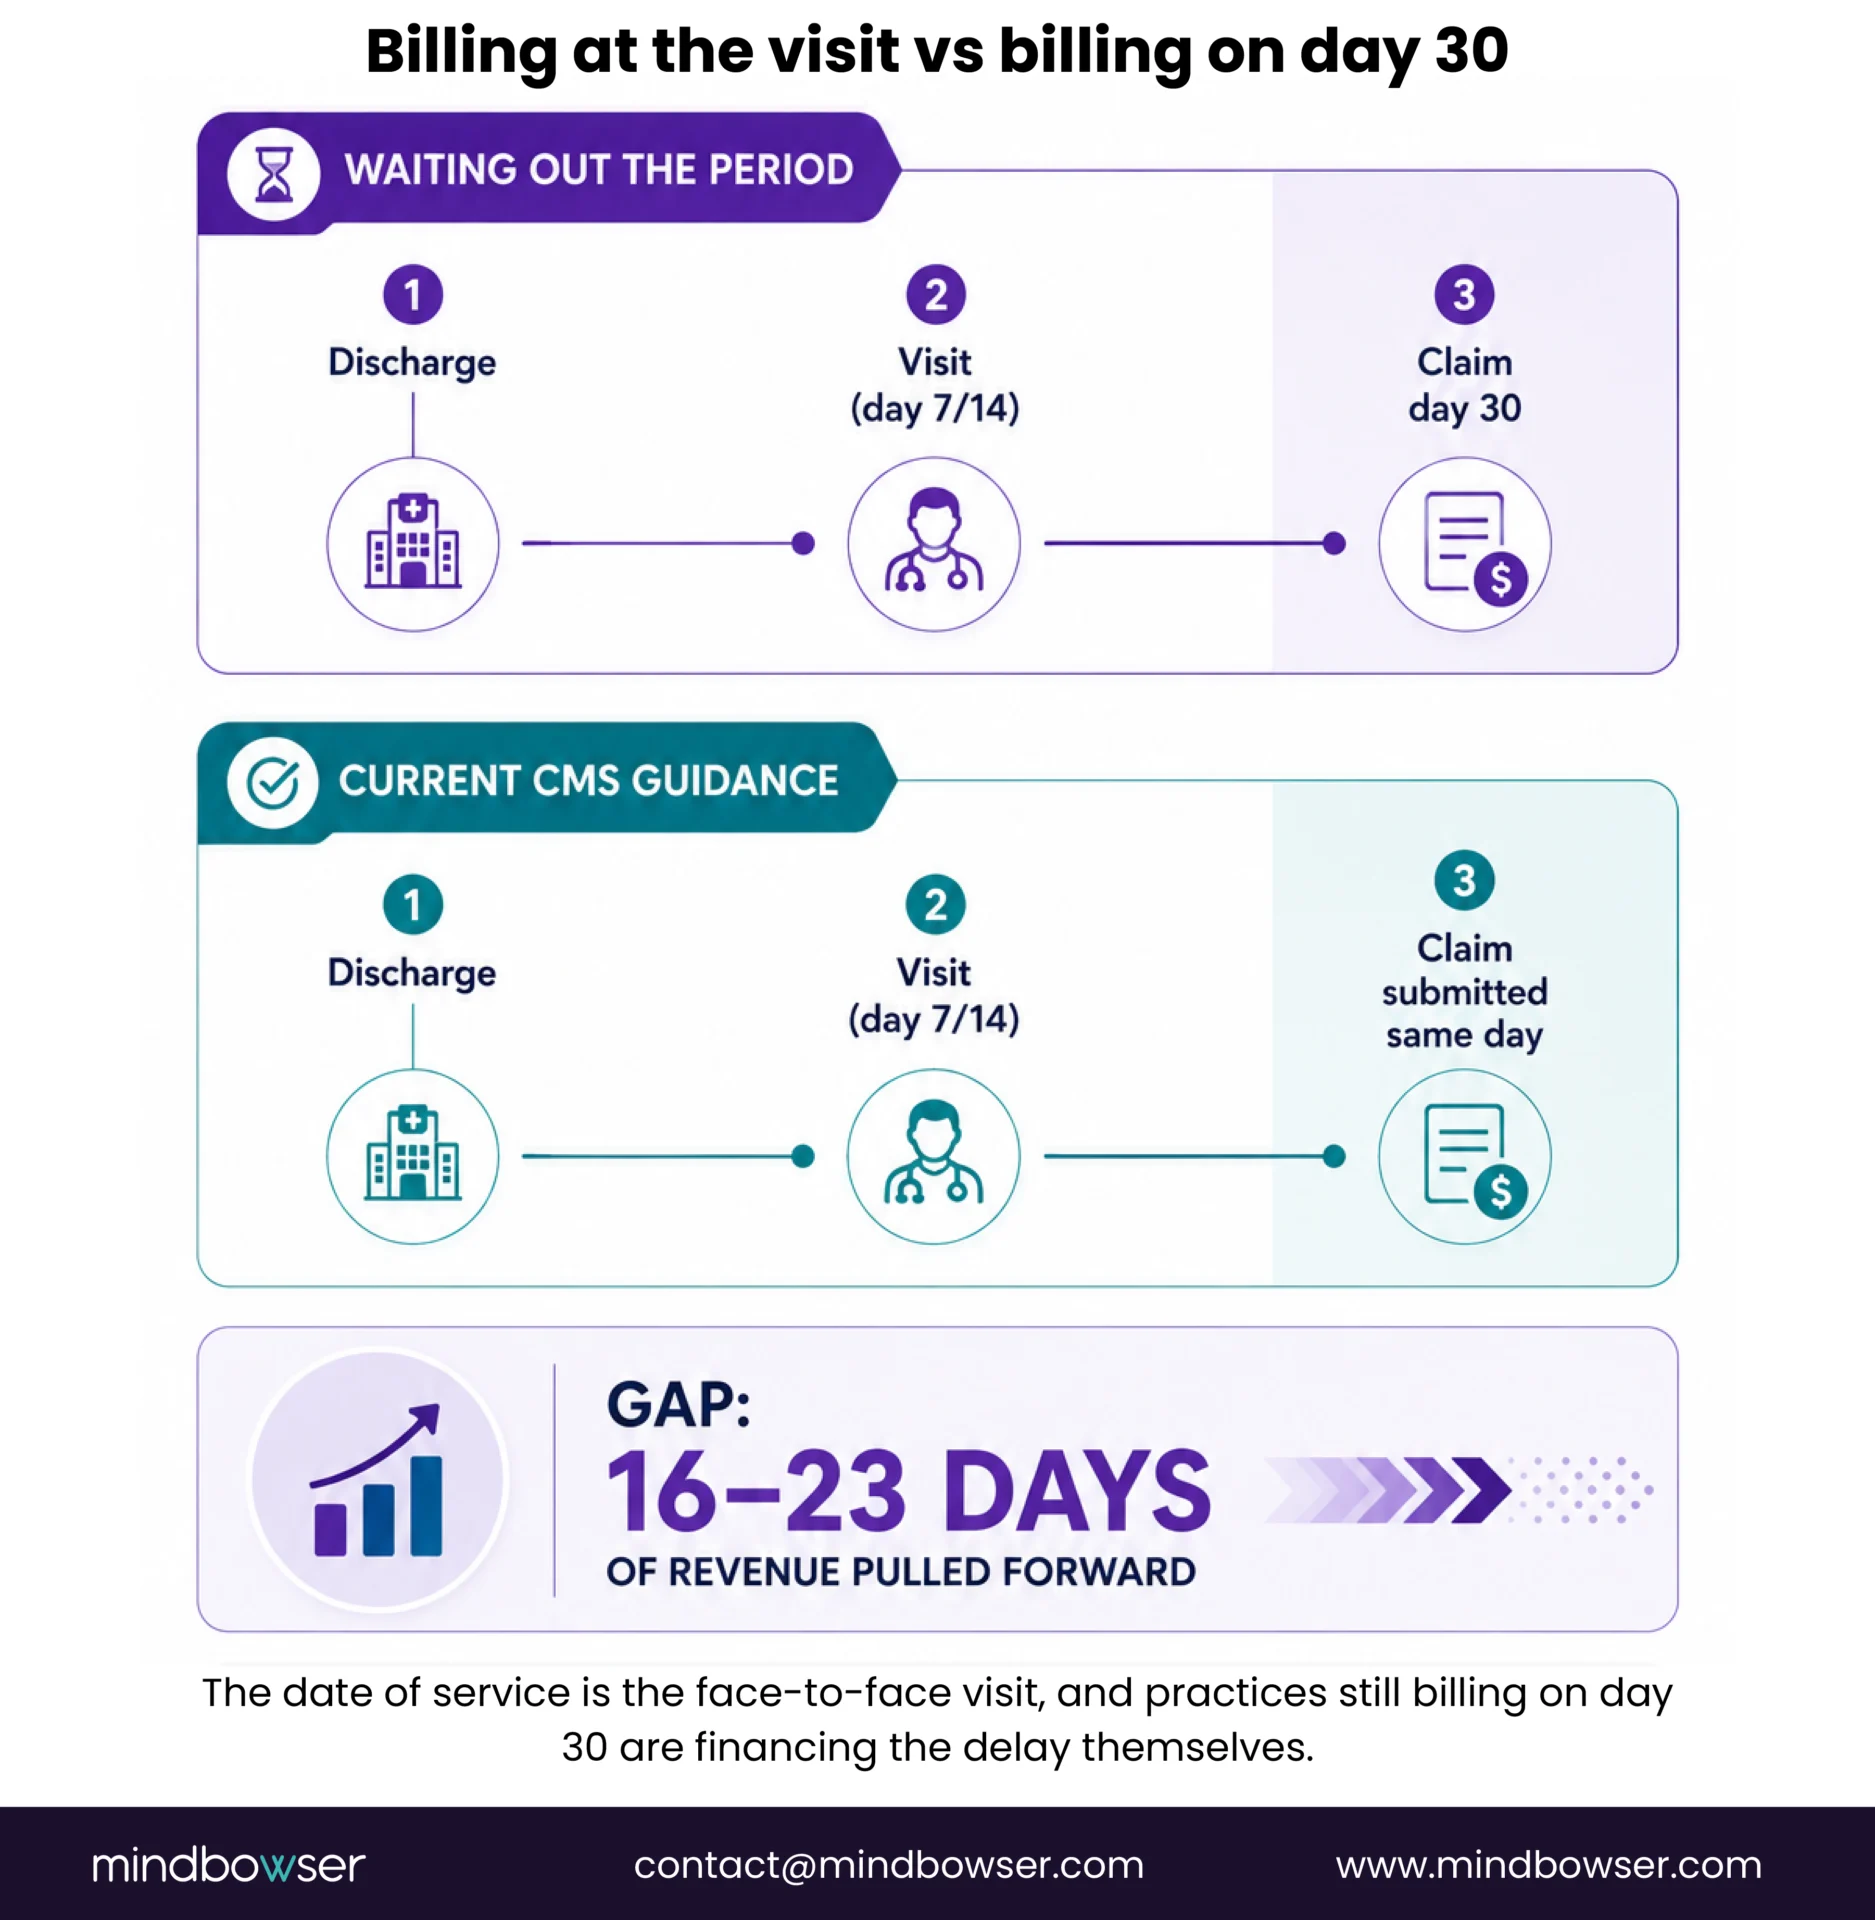
Ask most practices when they submit a TCM claim and they will say day 30. Correcting that is the fastest cash-flow improvement on this list.
CMS answers it directly in its own billing FAQ: the date of service you report should be the date of the required face-to-face visit, and you may submit the claim once that visit is furnished. You need not hold the claim until the end of the service period. The place of service on the claim is the place of service of that visit, which is also why the facility and non-facility rates in Figure 1 are decided by where the patient was seen rather than where the practice sits.
A 99496 visit is due by day 7 and a 99495 visit by day 14. Billing at the visit instead of waiting out the period pulls each episode’s revenue forward by roughly 16 to 23 days. For a practice running a few hundred TCM episodes a year, that is a permanent shift in working capital, obtained by changing when a claim is dropped.
It persists because it is still taught the old way by more than one source. The AAFP’s transitional care management billing page, one of the most-read provider references on this topic, currently instructs practices to submit the bill on the 30th day. The AAFP’s own FPM Getting Paid blog reported the change when CMS made it; the correction never reached the page most people land on. ThoroughCare’s TCM billing guide describes the same day-30 sequence. When the association and the vendors agree, a practice has no obvious reason to check the rule, which is how a decade-old change stays invisible.
Who May Bill, and Who May Not
TCM may be billed by physicians of any specialty and by non-physician practitioners legally authorized in their state: nurse practitioners (NP), physician assistants (PA), clinical nurse specialists (CNS), and certified nurse-midwives (CNM). It may not be billed by registered nurses, licensed practical nurses, or medical assistants. They can and do perform much of the coordination work, and CMS explicitly contemplates auxiliary personnel providing non-face-to-face services under general supervision. They cannot be the billing provider. TCM also applies to both new and established patients, which surprises practices assuming a transfer-of-care visit requires an existing relationship.
One rule governs frequency, stated by CMS in three layers people mistake for three rules. One practitioner, once per patient, per 30-day period. The unit is the period, never the discharge. If a patient is readmitted inside the window, the same individual or group cannot report a second TCM for that discharge. CMS offers a choice instead: continue the existing episode through the second discharge, or, if nobody billed the first, anchor a full 30-day period to the second. You pick one.
Where two practitioners could each plausibly claim an episode, Medicare pays the first eligible claim submitted in the 30-day period and denies the others. Ownership becomes a race, won by whoever is watching the discharge feed. Others can still report their own reasonable and necessary services during those 30 days, including E/M, so losing the TCM claim does not mean losing the work. It is the question continuity of care programs solve clinically, applied to a billing deadline.
CMS is also explicit that TCM is not intended for every discharge: clinical severity has to support the level of decision-making billed. Practices reporting TCM on every discharged patient tend to attract exactly the review they do not want.
Telehealth, Rural Clinics, and the Edge Cases
- Telehealth. CMS says 99495 and 99496 can be provided through telehealth, and pairs that with its own qualifier: Medicare pays for a limited number of Part B services furnished to an eligible patient using a telecommunications system. So the answer is yes, conditional on the encounter meeting Medicare’s telehealth conditions for the code and the patient, and those conditions have moved repeatedly. The practical constraint is rarely the policy; it is whether the visit is documented to the same standard as an in-person one, which is a question of how the telemedicine platform writes back to the record.
- FQHCs and RHCs. The rule here is different from the one that applies to a fee-for-service practice, and it changes what the clinic collects. Federally Qualified Health Centers and Rural Health Clinics are not paid separately under the Physician Fee Schedule, so none of the figures in Figure 1 are what an FQHC or RHC banks. What CMS says instead is that the face-to-face visit component of TCM can qualify as a billable visit, paid under the clinic’s own encounter rate: the all-inclusive rate for an RHC, the prospective payment system rate for an FQHC. Separately from the 2025 retirement of G0511, which never covered TCM, the CY2026 final rule opened a separate-payment path effective 1 January 2026: PFS care management services are treated as care coordination services that RHCs and FQHCs can bill on their own rather than folding into the encounter. For rural health clinics the harder problem is the discharge feed: rural patients are frequently discharged from a referral hospital in another system entirely, so the notification has further to travel and more places to stop.
- When the patient dies inside the window. If the beneficiary dies before the 30th day following discharge, CMS says not to report TCM, even where the visit happened and the coordination work was done. The visits that did occur may be reported under the appropriate E/M code instead. A bleak edge case that comes up more than practices expect.
- The service period is not a calendar month. The 30 days run from the discharge date, not from the first of the month. That matters when reconciling TCM against CCM, which is billed per calendar month, and it is the source of most confusion in the concurrency section below.
- Modifiers. TCM carries no routine modifier. Modifier 25 belongs to a separately identifiable E/M service on the same day as another procedure. And TCM is not on the primary care exception list, so the general teaching physician policy and the GC modifier apply as they would for other E/M services.
TCM, CCM, and APCM in the Same Month

This is the question that comes up most, and the answer that circulates is wrong.
CMS publishes a 42-code table, running seven pages of the current booklet, of care management services that can be billed concurrently with TCM when medically reasonable and necessary and when time and effort are not counted more than once. The CCM family is in it: 99490, 99491, 99487, 99489 and 99439. So are remote physiologic monitoring 99453, 99454, 99457 and 99458, remote therapeutic monitoring 98975 through 98981, 99091, prolonged services 99358 and 99359, home health and hospice supervision G0181 and G0182, anticoagulant management 93792 and 93793, and the ESRD series 90951 through 90970.
Two conditions do the work in that sentence, and they are the whole compliance question. The concurrent service has to be medically reasonable and necessary on its own terms, and the time behind it cannot be counted twice. A care manager cannot log the same 20 minutes of post-discharge outreach against both the TCM episode and the month’s CCM time. That is a time-attribution problem in your system of record, and if your chronic care management billing process cannot separate the two, take the conservative answer.
It is worth knowing why the stricter version is still everywhere. CMS’s 2016 billing FAQ, still circulated and still hosted, says CCM can be billed in the same calendar month as TCM only where the TCM period ends before the month does and at least 20 minutes of qualifying CCM time follows, and it excluded G0181 and G0182 outright. The current booklet lists both of those codes as concurrently billable. Where the two disagree, the August 2025 booklet is the current statement. Code-level detail across the CCM family sits in the CCM CPT code variants guide, and the higher-acuity tier in complex CCM, 99487 and 99489.
Advanced Primary Care Management (APCM), live since January 2025 under codes G0556 through G0558, changes the shape of the question. APCM bundles CCM, principal care management, TCM, and virtual check-ins into a complexity-tiered per-member-per-month payment with no time tracking, and the economics of moving from CCM codes to APCM are the deciding factor for most practices. APCM shows no 2024 billing in the CMS data, because 2024 predates its launch, so there is no utilization history to reason from yet.
A TCM episode is also a good moment to identify a patient for ongoing enrollment, and the same is true in reverse at the Medicare annual wellness visit, which is where most practices identify candidates for every other program in the first place.
What the Documentation Has to Prove When Someone Audits It
The denial list above is an audit preview, which makes this the cheapest section to read twice.
CMS names a documentation minimum, and it is short: the discharge date, the date of first interactive contact, the visit date, and the level of medical decision-making. Four dates and a judgment. That is the floor, and the floor is not what survives a review.
Four things have to be provable after the fact. That contact was attempted inside 2 business days, with timestamps on every attempt, because the safe harbor is worth nothing if the attempts are not in the record. That the complexity billed is supported by the visit note. That medication reconciliation was furnished on or before the visit date, timestamped to establish sequence rather than just occurrence. And that the practitioner who performed the visit is the one who billed it.
The failure pattern is consistent, and it is the same one behind care coordination technology that does not hold up: the documentation exists, scattered across a phone log, a scheduling system, and a note, with nothing tying it into one defensible episode record. In digital health teams building TCM into their own platforms, this shows up early now, as validation against CMS standards before submission rather than as an audit response afterwards.
Request an Assessment
What a Real TCM Build Looks Like, and How Much of It Is Already Built
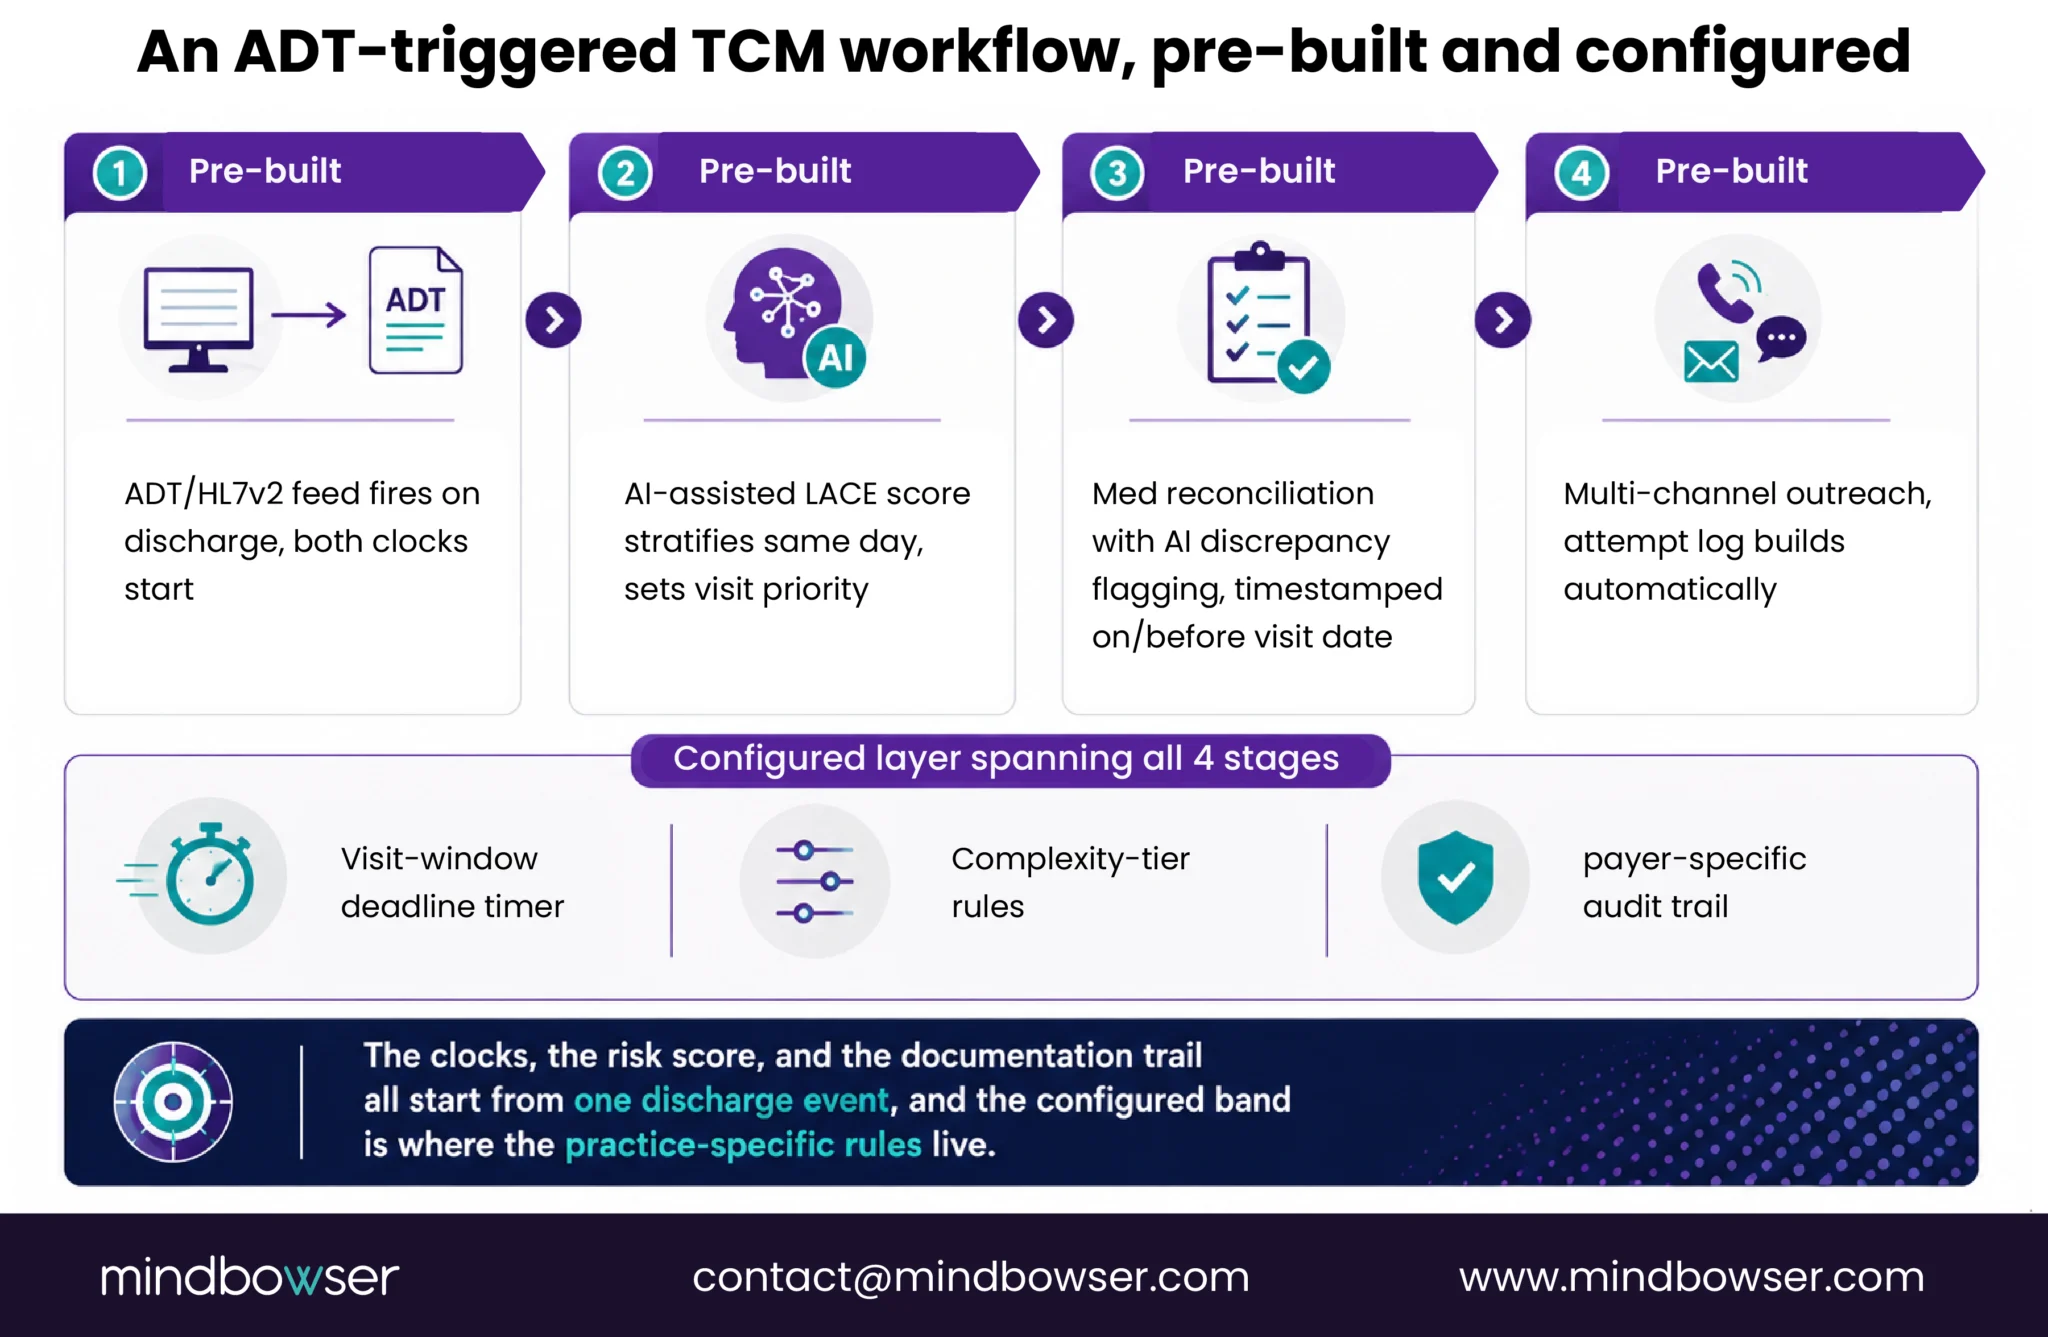
Everything above describes rules. This describes an actual build.
A digital health company replacing its own care platform worked with our clinical team to map a TCM program from discharge event to submitted claim. An ADT feed triggers patient intake the moment a discharge event fires, which starts the clock when it should start instead of whenever someone notices. An AI-assisted LACE score, a validated readmission-risk methodology scoring Length of stay, Acuity of admission, Comorbidities, and Emergency visits, stratifies the patient the same day and sets which patients get the 7-day visit priority. Medication reconciliation runs with AI flagging discrepancies against the discharge summary. Outreach goes across multiple channels instead of a single phone attempt, so the second documented attempt happens by default, which is what the safe harbor needs. The sequence was confirmed live on a sandbox environment, HL7 version 2 and secure file transfer ingestion included.
Most of that is not built from scratch. The discharge-alert intake, the reconciliation extraction with write-back to the EHR, and the readmission monitoring inside the 30-day window run as a pre-built ConnectHealth use case, roughly 80% of the workflow by scope, configured instead of coded. The post-discharge follow-up itself is handled in production by tools like DischargeFollow AI, whose deployment data shows a 38% reduction in 30-day readmissions and 40% less manual follow-up volume, recorded in our accelerator catalog.
The remaining 20% is where the claims are actually won. No pre-built deadline timer owns the visit window, so that gets built to your escalation rules. Your complexity-tier logic, the thing deciding 99495 against 99496 at intake, is specific to your patient mix. And the audit trail has to match what your payers ask for, which differs by contract. Those three are where a TCM build earns its money.
Rent a Platform, Configure the Pre-Built Workflow, or Build From Scratch
ChartSpan, CareHarmony, Clinii, SmartLink Health, and TapCloud all sell TCM platforms, and Epic markets native TCM capability inside its own EHR. So the choice is three ways, not two.
- Rent a point platform. Fast to stand up, generic in configuration, built for one program. The vendor owns the logic, fine until your payer mix or escalation rules differ from the default.
- Configure the pre-built workflow. The discharge-follow-up sequence described above already exists as a ConnectHealth use case. You configure the deadline timer, the complexity rules, and the audit trail instead of building the ADT ingestion, the reconciliation extraction, and the monitoring from nothing. For most practices already running TCM and losing claims to a late visit, this is the shortest honest path.
- Build from scratch. Correct when the workflow genuinely is yours alone. Cross-program stacking enforcement is the clearest example: deciding which combinations of CCM, principal care management, TCM, remote monitoring and behavioral health integration may run concurrently, and which minutes get attributed where, is rules-engine work no pre-built integration workflow covers.
The comparison worth having is which of the three matches the problem you have, and a practice losing claims to a routing delay has a different problem from one designing a multi-program billing engine.
Prevent the Denial Instead of Documenting the Visit
Every deadline in a TCM episode starts at a hospital, on a system you do not control, and the notification meant to tell you about it can be perfectly compliant and still never reach your care team.
CMS has built forgiveness into the part of this program practices worry about most: two documented calls satisfy the contact requirement even when nobody picks up. What CMS has not built forgiveness into is the visit, and a visit cannot be scheduled from a discharge nobody knows about. A practice running TCM on a spreadsheet learns about the gap during a billing review, weeks after the window closed. A practice running it from the discharge event learns the same day, while there is still something to do about it. Add the $44.20 per service Medicare allows but does not pay and somebody still has to collect, and the margin between those two operating models is most of the program’s economics.
If you are losing TCM claims and cannot say which of the seven patterns is doing the damage, that is the diagnosis worth running first.
Business days run Monday through Friday, excluding holidays, and the day of discharge does not count toward this requirement. CMS’s own example: a patient discharged Monday afternoon must be contacted by the end of the day Wednesday. A patient discharged on a Friday has until the end of the day Tuesday.
On the date of the face-to-face visit. CMS states that the date of service reported should be the visit date and that you need not hold the claim until the end of the service period, though the service period itself still runs the full 30 days.
If 2 or more separate attempts were made inside the window, documented in the medical record, and every other requirement was met including a timely face-to-face visit, the service can still be reported. The attempts have to be timely: calls placed after the deadline do not qualify, and neither does a window that passed with no attempt in it. CMS expects attempts to continue until they succeed. The requirement with no equivalent escape hatch is the visit window.
It has to be performed by the billing practitioner, which can be a physician or a qualified non-physician practitioner. Registered nurses, licensed practical nurses and medical assistants can perform the coordination work but cannot bill the service.
CMS says 99495 and 99496 can be provided through telehealth, and adds that Medicare pays for a limited number of Part B services furnished using a telecommunications system. It depends on the encounter meeting Medicare’s current telehealth conditions for the code and the patient, which have changed repeatedly since 2020.
99495 covers at least moderate-complexity medical decision-making with a 14-day face-to-face window. 99496 covers high-complexity decision-making with a 7-day window. The 2-business-day contact requirement is identical for both.
Yes. CMS lists the CCM codes 99490, 99491, 99487, 99489 and 99439 among the care management services billable concurrently with TCM, provided the service is medically reasonable and necessary and the same time and effort are not counted more than once.
Yes. CMS directs practices to report reasonable and necessary E/M services separately to manage the patient’s clinical issues, with the single exception of the required TCM face-to-face visit itself, which is not reported separately.
A visit outside its 7 or 14 day window, a missing or undocumented component of the four CMS requires, a date-of-service mismatch, medication reconciliation furnished after the visit, a complexity level unsupported by the documentation, a second TCM claim inside the same 30-day period, and a 30-day period overlapping a post-operative global surgery period.





