














 BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR























TL;DR
In most specialties the procedure is the money and the drug is incidental. In oncology that inverts, and the highest-value line on the claim is governed by the most mechanical rule in specialty billing: every single-dose vial line needs either a JW or a JZ modifier, and claims carrying neither are denied automatically. Practices still fail it, because the control is a person remembering to append two characters.
In most specialties the procedure is the money and the drug is a line item. Oncology inverts that, and every system built on the usual assumption inherits the inversion as a defect.
I have spent enough time looking at practice economics, and reading what groups like the Association of Cancer Care Centers publish about them, to be suspicious of anyone who describes oncology billing as simply “complex.” Complex is not actionable. What is actionable is that oncology’s largest revenue exposure sits on a part of the claim that most revenue cycle tooling treats as secondary, and that the single most common failure on that part of the claim is governed by a rule with no judgment in it whatsoever.
That last point is the one worth sitting with, and it is where I want to start. If you want the general shape of the cycle first, our revenue cycle management services page covers it and the 13 steps of the revenue cycle is the plainer version.
JW Modifier Versus JZ Modifier: Which One, and When
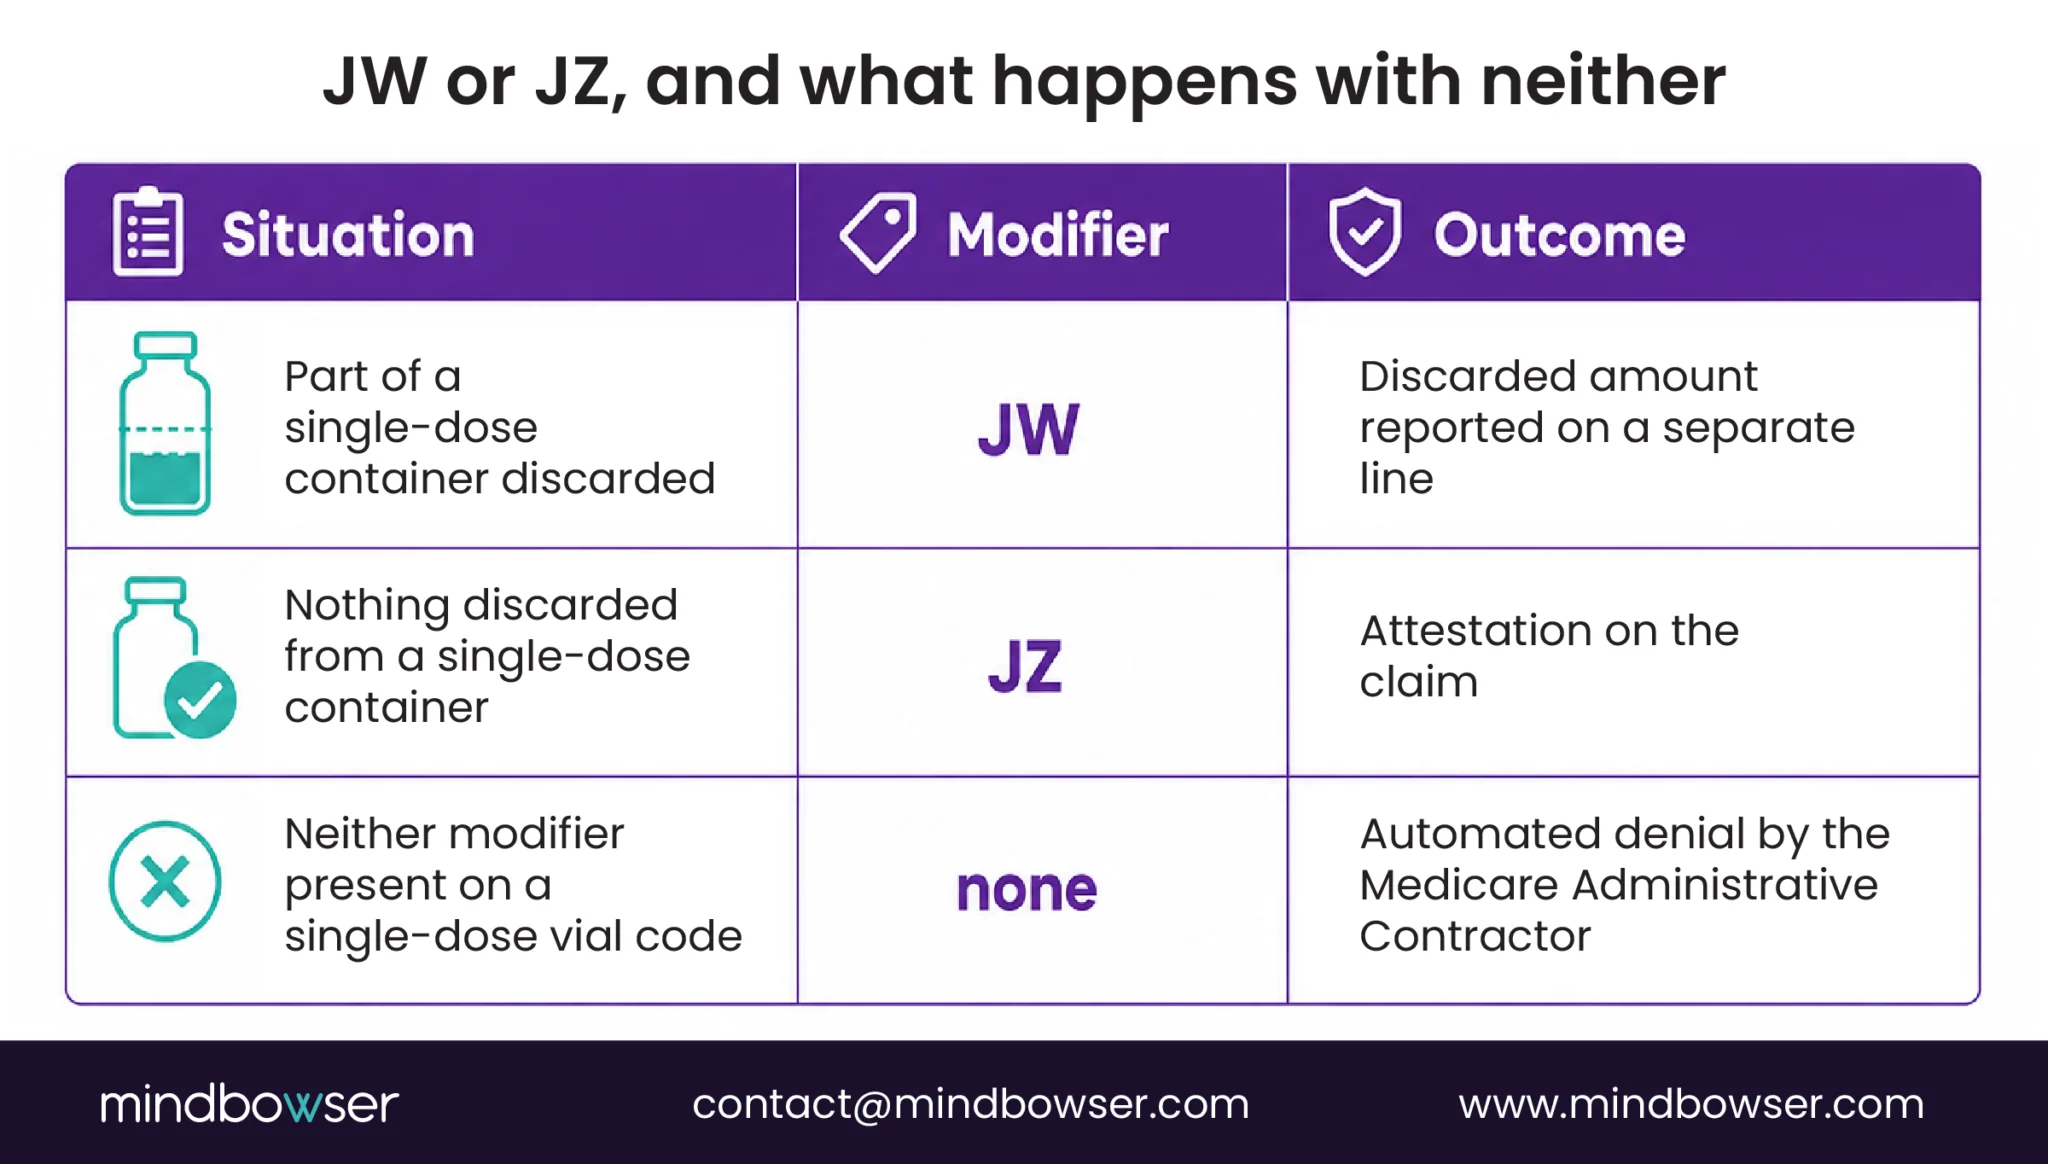
On a single-dose vial claim, you must report either the JW modifier or the JZ modifier. JW identifies drug that was discarded, billed on its own line. JZ attests that nothing was discarded. Medicare Administrative Contractors issue automated denials for single-dose vial codes that carry neither.
That is the rule. The policy sits with CMS, in its own JW and JZ modifier FAQ, which set the JZ attestation requirement from July 1, 2023, and it is implemented by the Medicare Administrative Contractors, whose drug wastage guidance is where most practices meet it. Both are official. Neither is a billing vendor’s interpretation.
- Part of a single-dose container was discarded Modifier: JW · Reported how: Discarded amount on a separate line
- Nothing was discarded from a single-dose container Modifier: JZ · Reported how: Attestation on the claim
- Neither present on a single-dose vial code Modifier: none · Reported how: Automated denial
Read that third case carefully. The absence of a modifier is not a risk factor or an audit exposure. It is a denial, applied automatically, every time. There is no reviewer to persuade and no documentation that rescues it.
Why a Rule with No Judgment in It Still Fails
Here is what I find genuinely interesting about this, and it is not a coding observation.
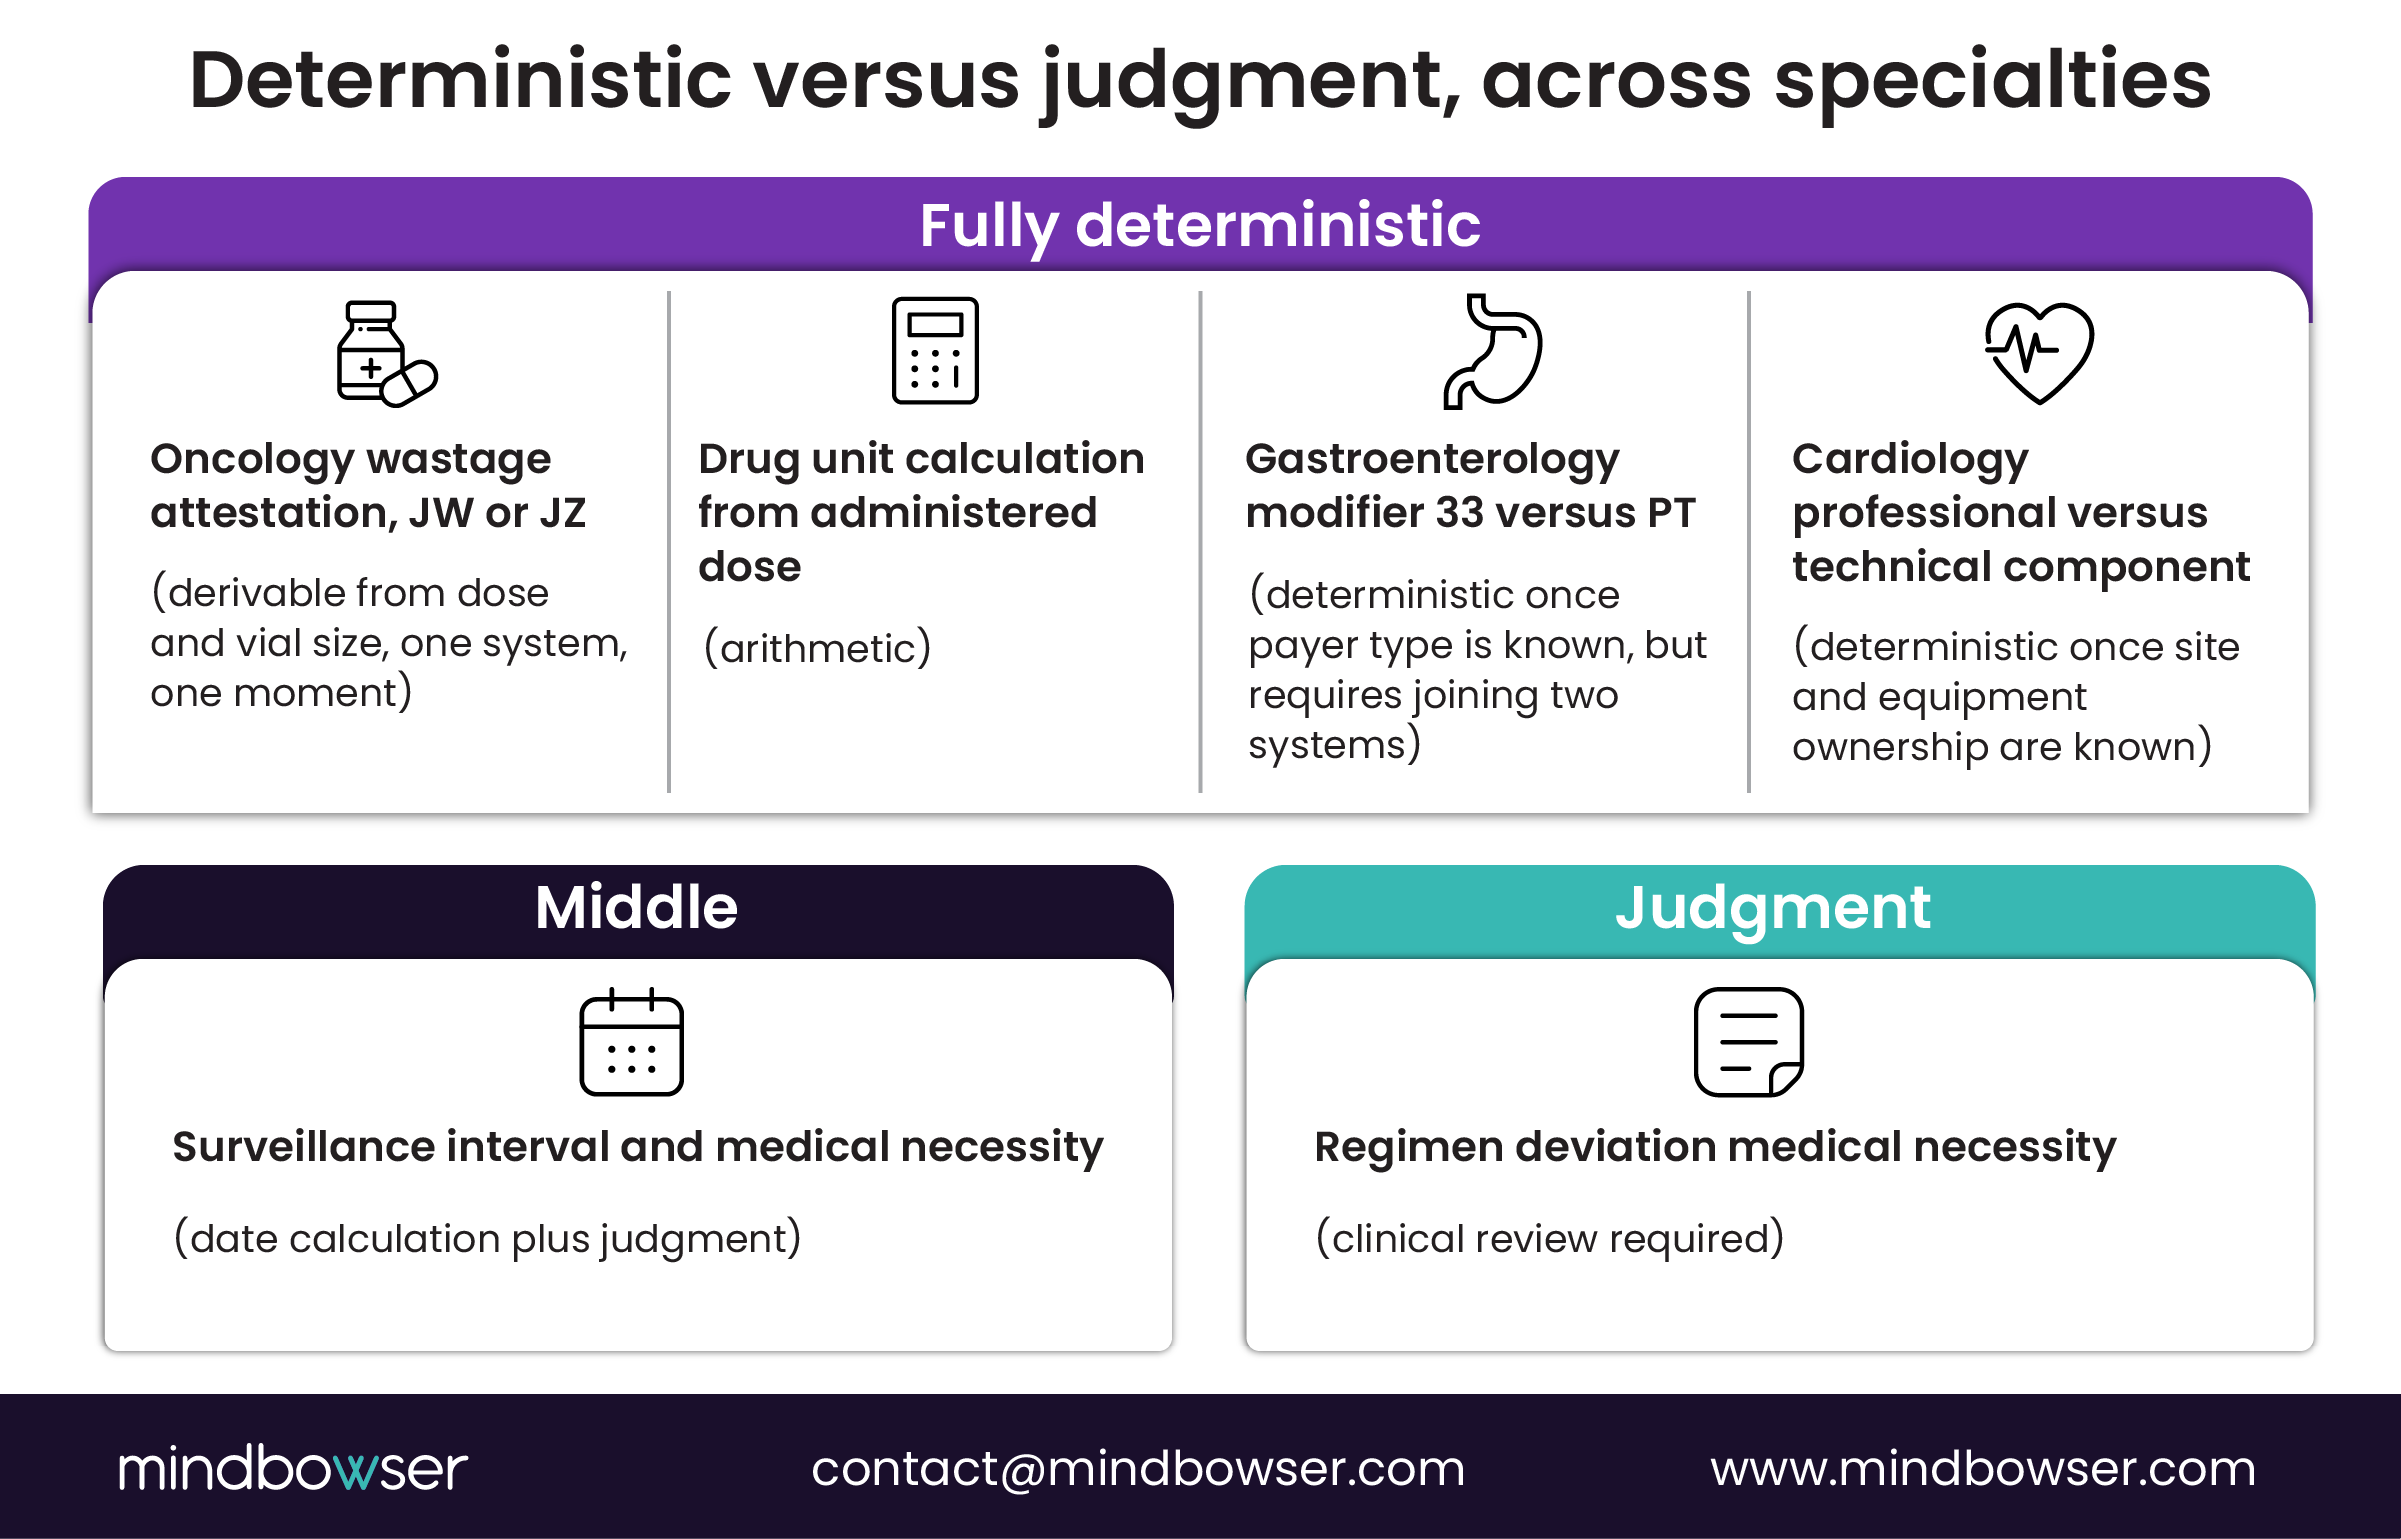
Compare the wastage attestation to the modifier problem in screening gastroenterology, where the correct answer depends on the payer and on what the physician found mid-procedure. That one at least requires joining two variables that live in different systems. It is a hard problem honestly earned.
The wastage attestation is not that. It is binary. The information needed to answer it exists at the moment of administration, in one place, held by one person. There is no payer variance to reconcile and no clinical judgment to preserve. A system given the administered dose and the vial size can derive the answer without asking anyone.
And it is still one of the most common denial causes in the specialty.
The reason is that the control is human memory, applied hundreds of times a month, to a field that feels administrative. The rule is deterministic. The enforcement is not. That gap between “fully specifiable” and “reliably done” is the single best argument for encoding a rule rather than training it, and oncology happens to provide the cleanest example of it in all of specialty billing.
I would put it more bluntly. If a rule can be stated completely in two sentences and a machine can evaluate it from data you already have, a person should not be the thing standing between you and payment.
The Four Things That Have to Be Right on a Drug Line
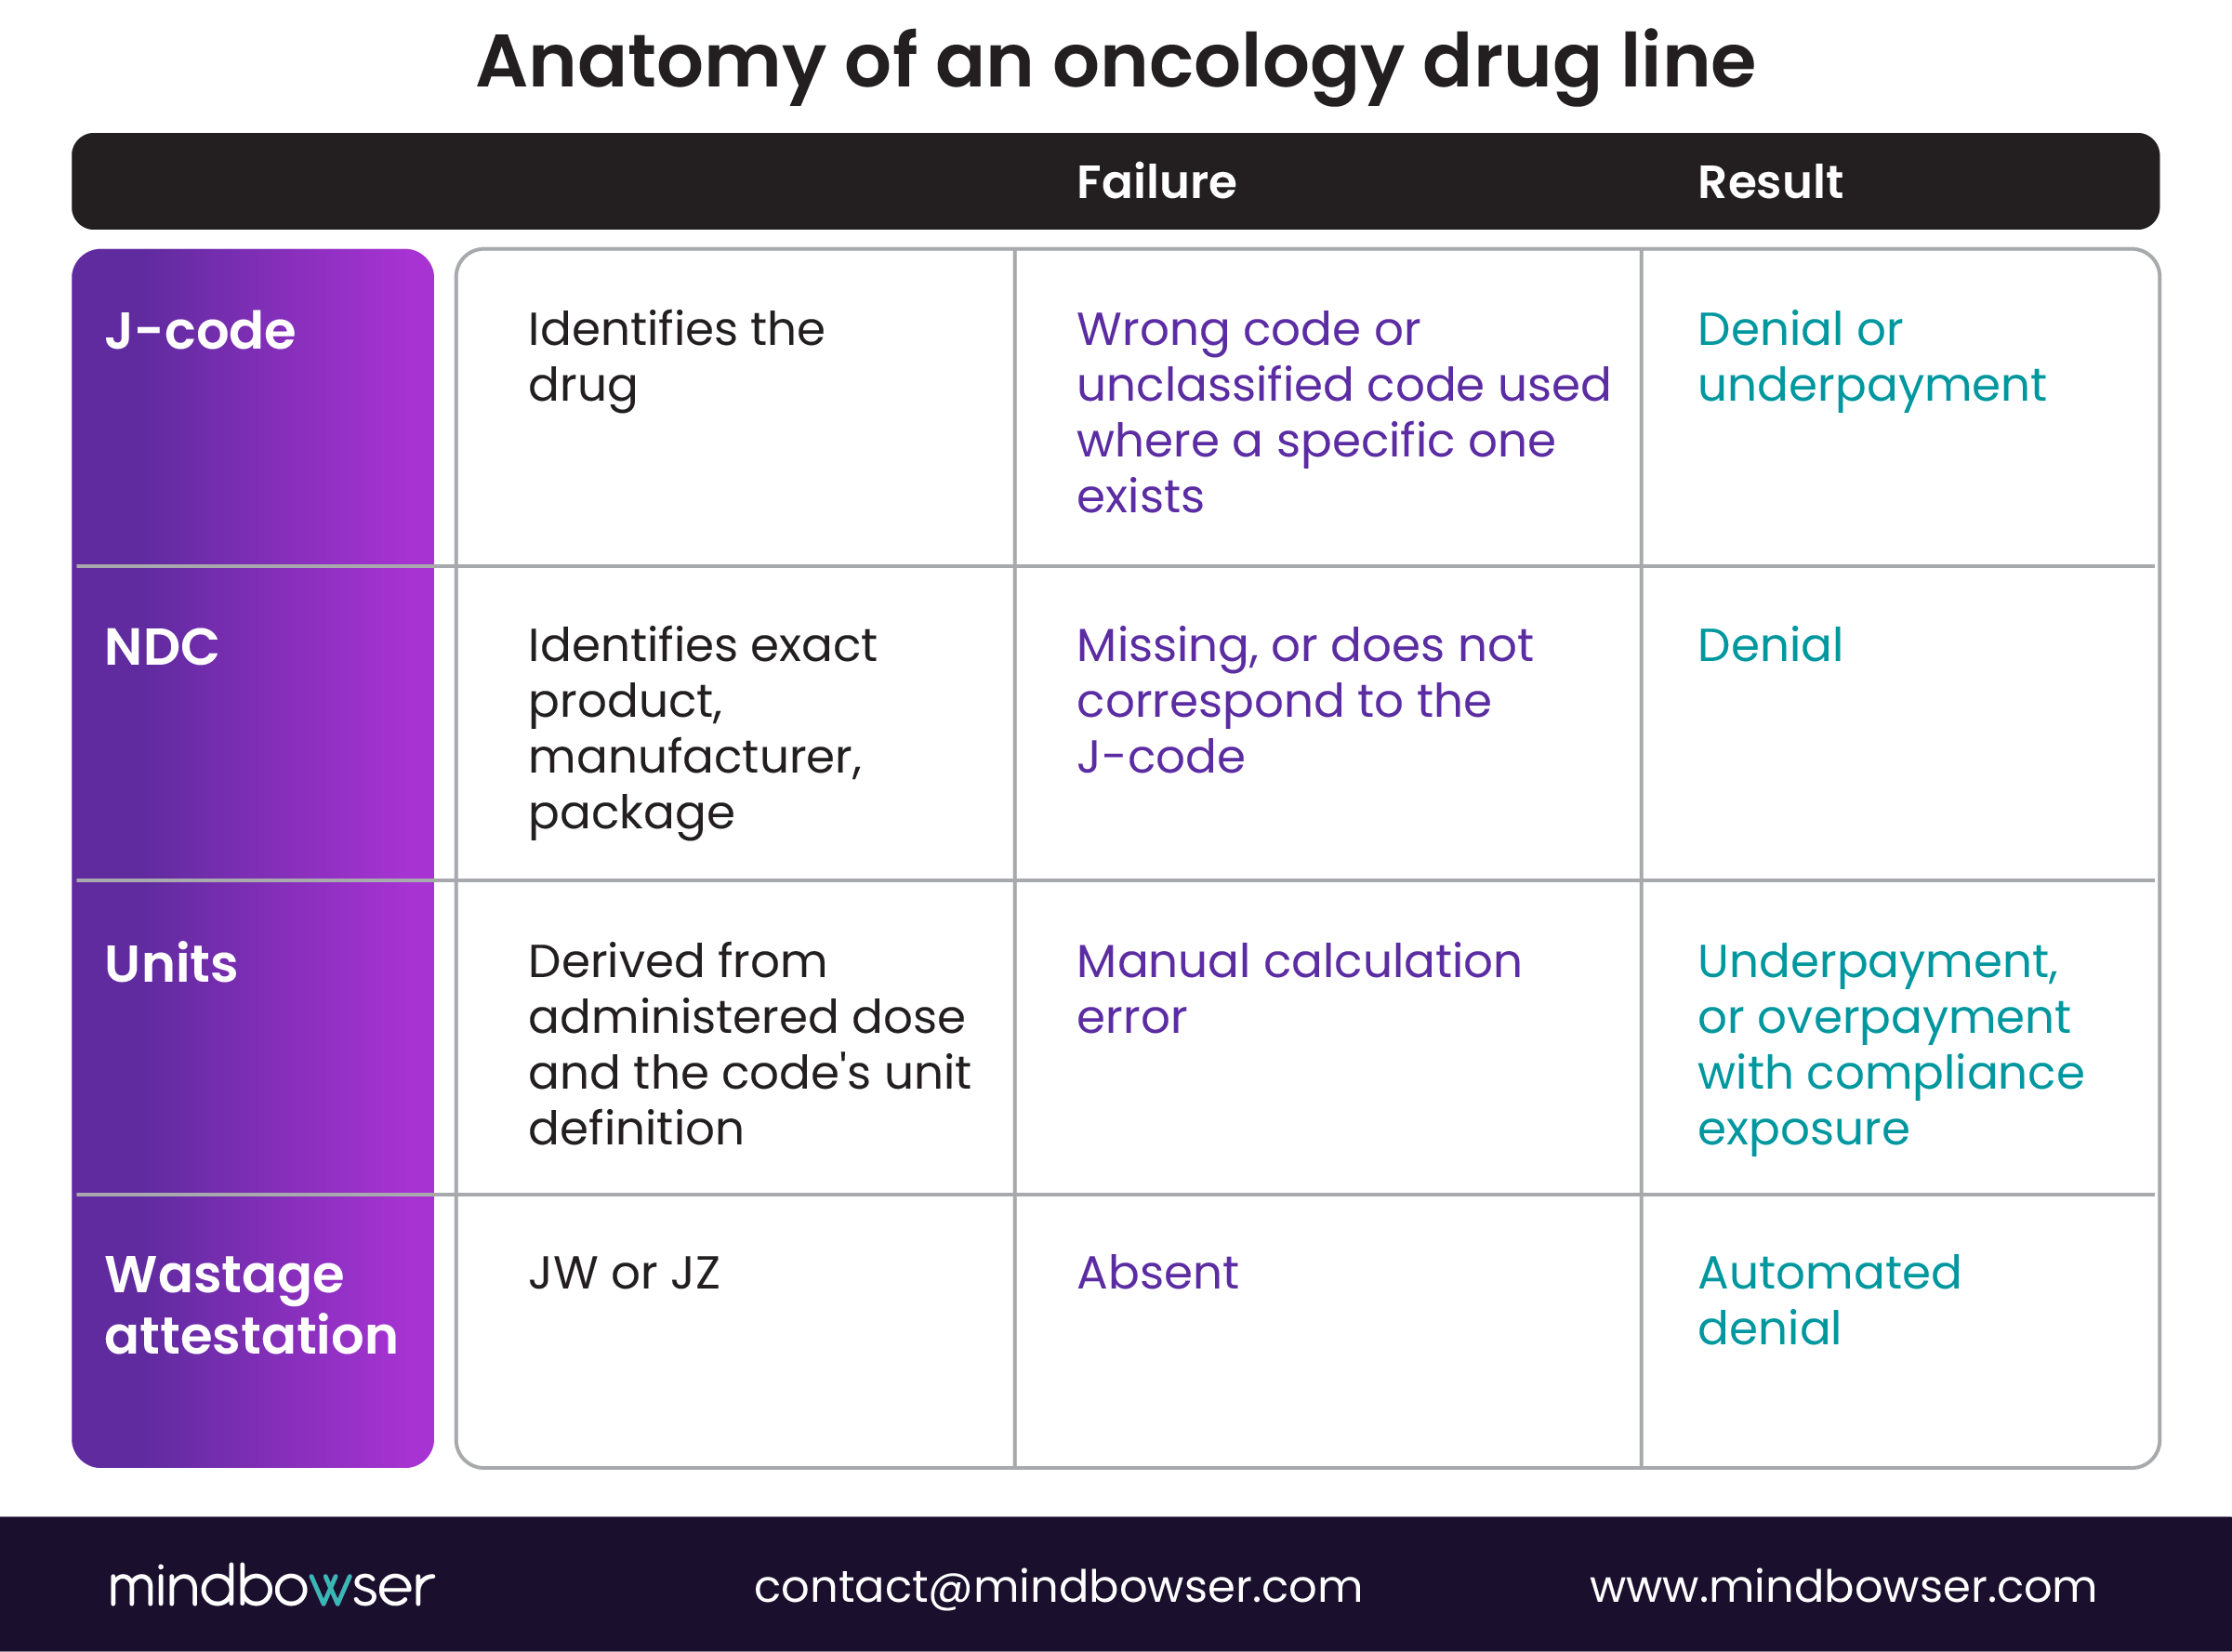
The wastage attestation is one of four, and the other three fail quietly rather than automatically.
- J-code selection. The Healthcare Common Procedure Coding System code identifying the drug. Selecting the wrong one, or defaulting to an unclassified code when a specific one exists, produces a denial or an underpayment depending on the payer.
- National Drug Code. The NDC identifies the exact product, manufacturer and package. Payers increasingly require it alongside the J-code, and the two have to correspond.
- Unit calculation. This is the one I would automate first. The number of billable units is derived from the administered dose and the code’s defined unit amount. It is arithmetic. Performed by hand, at volume, against drugs with different unit definitions, it produces errors in both directions, and overbilling errors carry consequences that underbilling errors do not.
- Wastage attestation. Covered above.
On a claim where the drug can be worth many multiples of the professional fee, an error rate that would be tolerable in another specialty is not tolerable here. That is an arithmetic consequence of the drug cost, not a claim about how careful anyone is being.
See If Your Oncology Claims Are Missing a JW or JZ Modifiers
340B Is About to Get Materially Harder
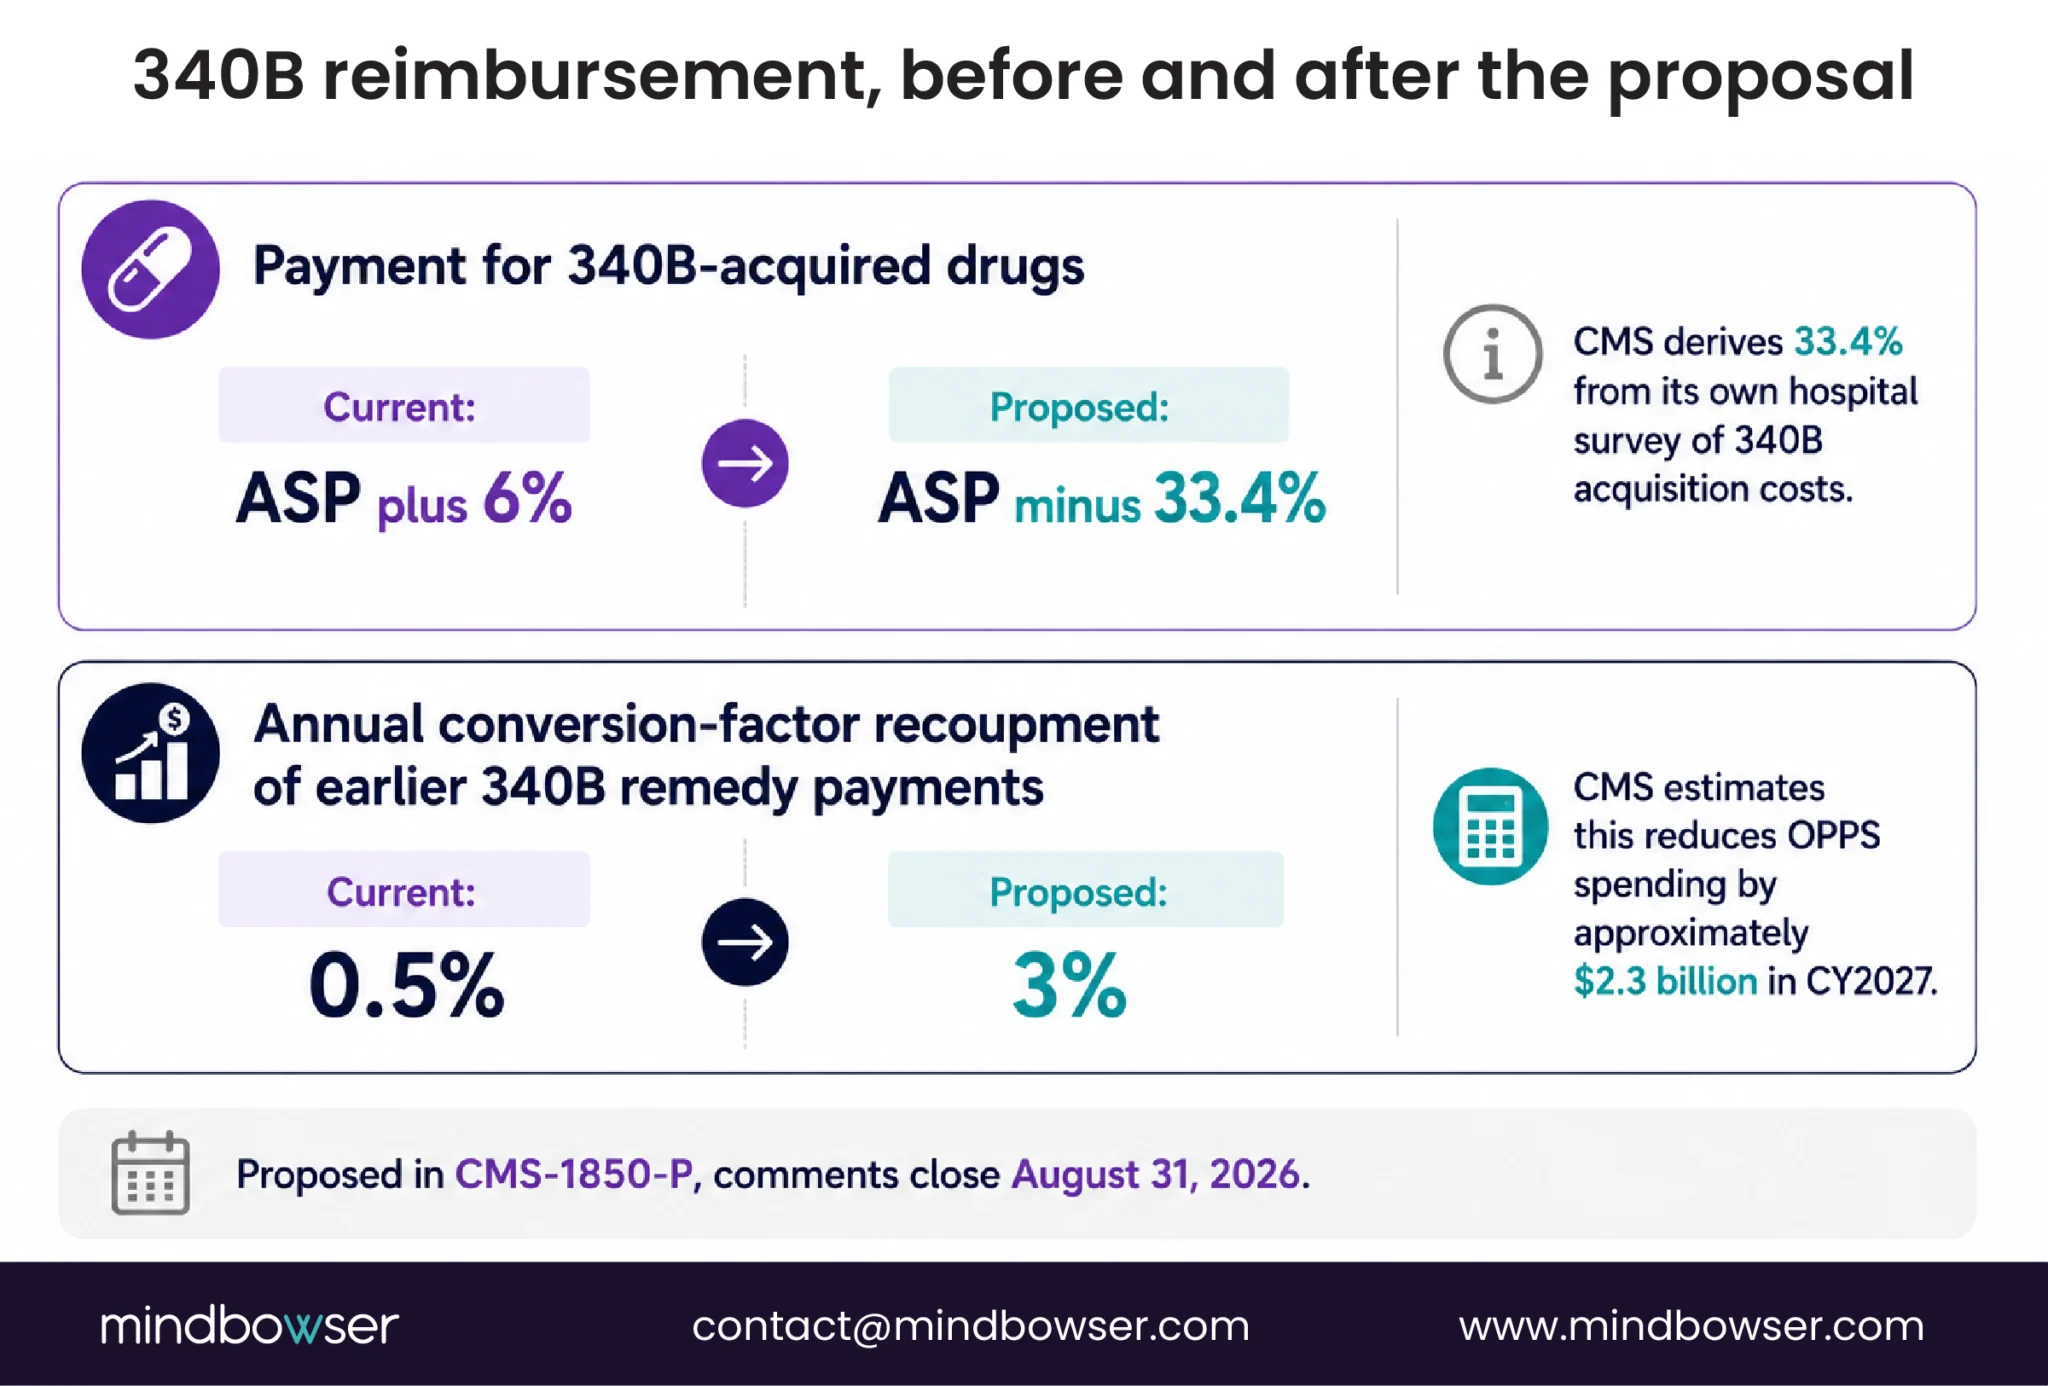
No specialty is more exposed to what CMS has proposed for CY2027 than oncology.
The CY2027 outpatient proposed rule, CMS-1850-P, published July 7, 2026, would pay ASP minus 33.4% for 340B-acquired drugs, down from ASP plus 6%. Average Sales Price is the benchmark Medicare reimburses drugs against, and CMS derives the 33.4% figure from its own hospital survey of 340B acquisition costs. Separately, the rule raises the annual conversion-factor reduction that recoups earlier 340B remedy payments from 0.5% to 3%. CMS estimates that second change alone reduces outpatient spending by approximately $2.3 billion in CY2027.
For a practice or hospital outpatient department whose drug spend is concentrated in oncology, that is not a rate adjustment at the margin. It changes the economics of the largest line on the claim.
Two operational consequences follow, and both are systems consequences rather than policy ones.
340B status has to be carried onto the claim accurately, every time. Reimbursement now depends on it in a way it did not when the differential was smaller. A drug’s 340B inventory status lives in pharmacy systems and the claim is built somewhere else.
340B does not exempt you from the wastage rule. Covered entities must still report JW or JZ, and some payers expect wastage reimbursement to reflect the lower acquisition cost. The compliance obligation is unchanged while the reimbursement underneath it moves.
Our explainer on what CMS-1850-P costs your revenue cycle covers the rest of the rule, including the site-neutral and Inpatient Only list changes. The comment period closes August 31, 2026.
Clinical Trial Billing Is a Reconciliation Problem
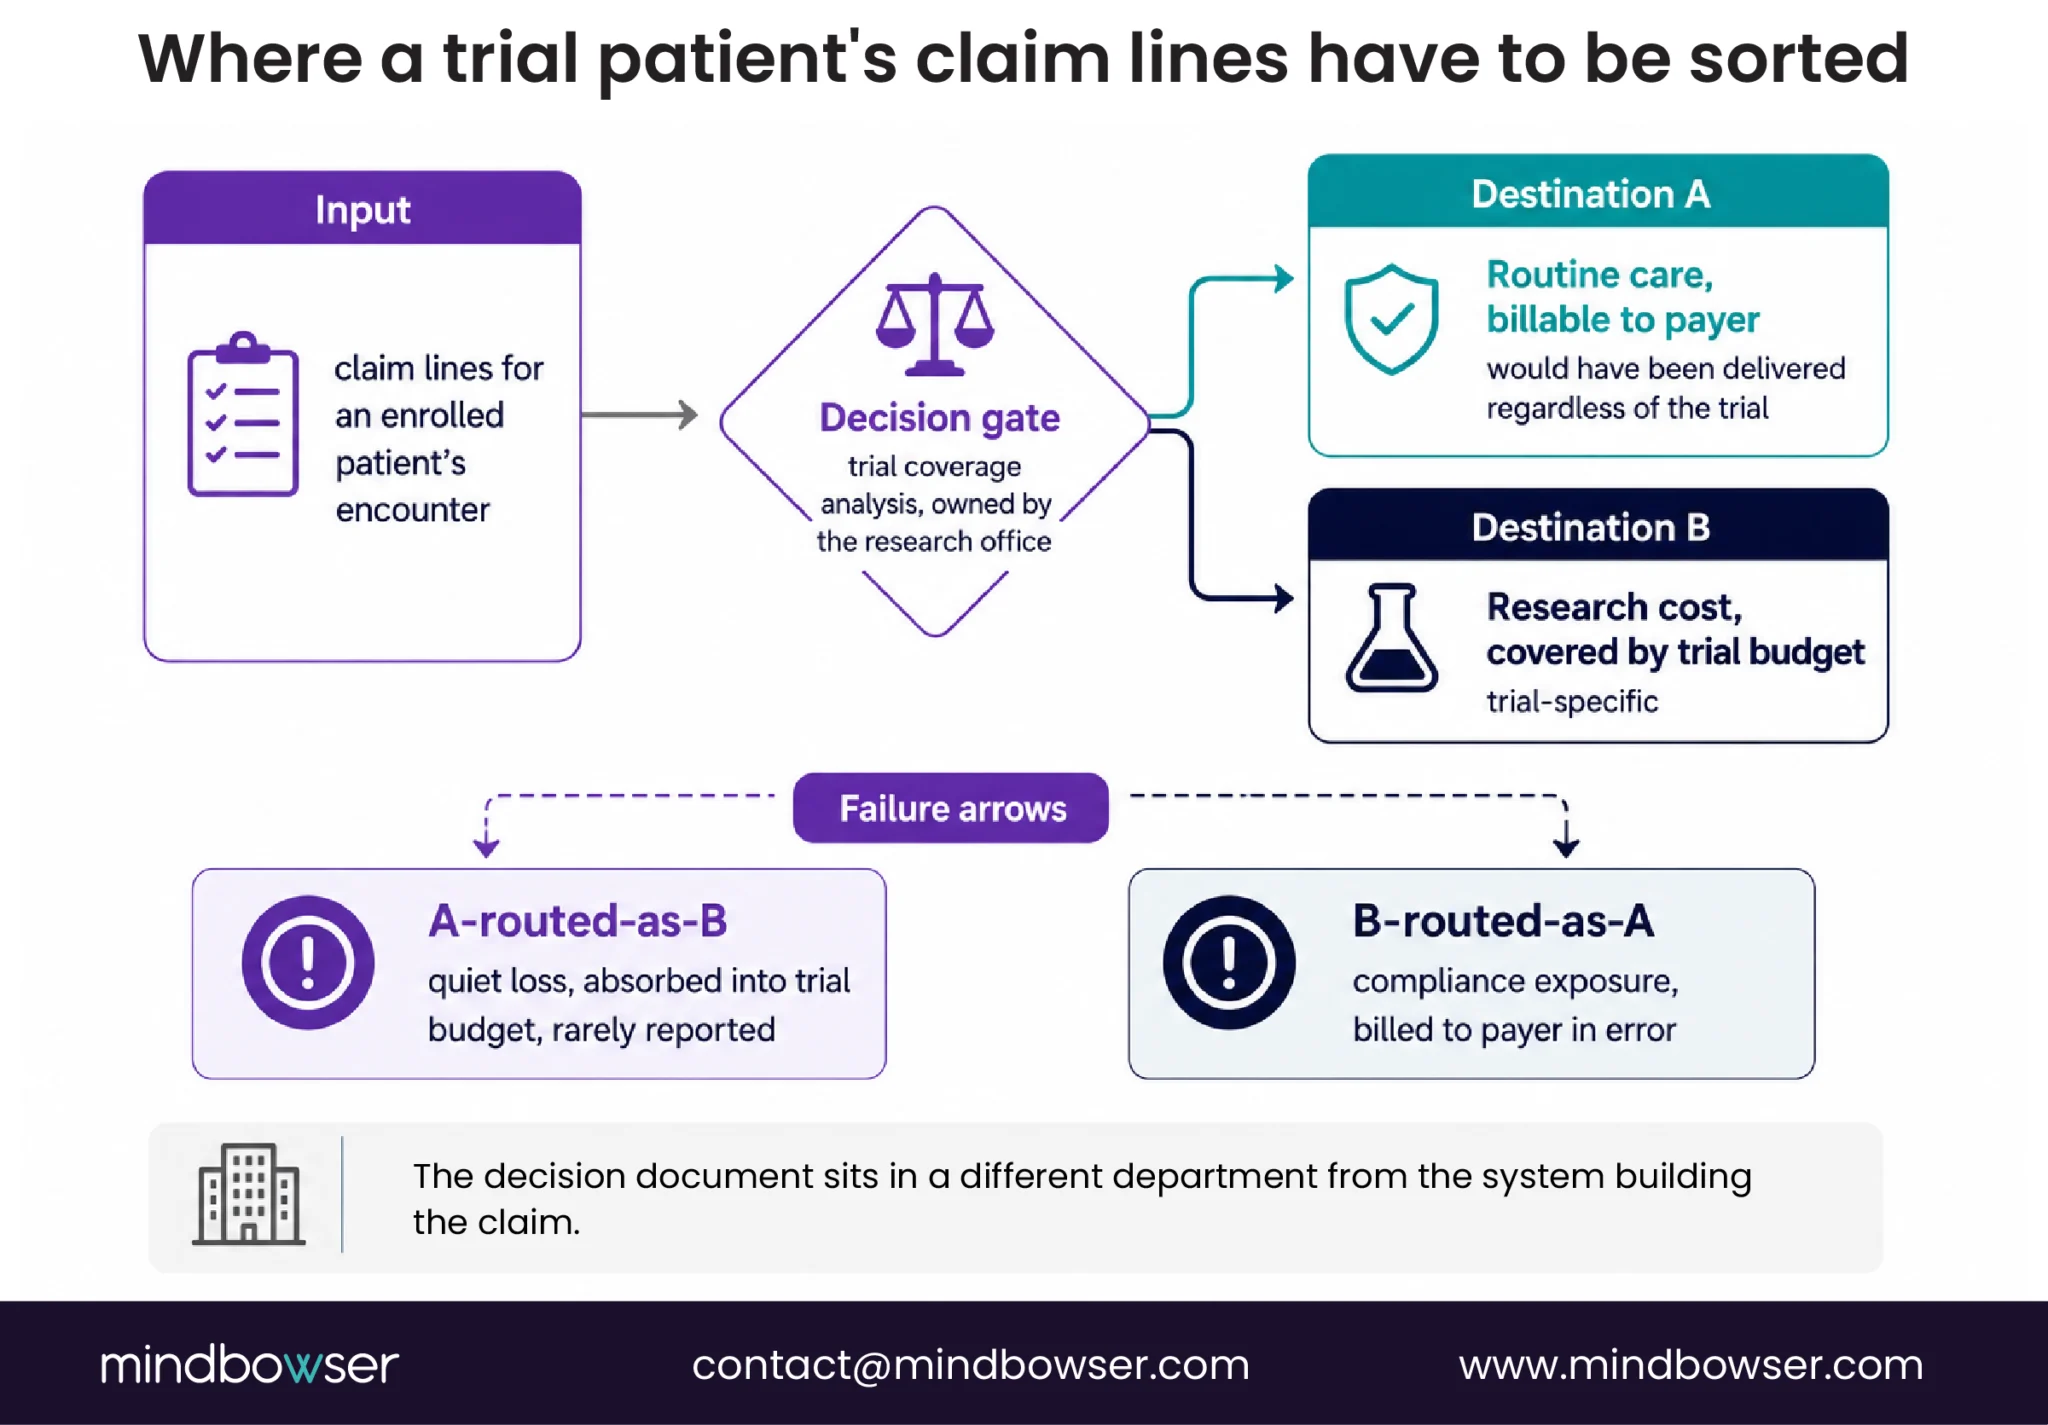
This one is barely discussed in the material published about oncology billing, and it is the least tractable thing on the list.
When a patient is enrolled in a clinical trial, the costs of their care split into two categories. Routine care that would have been delivered anyway is generally billable to the payer. Research costs specific to the trial are not, and are covered by the trial budget. The line between them is defined by the trial’s coverage analysis, a document produced during trial setup.
The billing problem is that the coverage analysis lives in the research office and the claim is built in the revenue cycle. Every claim line for an enrolled patient has to be checked against a document that another department owns, for a determination that changes by trial and sometimes by visit within a trial.
That is not a coding-skill problem. No amount of coder training fixes it, because the coder does not have the document. It is a reconciliation problem between two systems that in most organizations do not talk to each other, and the failure modes run in both directions: billing the payer for a research cost is a compliance problem, and absorbing a routine cost into the trial budget is a quiet loss nobody reports.
The organizations that handle this well have made the coverage analysis machine-readable and joined it to the claim at the line level. That is a data-integration project with a compliance benefit, which is an unusual and rather good combination.
Where Oncology Claims Actually Die
Five mechanisms, ranked by how mechanically preventable they are.
- Missing wastage attestation. Fully deterministic. Automated denial. Preventable at claim build with no judgment required.
- Unit miscalculation. Arithmetic. Fully automatable from the administered dose.
- Prior authorization on high-cost agents. Deterministic as a requirement, administratively heavy in practice. The federal Interoperability and Prior Authorization rule, CMS-0057-F requires affected payers to run a Prior Authorization application programming interface by January 1, 2027, which changes the mechanics substantially. Our prior authorization services page covers that integration work.
- Step therapy denials. Partly mechanical. The requirement is knowable in advance from the payer’s policy, and the appeal is built on clinical guideline citations. Practices that pre-check the requirement rather than appealing after the fact spend far less on it.
- Medical necessity on regimen deviation. Genuine clinical judgment. This is the one that needs a person, and it should be where your expert time goes rather than on the four above.
I am not going to reprint the clean-claim-rate percentages that appear across the billing services ranking for this topic. They are published without methodology, sample or source, and repeating them would add nothing except the appearance of rigor.
What is defensible is the ordering. Four of the five are rules. Denial management that enforces the rules frees your clinical reviewers for the one case that actually needs them, and a revenue cycle analytics view that slices denials by mechanism tells you which of the five is actually costing you, which is not always the one people assume.
What Your Systems Have to Know
Four requirements, and none of them is exotic.
- Wastage attestation enforced at claim build, never optional. If a single-dose vial code can leave your system without JW or JZ, that is a configuration decision you are making, whether or not anyone decided it.
- Units derived, not entered. The calculation from administered dose to billable units is computation. Typing it is a choice to introduce error.
- 340B inventory status carried onto the claim. Pharmacy knows it. The claim needs it. With the proposed reimbursement differential, the cost of getting that handoff wrong rises sharply.
- Trial coverage analysis joined to the claim at line level. The hardest of the four and the one with the clearest compliance payoff.
The engineering reality is worth stating plainly, because vendor material tends to skip it. Connecting to a major electronic health record or a pharmacy system is well-understood work. The difficulty is the last mile: reconciling identifiers across systems that were never designed to agree, handling the encounters that fall outside the standard path, and writing results back where the billing staff already work rather than into a dashboard they have to remember to open. Anyone presenting that part as routine has not done it.
Outsource, Buy, or Build
Almost every page ranking for this topic is published by a company selling one of these three. Here is the version that is not.
Outsourcing is the right answer for many oncology practices, and the threshold is arguably higher here than in other specialties because the drug-billing expertise is genuinely specialized and hard to hire. A partner who does only oncology billing will know things your generalist biller will not. Outsourcing revenue cycle management covers where the line usually falls, and our list of revenue cycle management companies is a starting point for a shortlist.
Where the oncology case differs is drug-cost concentration. Everywhere else, outsourcing transfers a labor problem. Here it also transfers exposure on the most expensive line of the claim, which raises the bar on the partner and makes the audit trail matter more than it would elsewhere.
Building earns its keep when your denials concentrate in the deterministic mechanisms above, your volume funds ongoing maintenance, and the fix has to live inside a workflow you control. Oncology meets the first condition unusually well, because the top two denial causes have no judgment in them at all.
The underestimated cost is maintenance, not build. Payer policies change continuously, and CMS-1850-P is a live demonstration that the reimbursement basis itself can move.
For the same argument through different specialty mechanics, our cardiology revenue cycle guide covers a code-set migration, gastroenterology revenue cycle management covers a payer-dependent decision tree, and behavioral health revenue cycle management covers session-based billing with carve-out payers. Practices with rural or critical access exposure have a different profile again, covered in critical access hospital reimbursement.
Six Checks Before Your Next 340B Cycle
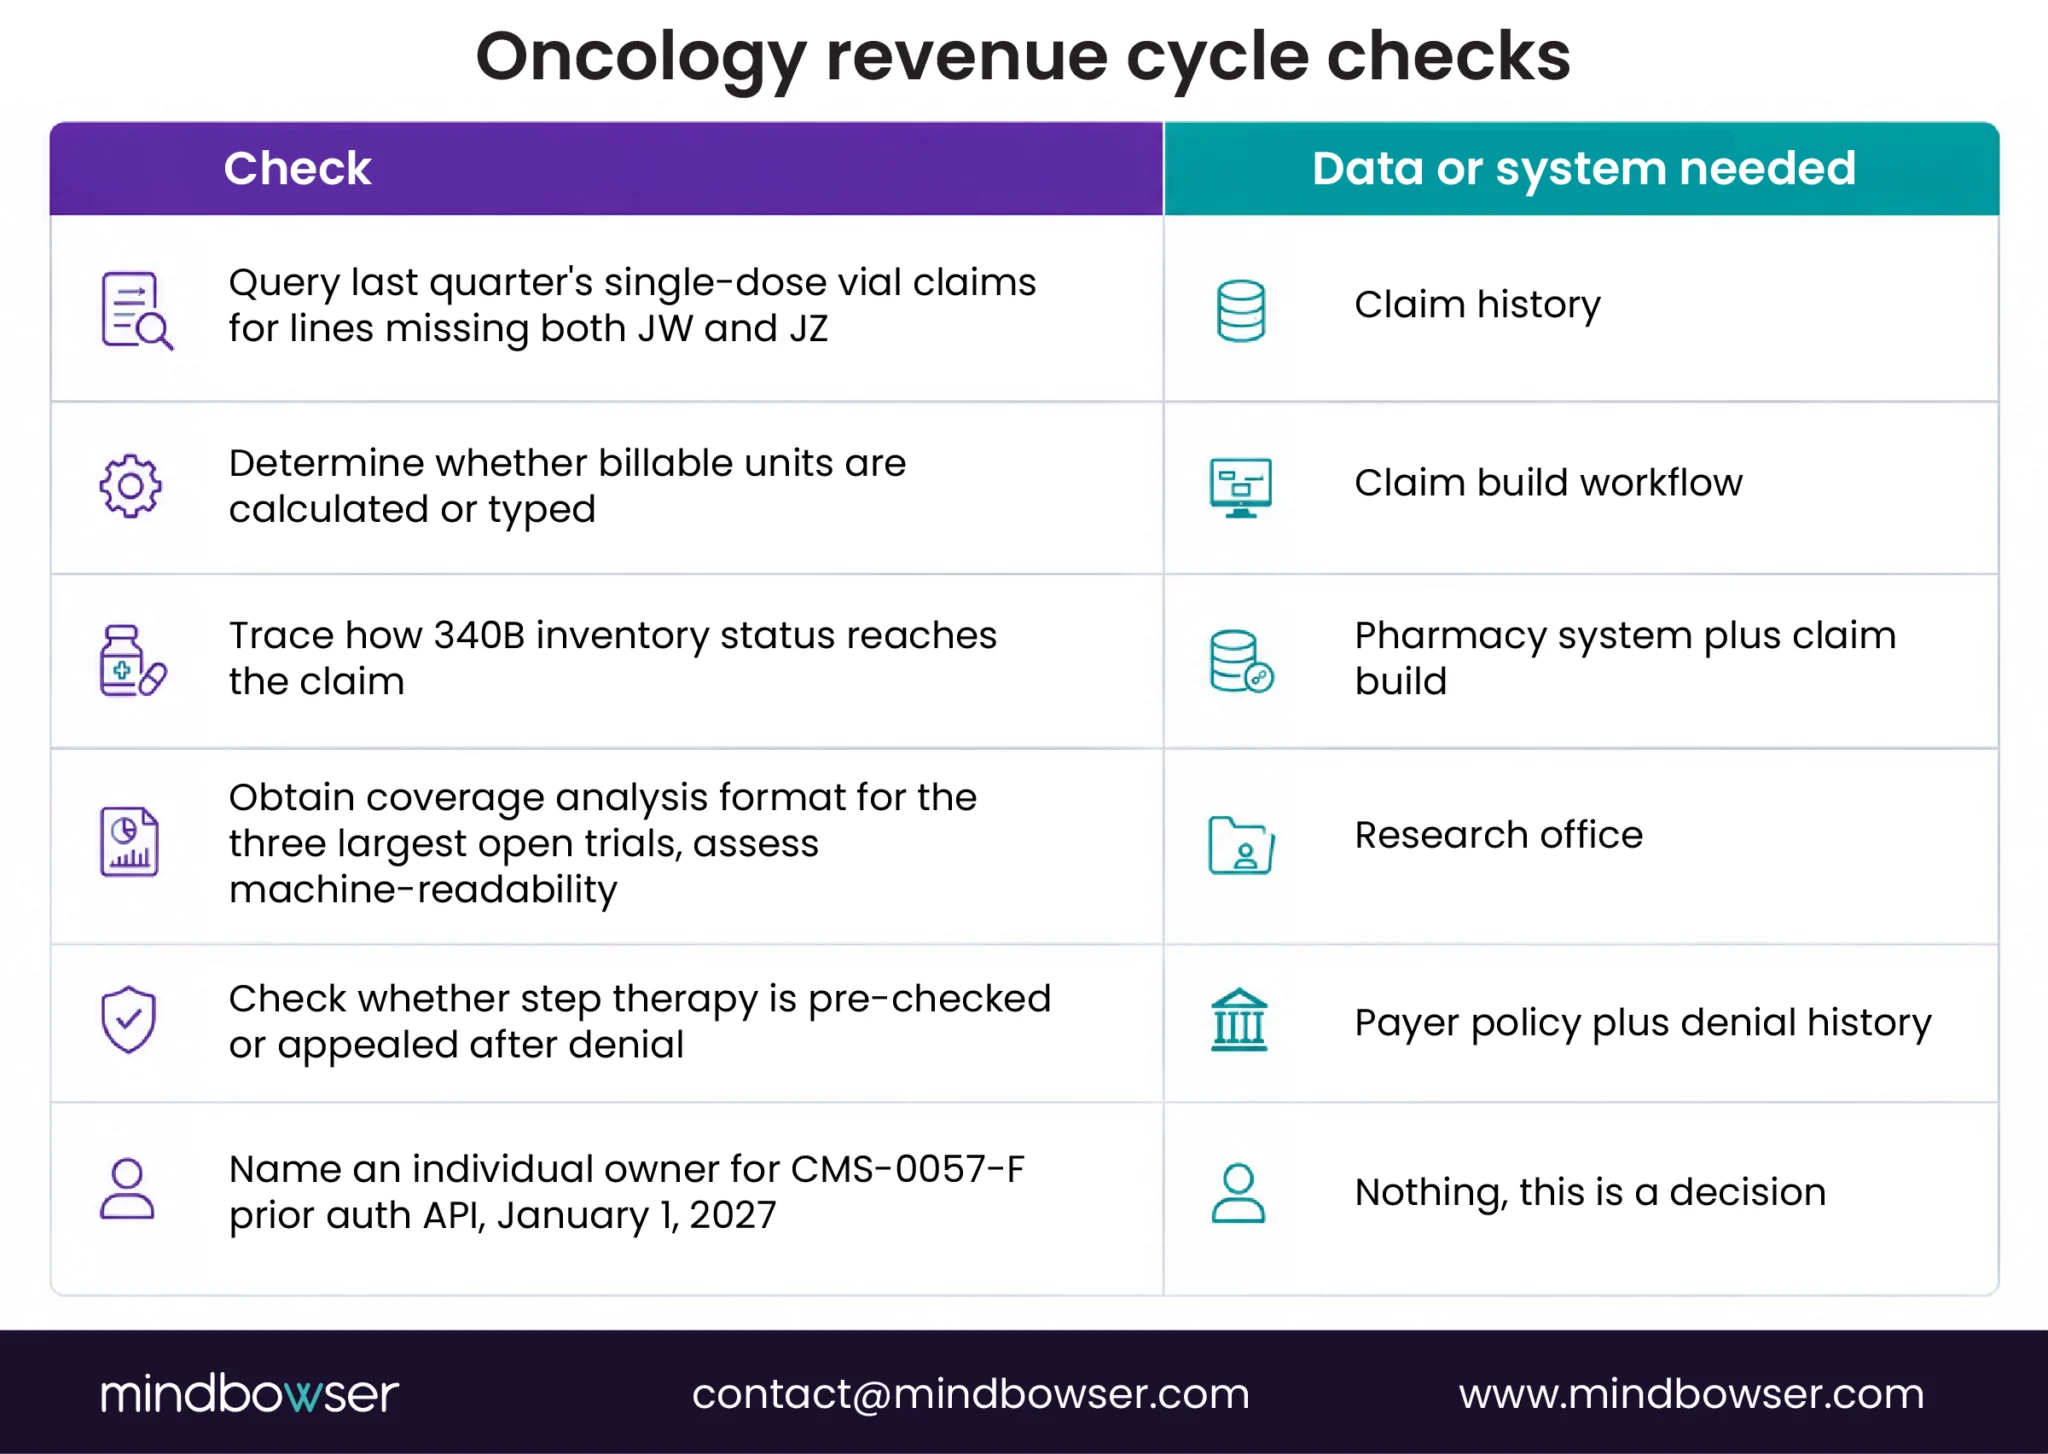
In the order I would run them
- Query your last quarter of single-dose vial claims for lines missing both JW and JZ. This is a database question with a yes or no answer, and it is the highest-yield thing on this list.
- Determine whether billable units are calculated by your system or typed by a person. If typed, that is your next automation, ahead of anything more sophisticated.
- Trace how 340B inventory status reaches the claim. If the answer involves a person checking a second system, price what the proposed ASP minus 33.4% does to the cost of that handoff being wrong.
- Ask the research office for the coverage analysis format for your three largest open trials, and find out whether anything about it is machine-readable today.
- Check whether step therapy requirements are pre-checked before submission or appealed afterward. The second is far more expensive and the information needed for the first is published.
- Name an individual owner for the January 1, 2027 prior authorization API deadline. A person, not a team.
Five of the six cost time rather than money. Their output is also what you would need in hand before you could sensibly evaluate any vendor, which makes them worth doing even if you intend to outsource all of it.
Conclusion
Oncology revenue cycle management works best when preventable billing errors are handled by systems, not memory. Automating rules around drug units, JW/JZ modifiers, 340B status, and claim routing can reduce denials and compliance risks while allowing teams to focus on cases that genuinely require clinical judgment.
It is the financial process a cancer care practice runs from scheduling through final payment. What distinguishes it from other specialties is that the drug, rather than the procedure, is usually the largest value on the claim, so correctness depends on drug code selection, national drug code reporting, billable unit calculation and a mandatory wastage attestation.
JW identifies drug discarded from a single-dose container and is reported on a separate line for the discarded amount. JZ attests that nothing was discarded from a single-dose container. One of the two must appear on single-dose vial claims. Claims carrying neither receive an automated denial.
No. Covered entities must still report JW or JZ. Some payers also expect wastage reimbursement to reflect the lower 340B acquisition cost, so the reporting obligation continues even as the reimbursement basis changes.
The rule proposes paying ASP minus 33.4% for 340B-acquired drugs, down from ASP plus 6%, and raising the annual conversion-factor recoupment tied to earlier 340B remedy payments from 0.5% to 3%. Both are proposals, not final policy, with a comment period closing August 31, 2026.
The trial’s coverage analysis defines which costs are routine care billable to the payer and which are research costs covered by the trial budget. The practical difficulty is that this document is produced and owned by the research office while the claim is built in the revenue cycle, so the split has to be applied at claim line level across a departmental boundary.
Five mechanisms account for most of it: missing wastage attestation, unit miscalculation, prior authorization on high-cost agents, step therapy requirements, and medical necessity on regimen deviation. Only the last requires clinical judgment. The other four are rules that can be enforced before submission.





