














 BLOGS
 NEWSROOM
 CASE STUDIES
 WEBINARS
 PODCASTS
 ASSET HUB
 EVENT CALENDAR
























TL;DR
- No standardized national Medicaid CCM benefit coverage varies by state and by FFS vs. MCO plans.
- For dual-eligible patients, Medicare bills first; Medicaid typically covers eligible cost-sharing.
- D-SNP plan type determines whether claims follow integrated, companion, or crossover processing.
- Multi-state CCM platforms need patient-level payer flagging instead of one nationwide billing workflow.
- Incorrect payer logic often surfaces later as claim denials or payment delays.
The Short Answer, and Why It’s Unsatisfying

Medicaid coverage for chronic care management is not standardized the way Medicare’s is. There’s no single national CPT-code-based CCM benefit under Medicaid. Coverage depends on individual state policy, and it varies meaningfully: some states reimburse care coordination through health home programs or managed care arrangements, others don’t have an equivalent benefit at all.
This is a genuinely different regulatory picture than the rest of this cluster’s Medicare-focused content, and it deserves its own answer rather than an assumption borrowed from the Medicare rules.
What Actually Happens for Dual-Eligible Patients
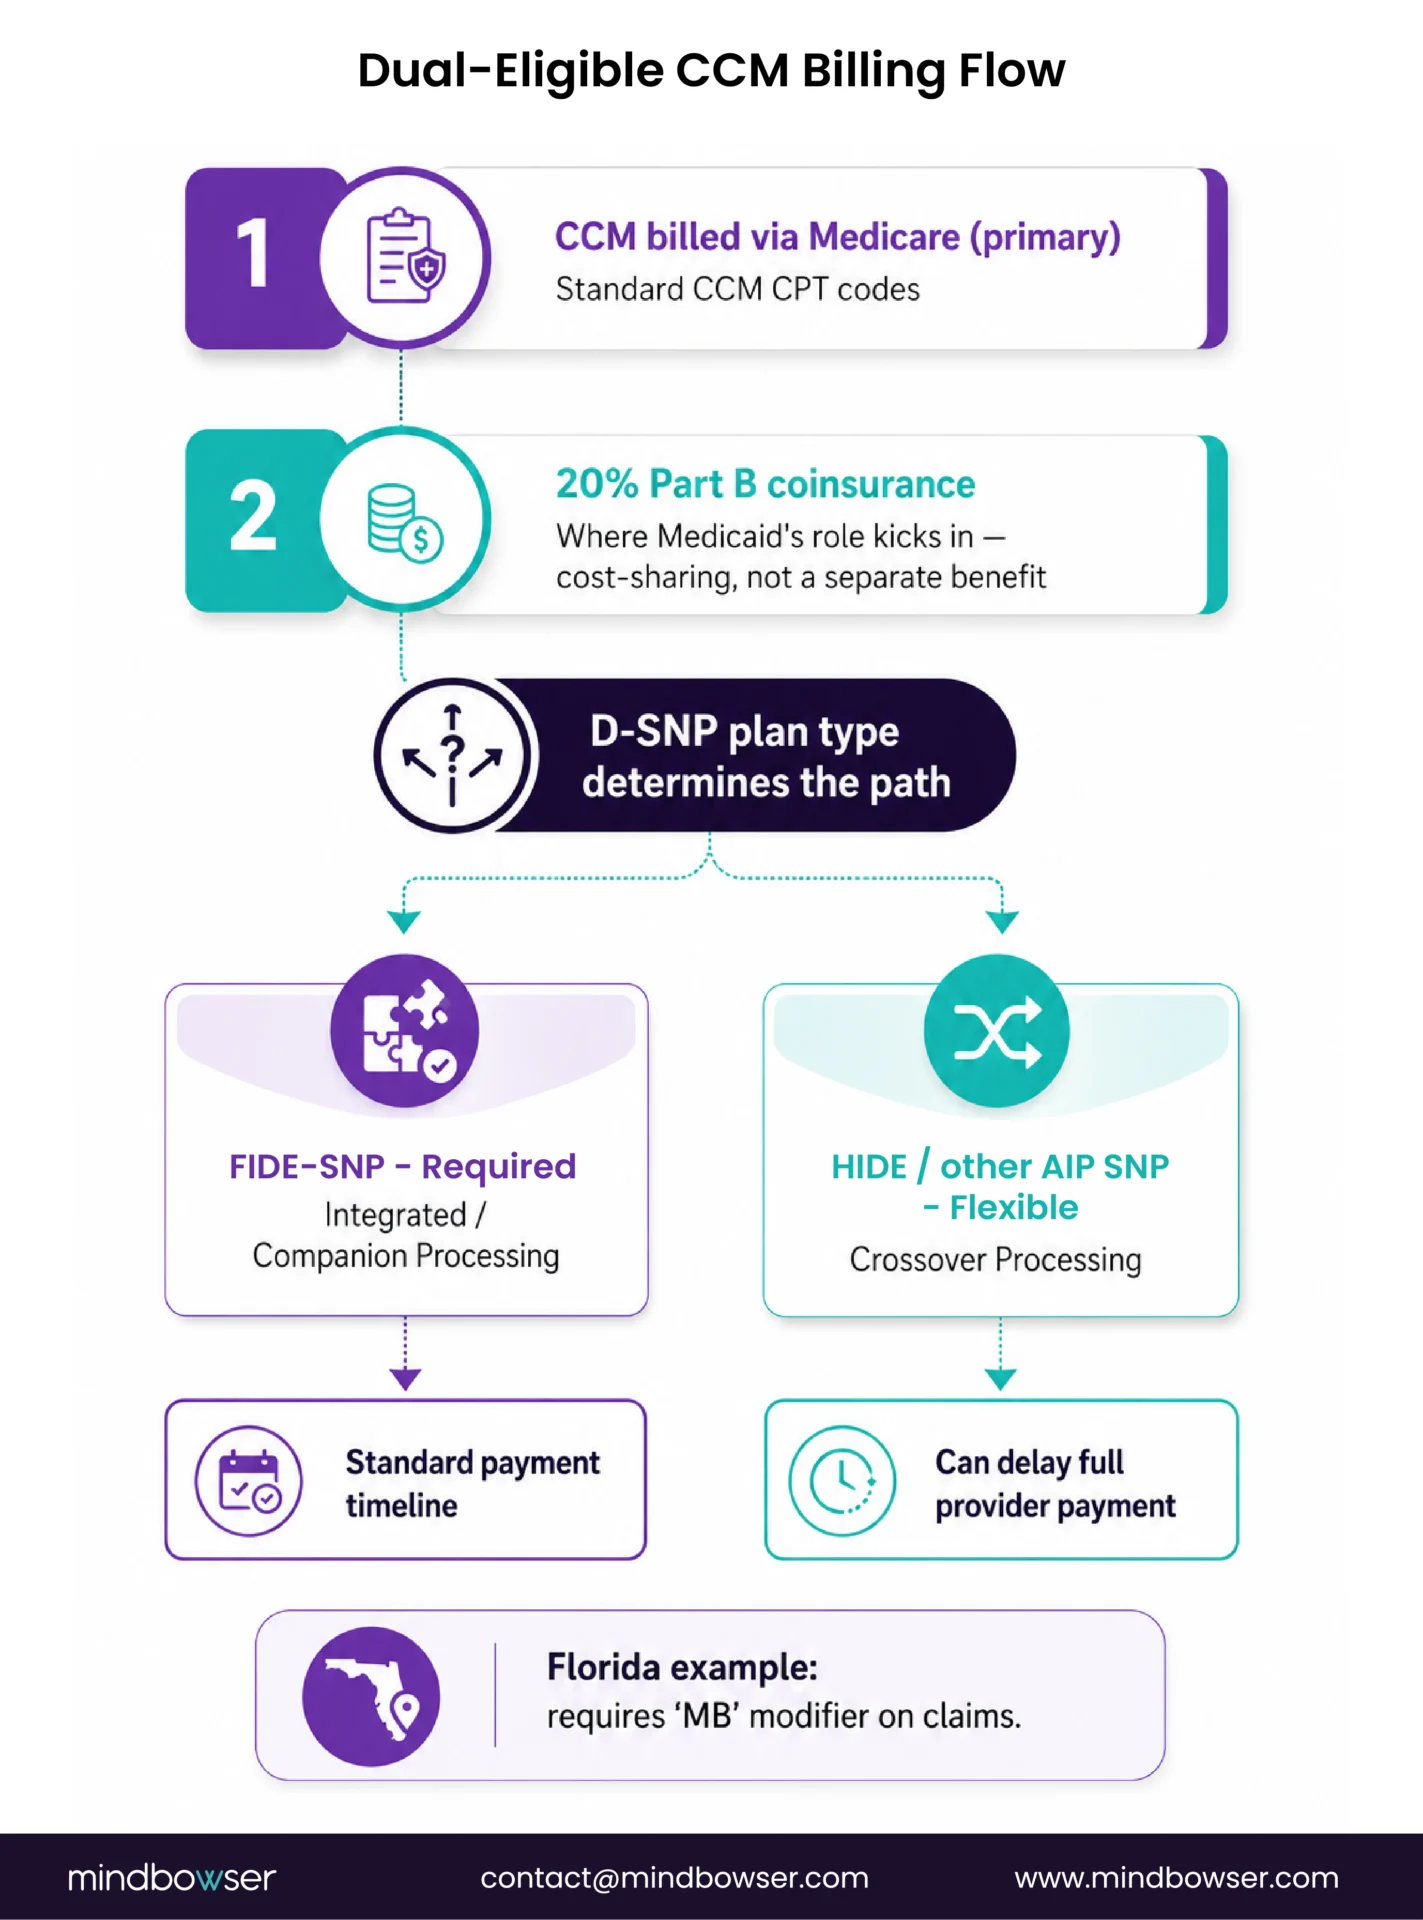
For patients covered by both Medicare and Medicaid (dual-eligible beneficiaries), Medicare is billed as the primary payer for CCM. Medicaid’s role, where the state program participates, is typically covering the cost-sharing Medicare doesn’t (the standard 20% Part B coinsurance that otherwise applies to CCM). This means a dual-eligible patient may face zero out-of-pocket cost for CCM, even though the CCM billing itself still runs through Medicare’s standard CPT-code structure, not a separate Medicaid mechanism.
How that coordination actually happens operationally depends on plan structure, and 2026 is a meaningful year for this because CMS continues expanding Dual Special Needs Plans (D-SNPs), which consolidate what used to be separate Medicare-to-Medicaid crossover processes under a single managed plan. Fully Integrated Dual Eligible SNPs (FIDE-SNPs) are required to use integrated or companion claims processing; Highly Integrated (HIDE) and other Applicable Integrated Plan (AIP) SNPs have more flexibility and can also use crossover processing.
Where crossover processing is used, Coordination of Benefits Agreements allow Medicare to send cost-sharing claims directly to the state Medicaid agency, but crossover is specifically slower than integrated or companion processing, which means full provider payment can lag. Some states add their own requirements on top of this; Florida, for instance, requires an “MB” modifier on claims to flag a service as Medicare-paid. A billing workflow that assumes one dual-eligible claims path nationwide will be wrong the moment it hits a state or plan-type variation like this.
Related read: Chronic Care Management Billing in 2026: From CPT Codes to APCM Strategy
Building a CCM Platform That Handles Medicaid and Medicare Billing Correctly?
Why State Variation Matters Operationally

A hospital system or practice operating across state lines, or a digital health platform building for a national Medicaid-adjacent population, cannot apply one CCM-Medicaid assumption everywhere. The variation isn’t just state-to-state; it runs within a single state too, between fee-for-service (FFS) and managed care organization (MCO) structures.
Some states flag CCM or RPM as simply not payable under their FFS Medicaid program, while the same state’s Medicaid MCO plans may still fund care coordination through a per-member-per-month payment, a value-based contract, or a quality incentive that doesn’t run through a CCM-specific CPT code at all.
A workflow built assuming Medicaid coverage mirrors Medicare’s CCM structure will be wrong in states without an equivalent health-home or managed-care care-coordination benefit, and correct in states that do have one, and potentially wrong again depending on whether that specific patient sits in FFS or an MCO plan within the same state.
Related read: RPM + CCM: How to Stack Billing for Maximum Revenue Per Patient
What This Means for Technology and Workflow Design
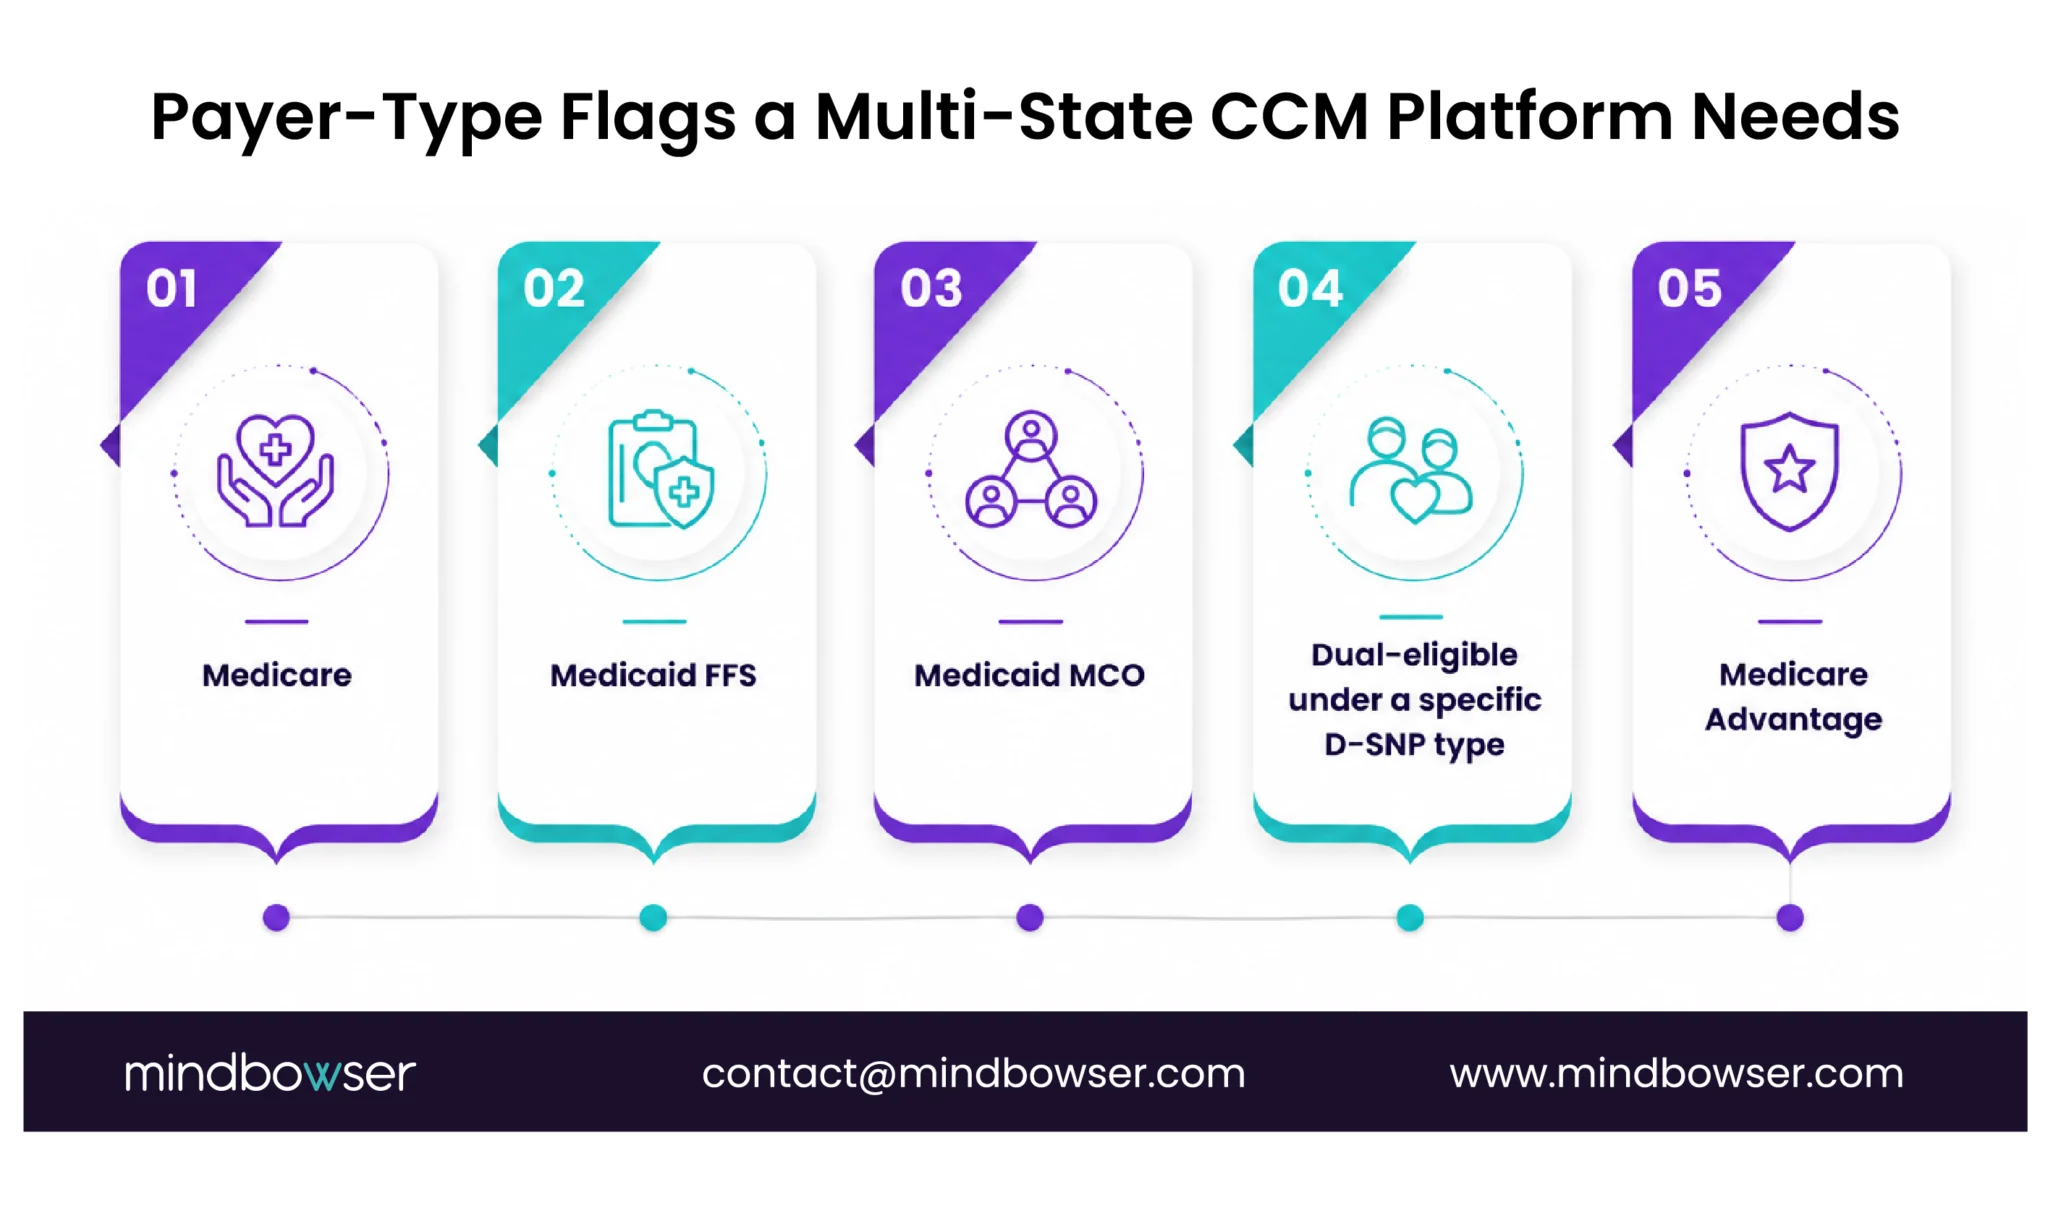
A CCM platform serving a multi-state population needs to flag payer type at the patient level (Medicare, Medicaid FFS, Medicaid MCO, dual-eligible under a specific D-SNP type, Medicare Advantage) and apply the correct billing logic for each, rather than assuming one CMS-wide rule set applies uniformly.
For dual-eligible patients specifically, the workflow needs to correctly bill Medicare as primary while routing the Medicaid cost-sharing claim through the right processing path for that patient’s plan type, integrated, companion, or crossover, since crossover processing runs slower and can delay full provider payment if the workflow doesn’t distinguish it upfront.
How Mindbowser Approaches This
We build CCM platforms that handle payer-type variation as a structural part of the workflow, not an edge case handled manually. That includes correctly sequencing Medicare-primary billing for dual-eligible patients, flagging state-specific Medicaid care-coordination benefits and FFS-vs-MCO differences where they exist, and building for the specific claims-processing path a given D-SNP plan type actually requires rather than assuming one crossover process fits every dual-eligible patient.
Building or fixing a CCM program that handles this variation correctly, rather than patching it in after a denied claim surfaces the gap, is part of the same platform work we do end to end.
Conclusion
Medicaid’s role in chronic care management cannot be reduced to a single national billing rule. Coverage varies by state, by fee-for-service versus managed care structure, and, for dual-eligible patients, by the claims-processing model tied to the patient’s D-SNP. Medicare remains the primary payer for CCM services, while Medicaid may cover eligible cost-sharing through integrated, companion, or crossover workflows.
For healthcare organizations operating across multiple states, this makes payer identification and plan-specific billing logic essential. A CCM platform must determine each patient’s coverage type, apply the correct rules, and route claims through the appropriate processing path before submission. Without that logic, the gaps often appear later as denials, payment delays, or manual reconciliation.
No. There’s no standardized national Medicaid CCM benefit using Medicare’s CPT-code structure. Some states reimburse care coordination through health home programs or managed care arrangements; others don’t have an equivalent benefit, and the split often runs within a state too, between fee-for-service and managed care programs.
Medicare is billed as the primary payer using standard CCM CPT codes. Medicaid, where applicable, typically covers the cost-sharing (the 20% Part B coinsurance). How that coordination is processed depends on the D-SNP plan structure: FIDE-SNPs require integrated or companion claims processing, while other dual plan types may still use slower crossover processing.
Coverage varies by state, and within a state it can vary again between fee-for-service and managed care plans, so this requires checking directly with your state’s Medicaid agency and, for MCO-enrolled patients, the specific plan.
Yes, if it’s serving a multi-state population. The platform needs to correctly identify payer type per patient, apply the right billing logic for FFS vs. MCO Medicaid patients, and route dual-eligible claims through the correct plan-specific processing path rather than assuming a single Medicare-style rule set covers every patient regardless of coverage type.





